
Double Gloving Guidelines: What U.S. Teams Should Follow
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.


Inventory turnover in medical supplies is defined as the number of times a healthcare facility sells through and replenishes its entire inventory within a given period, typically one year. This metric, formally called the inventory turnover ratio, is the primary key performance indicator for balancing clinical availability against capital efficiency in healthcare supply chains. The industry benchmark sits at 3–5 turns per year for general healthcare facilities, while high-volume medical-surgical buyers target 4–6 turns annually. Understanding what is inventory turnover for medical supplies, how to calculate it, and how to act on it separates facilities that control costs from those that hemorrhage them.
Inventory turnover measures how efficiently a healthcare facility cycles through its stock of medical supplies within a set timeframe. A higher ratio generally signals less waste, lower carrying costs, and better cash flow. A lower ratio signals overstocking, potential expiration losses, and tied-up capital that could fund clinical operations.
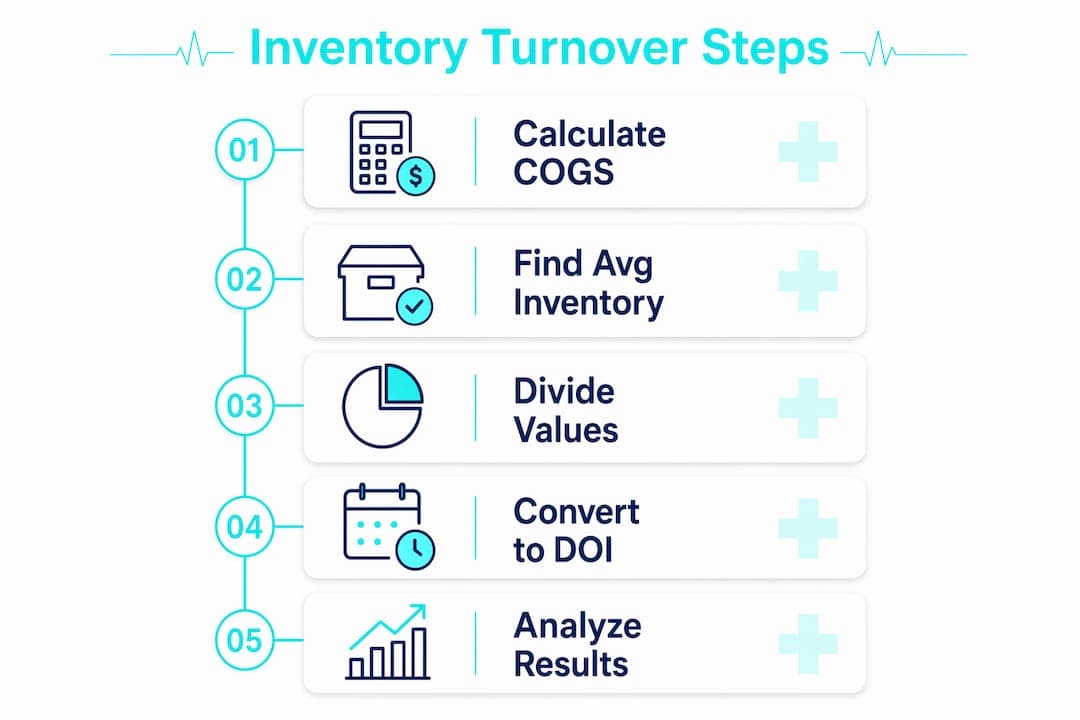
The standard formula is straightforward: Inventory Turnover = Cost of Goods Sold (COGS) ÷ Average Inventory. Average Inventory equals the beginning inventory value plus the ending inventory value, divided by two. This formula applies directly to medical supply categories including disposables, instruments, and personal protective equipment.

The ratio alone does not tell the full story. A facility running a ratio of 2.0 on surgical gloves is almost certainly overstocked. A facility running 8.0 on a critical implant category is flirting with dangerous stockouts. Context and category matter as much as the number itself.
Calculating the inventory turnover ratio for medical supplies follows four clear steps.
DOI is often more operationally useful than the raw ratio. A supply chain director can act on “we have 91 days of PPE on hand” far more directly than “our ratio is 4.0.”
Pro Tip: Run the DOI calculation separately for each major supply category. A blended facility-wide DOI of 60 days can mask a 200-day DOI on slow-moving items sitting in a back storeroom.
The COGS figure should reflect actual consumption, not purchase orders placed. Facilities that track purchases rather than consumption consistently overstate turnover and underestimate true holding costs.
Benchmarks vary significantly by facility type and supply category. Applying a single target across an entire organization produces misleading results.
The table below summarizes industry-standard benchmarks by setting and category type.
| Healthcare Setting | Supply Category | Target Turns/Year | DOI Equivalent |
|---|---|---|---|
| General healthcare facility | All medical supplies | 3–5 | 73–122 days |
| High-volume med-surg buyer | Medical-surgical supplies | 4–6 | 61–91 days |
| Surgical center | Consumables (gloves, masks) | 6–8 | 46–61 days |
| Any facility | High-value implants | 1–3 | 122–365 days |
| Any facility | Exam consumables | 6–10 | 37–61 days |
Exam consumables like fast-moving medical supplies turn far faster than high-value implants. Applying the same 4.0 target to both categories will cause you to understock disposables and overstock implants simultaneously.
Calibrating turnover targets by category is not optional. Uniform metrics obscure overstocking of slow-moving items and create risk for critical supplies. A surgical center running 10 turns on nitrile gloves is performing well. A hospital running 10 turns on orthopedic implants has a serious procurement problem.
The 3–5 turns benchmark for general healthcare reflects a balance between avoiding stockouts and avoiding excess carrying costs. Facilities below 3 turns annually are almost certainly holding too much inventory. Facilities above 6 turns in general categories risk clinical disruption from supply gaps.
Medical supply inventory management carries several complications that standard retail inventory formulas do not account for.
Pro Tip: Build a separate tracking register for consignment stock, reusable equipment in the refurbishment cycle, and items within 90 days of expiration. These three categories require different management responses than standard active inventory.
Proper medical equipment storage also affects turnover accuracy. Supplies stored incorrectly may expire faster or become unusable before consumption, creating phantom losses that distort your ratio.
Improving the inventory turnover ratio in healthcare requires both technology and process discipline. The following five strategies produce measurable results.
Each strategy compounds the others. AI forecasting without ERP integration produces recommendations that never reach the purchasing team. ERP integration without regular audits creates false confidence in data that has drifted from reality.
The inventory turnover ratio is the single most actionable metric for reducing waste and protecting clinical availability in medical supply chains.
| Point | Details |
|---|---|
| Standard formula | Divide COGS by average inventory; convert to DOI by dividing 365 by the ratio. |
| General healthcare benchmark | Target 3–5 turns per year; high-volume med-surg buyers target 4–6 turns annually. |
| Category-specific targets | Apply separate benchmarks to consumables, implants, and reusables to avoid misleading blended ratios. |
| Consignment and reverse logistics | Track consignment stock and reusable equipment separately to prevent ratio distortion. |
| Technology and monitoring | Use AI forecasting with ERP integration and review turnover monthly to prevent stockouts and write-offs. |
I have watched supply chain teams celebrate a rising inventory turnover ratio while their clinical staff quietly built personal stashes of critical supplies in desk drawers. That is the clearest sign that the metric has been optimized in isolation from the people who actually use the supplies.
The ratio is a financial tool. Patient care is the operational reality. When those two things pull in opposite directions, the ratio always loses. A facility that cuts its PPE inventory to hit a 6.0 ratio and then scrambles during a demand spike has not improved its supply chain. It has just moved the cost from carrying charges to emergency procurement premiums and staff stress.
The facilities I have seen manage this well treat inventory turnover as one input among several, not as a scorecard. They run category-level reviews, involve clinical leads in reorder point decisions, and treat a sudden ratio spike as a warning sign rather than a win. A spike in turnover on a critical item often means someone is consuming more than planned, not that procurement is running efficiently.
The most underrated practice in healthcare inventory management is the cross-functional audit. When supply chain, finance, and clinical operations sit in the same room and review the same numbers quarterly, the blind spots disappear fast. No AI system replaces that conversation.
— QB
Healthcare administrators who have their turnover metrics in order still need a reliable supplier to back up their reorder strategy.

Queenssurgical supplies hospitals, clinics, and surgical centers across the Americas with a full catalog of disposables, PPE, instruments, and equipment. From disposable face masks to isolation gowns, the platform offers both wholesale and retail purchasing with competitive pricing and consistent availability. Facilities managing tight DOI targets need a supplier that ships reliably and maintains stock on high-velocity items. Browse the full Queenssurgical catalog to source the consumables your turnover strategy depends on.
The inventory turnover ratio in healthcare measures how many times a facility cycles through its medical supply inventory in a given period. The standard formula is COGS divided by average inventory, with a benchmark of 3–5 turns per year for general healthcare facilities.
Divide 365 by the inventory turnover ratio. A turnover ratio of 4.0 equals approximately 91 days of inventory on hand, meaning current stock would last 91 days without replenishment.
A very high ratio signals lean stock levels that can lead to clinical stockouts. Excessively high turnover risks supply gaps that compromise patient care, particularly for critical or high-demand items.
No. Consignment inventory should be tracked separately because it skews the turnover ratio and hides true carrying costs. Including vendor-owned stock in your average inventory figure inflates the denominator and understates your actual capital exposure.
High-volume operations should review turnover monthly, with deeper category-level audits conducted quarterly. Regular reviews catch expiration risks, demand shifts, and procurement inefficiencies before they become costly write-offs or stockouts.
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.
Mayo and Metzenbaum scissors look alike but do different jobs. See how blades, shanks and tips differ, when to use each, and how to care for them.
Sterile water or saline? Learn the difference in tonicity, safe uses, wound irrigation evidence, and how to choose irrigation and dressing supplies.

