
Double Gloving Guidelines: What U.S. Teams Should Follow
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.
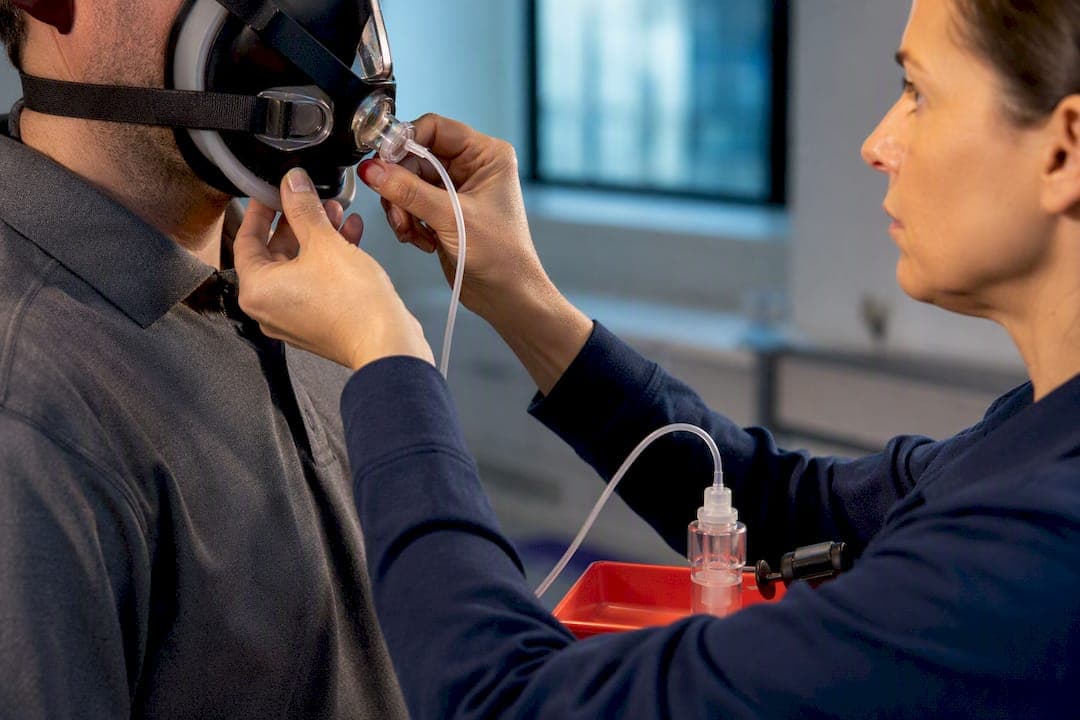
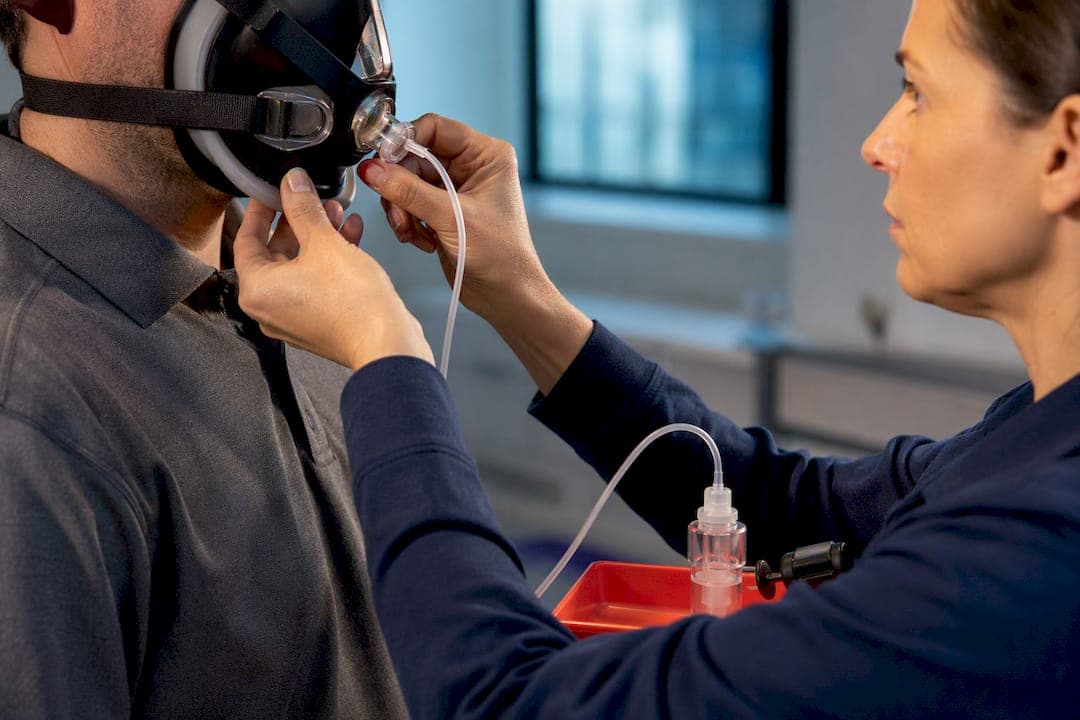
A compliant fit test follows a fixed sequence: medical evaluation clearance, respirator selection, a sensitivity screen or instrument setup, donning with a five-minute settle period, a user seal check, the seven prescribed exercises, and a documented pass/fail result. Every step ties back to OSHA 29 CFR 1910.134 Appendix A, and the test only applies to the exact make, model, and size worn. Masks and consumables that make running that sequence smoother are stocked by some suppliers.
TL;DR:
Stock Essential Fit Testing Supplies
Browse medical masks, instruments, equipment, and consumables for healthcare teams preparing compliant fit testing procedures.
Before anyone straps on a hood or sensitivity nebulizer, confirm three things: the employee has current medical clearance from a physician or licensed health care professional (PLHCP), the person administering the test knows Appendix A cold, and the room has enough respirator sizes on hand to avoid a wasted trip.
On the day itself, a few rules govern the room. The subject shouldn’t eat, drink, chew gum, or smoke for a period before a qualitative test using bitter or sweet-tasting agents, since taste sensitivity drives the whole screening step. The sealing surface of the face needs to be clean-shaven where the respirator contacts skin. Jewelry or heavy makeup near the seal line should come off.
The actual sequence runs like this:
Budget a short amount of time per person for a qualitative test. Quantitative testing runs longer because of instrument setup and calibration. A tester needs, at minimum:
Nobody gets fit tested without medical clearance first. 29 CFR 1910.134(e)(1) requires a PLHCP to evaluate an employee’s ability to wear a respirator before that employee is fit tested or assigned one. That evaluation typically happens through a questionnaire, and it needs to be current, not something pulled from a file three employers ago.
OSHA doesn’t require an outside certification to administer a fit test. An employer can designate any trained, competent person to run the program, as long as that person follows Appendix A exactly, without shortcuts or improvised substitutions. That’s a lower bar than many facilities assume, and it’s also why sloppy execution is the most common source of invalid results, not a lack of formal credentials.
Room setup matters more than people expect. A functional fit-test station needs:
Subject prep is where most delays happen. Facial hair crossing the seal line, even light stubble, is a common cause of failure, and enforcing a clean-shaven policy on the sealing surface matters more than most administrators realize. Jewelry, heavy makeup, and facial piercings near the seal should be removed. Depending on the test agent, subjects need to avoid eating, drinking, chewing gum, or smoking for a defined window beforehand, since a compromised palate throws off sensitivity screening entirely.
Pro Tip: Keep at least three respirator models in three sizes on the test cart. A single failed fit because the only option was a medium regular can turn a 20-minute test into a half-day scheduling problem.
QLFT is a pass/fail sensory test suited to negative-pressure, tight-fitting respirators like N95s, where a numeric fit factor isn’t required. It relies on the subject’s ability to taste or smell a test agent, most commonly saccharin or Bitrex, leaking past the seal.
The sequence, per OSHA’s Appendix A protocol, runs as follows:
Why the sensitivity screen matters: OSHA’s Appendix A treats a failed sensitivity screen as an automatic disqualifier for that agent, and a leading cause of false results in poorly run programs is skipping or rushing this step.
Adjusting the mask mid-exercise voids the entire test, no exceptions. If the subject detects the taste or smell of the agent at any point during the exercises, that’s a fail. Pass/fail is binary: either the subject completes all seven exercises without detecting the agent, or they don’t. A failed test means retrying with a different size or model, not repeating the same setup and hoping for a different outcome.
Documentation needs to capture the employee’s name, the respirator make/model/style/size, the test agent and protocol used, the date, and the result. Skipping any of these fields creates a record that won’t hold up if OSHA ever asks to see it.
QNFT produces a numeric fit factor instead of a pass/fail sensory judgment, and it’s the required method for full-face respirators and any situation where a documented numerical result matters, such as programs with tighter internal standards than the OSHA minimum.
Setup starts with the sampling probe. A small port gets attached to the respirator, connected by tubing to the instrument that measures particle concentration inside versus outside the mask. This is where a lot of quantitative tests go wrong: if the sampling tube pulls or tugs on the facepiece, it can distort the seal and generate an artificially low fit factor that has nothing to do with the actual fit. Strain relief on that tubing isn’t optional. Once a respirator has been fitted with a sampling probe, it typically can’t be reused for regular work, since the probe penetrates the facepiece.
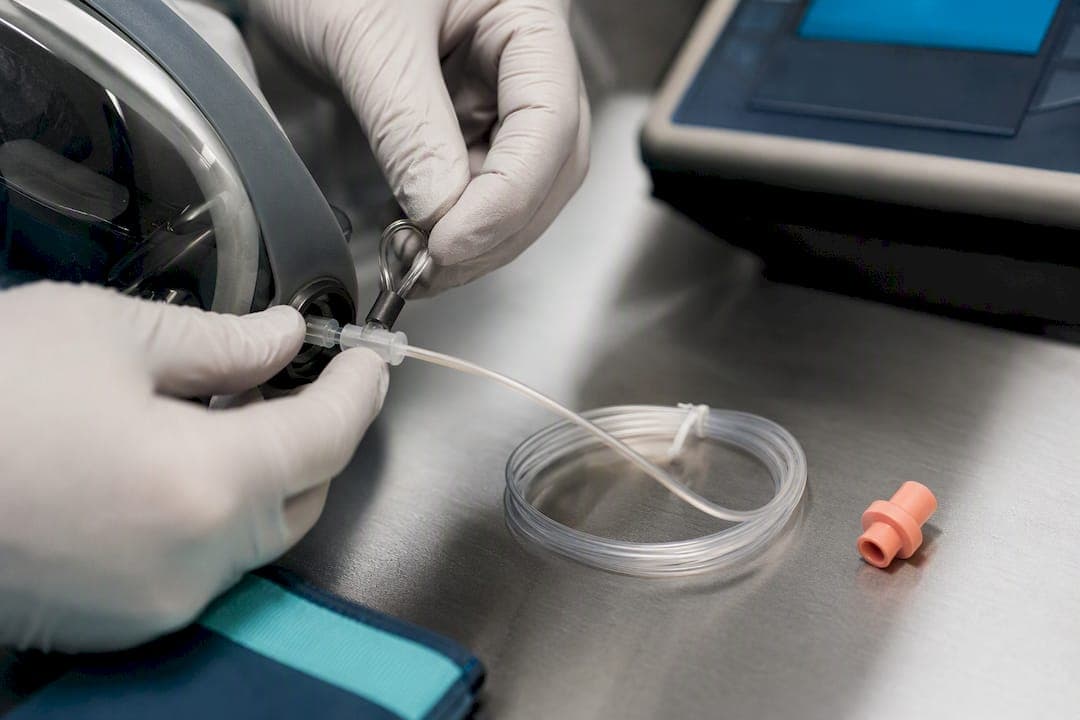
The exercise regimen mirrors QLFT with one addition: a grimace exercise, held briefly, used specifically to check whether the seal recovers after a facial distortion rather than staying disrupted. The instrument calculates a fit factor for each exercise, and the overall result comes from a harmonic mean across the full exercise set rather than a simple average, which weights lower readings more heavily and catches intermittent leaks a straight average would smooth over.
Before testing starts, the instrument needs a proper ambient particle check and a zero-calibration to confirm it’s reading accurately, not just producing plausible-looking numbers.
Pro Tip: If a quantitative fit factor comes back suspiciously low across every exercise, check the sampling tube for strain before assuming the respirator itself failed. A tugged probe can fail an otherwise well-fitted mask.
Most failed fit tests trace back to one of four causes, and each has a fairly direct fix.
Sensitivity screening failures. If a subject can’t detect the screening agent even at the highest threshold, don’t force a test that’s doomed from the start. Switch to the alternate agent (saccharin to Bitrex, or vice versa) or move the subject to quantitative testing instead, which doesn’t depend on taste or smell at all.
Facial hair. Stubble, beards, or even heavier sideburns crossing the seal line are among the most common reasons for a failed fit, and no amount of retesting fixes a beard. The practical options are a clean-shaven policy on the sealing surface, or moving that employee to a loose-fitting powered air-purifying respirator (PAPR) that doesn’t rely on a tight facial seal.
Wrong model or size. A test that fails on one respirator often passes on a different size or brand within minutes. Facilities that stock only one or two options end up sending people home or rescheduling instead of solving the problem on the spot.
Equipment errors. A poorly maintained nebulizer or an inconsistent squeeze count during replenishment throws off the whole qualitative test. Clean nebulizers between uses, follow a consistent squeeze count at each threshold level, and in quantitative testing, double-check probe strain relief before blaming the respirator for a bad reading.
An employer can designate any trained, competent person to administer fit tests, provided that person follows Appendix A exactly. There’s no OSHA-mandated outside certification, though many employers use manufacturer or third-party training programs to build that competency and document it.
OSHA requires a new or repeated fit test in a handful of specific situations, not on some arbitrary calendar:
| Record field | What to capture |
|---|---|
| Employee identifier | Name or employee ID |
| Respirator details | Make, model, style, and size |
| Test type | QLFT or QNFT, and specific protocol used |
| Date | Date the test was conducted |
| Result | Pass or fail, plus fit factor if applicable |
For facilities running annual cycles across large staffs, spreading tests across a rolling schedule tied to hire-date anniversaries avoids the compliance crunch that hits every January when everyone’s due at once.
A user seal check happens every single time someone dons a respirator, and it takes about ten seconds. It is not a substitute for formal fit testing, a distinction NIOSH guidance makes explicit, since many programs mistakenly treat a quick seal check as good enough on its own.
A seal check confirms the mask is seated correctly today. It says nothing about whether that specific model and size actually fits that specific face, which is exactly what the formal fit test settles.
Running fit tests without the right supplies on hand is how a 20-minute test turns into a canceled appointment. A working kit needs test hoods, screening and testing nebulizers or a calibrated quantitative instrument, sampling tubes with strain relief, and spare respirators across enough sizes and models to catch the person whose face doesn’t match your default stock.
Stocking depth matters more than most programs budget for. A single failed fit because the only size on the cart was a medium regular costs more staff time than keeping a small, medium, and large of two different models on hand ever will. Reference points like a youth or small-fit mask or an elongated non-rebreather style illustrate how much variation exists across face shapes and why a one-size approach fails predictably.
— QB
Running a fit-test program smoothly comes down to having the right supplies on the cart before test day, not scrambling mid-session when the only size left doesn’t fit anyone. Masks and consumables needed to build out a testing kit are available from suppliers without waiting on backordered items from a single manufacturer.

A practical starter kit covers a range of fit profiles: a molded face mask for standard sizing, a surgical mask with ties and a plastic shield for procedures requiring splash protection, and a child or youth-sized option for facilities that test smaller staff or need a reference point for narrower face shapes. Keep in mind that the respirator used during an actual fit test needs to match the exact make, model, and size the employee will wear on the job, not a similar substitute picked because it happened to be in stock.
Browse the full Queenssurgical catalog to compare sizes and models before your next testing cycle, and place an order ahead of your annual retest window so a supply gap never delays a compliance deadline.
The primary source for every procedural detail in this article is OSHA 1910.134 Appendix A, which lays out the exact accepted protocols, the seven required exercises, and the rules governing sensitivity screening and equipment adjustments.
For a clearer breakdown of qualitative versus quantitative methods and healthcare-specific notes, NIOSH’s fit testing page is the more digestible companion document. NIOSH’s respiratory protection FAQ document covers user seal check procedures and practical troubleshooting guidance in more depth than the regulatory text alone provides.
Any person the employer designates and trains to follow OSHA Appendix A exactly can administer a fit test. OSHA doesn’t require an external certification, though many facilities use structured training programs to document that competency.
There’s no single OSHA-issued certification; instead, employers train and designate competent staff internally or send them through a manufacturer or third-party training course that covers the Appendix A protocol step by step.
A fit test includes a sensitivity screen or instrument setup, donning the respirator for a five-minute settle period, a user seal check, and then a set sequence of seven exercises while checking for leakage, either by taste and smell (QLFT) or by numeric fit factor (QNFT).
At least annually, plus before initial use and any time the respirator’s brand, model, size, or style changes, or when the wearer’s facial features change enough to affect the seal, according to OSHA’s standard interpretation.
Qualitative testing (QLFT) is a pass/fail sensory test based on whether the subject detects a test agent by taste or smell, while quantitative testing (QNFT) uses an instrument to produce a numeric fit factor, as explained on NIOSH’s fit testing page.
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.
Mayo and Metzenbaum scissors look alike but do different jobs. See how blades, shanks and tips differ, when to use each, and how to care for them.
Sterile water or saline? Learn the difference in tonicity, safe uses, wound irrigation evidence, and how to choose irrigation and dressing supplies.

