
Double Gloving Guidelines: What U.S. Teams Should Follow
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.
Higher gauge numbers mean thinner needles, not thicker ones. In everyday practice, a range of gauges covers blood draws, IV access, viscous fluids, intramuscular injections, subcutaneous and insulin work, as well as the finest injections, like certain dermal procedures, with gauge sizes increasing as needle thickness decreases. The full needle gauge chart below breaks down exact millimeter and inch measurements, plus the thin-wall “s” variants worth knowing.
TL;DR:
The numbers below come straight from the Birmingham gauge (BWG) system, the standard nearly every hypodermic needle manufacturer builds against. Outer diameter (OD) determines how much the needle hurts going in and whether it fits your syringe hub. Inner diameter (ID) determines flow rate and how much medication gets stranded inside the needle after injection.

Here’s a reference indicating typical outer diameter, inner diameter, and wall thickness for common gauges along with typical uses, but precise millimeter and inch values can vary slightly across manufacturers and should be verified for exact match.
These figures track the Birmingham gauge table and the dimension tables Darwin Microfluidics publishes, which list OD and ID in both inches and millimeters for cross-checking. Where you see “s” appended to a gauge (26s, for example), the outer diameter stays the same as the standard 26G, but the wall gets thinner, so the inner diameter, and therefore the flow rate, goes up. That distinction matters more than it looks on paper, especially once you get into small-volume dosing.
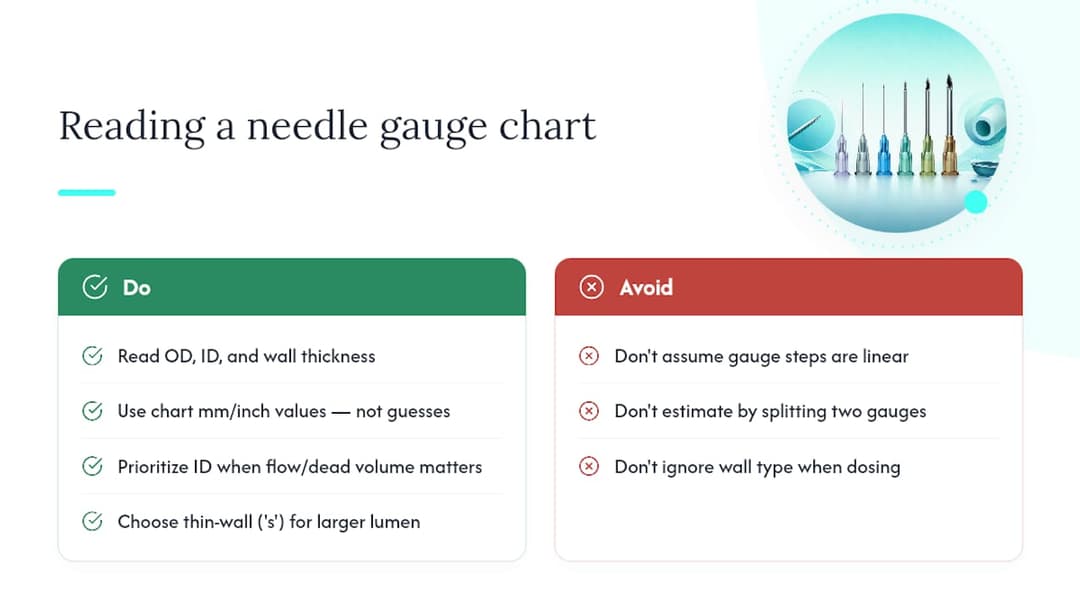
Three numbers matter on any chart: outer diameter, inner diameter, and wall thickness. OD dictates puncture size and tissue trauma; ID governs flow speed and dead volume; wall thickness is simply the gap between the two.
The trap most students fall into is assuming gauge numbers scale in even steps, like a ruler. They don’t. The BWG system is non-linear, so the jump from 20G to 21G is not the same physical distance as the jump from 30G to 31G. Guessing a needle’s diameter by splitting the difference between two known gauges will give you a wrong answer more often than a right one. Always pull the actual mm or inch value off the chart.
Regular-wall needles are the default; thin-wall (“s”) needles trade a little rigidity for a meaningfully larger lumen at the same outer diameter. That trade-off is worth it whenever dead volume or flow rate matters more than needle stiffness, which comes up constantly in small-volume dosing and lab work.
Route drives gauge selection more than any other single factor. Here’s how it typically breaks down:
Obese patients often need longer needles to reach muscle reliably on IM injections, while pediatric and geriatric patients frequently call for shorter lengths and finer gauges to reduce trauma. Specialty devices like tuberculin syringes and insulin pens use their own markings and gauge conventions, so check the device spec sheet rather than assuming standard hypodermic norms apply. Clinical guidance from Lecturio’s needle sizing reference backs this general approach: pick the thinnest gauge the fluid and route allow.
Selecting a needle isn’t a single decision, it’s a short sequence of filters. Work through them in order and you’ll rarely land on the wrong size.
The thinnest, shortest needle that still allows proper flow minimizes tissue trauma without compromising delivery, which is the balance clinical best practice actually optimizes for rather than defaulting to the thinnest needle available.
Pro Tip: Reach for a thin-wall (“s”) needle whenever you’re priming a small-volume syringe or working with an expensive medication where every microliter of dead space counts. The wider lumen at the same OD means less product gets stranded inside the needle.
Color-coded hubs are a fast visual shortcut, and most departments lean on them out of habit. Orange often means 25G, blue often means 23G, pink often means 18G, but these correspondences shift between manufacturers, and no regulatory body enforces a single universal standard.
Pro Tip: In a busy or dimly lit room, tilt the hub toward the light and read the printed numbers directly rather than trusting color memory, especially when switching between brands stocked on the same unit.
Dead volume is the fluid that stays trapped inside the needle after the plunger bottoms out, and it’s usually expressed as microliters per unit length. Hamilton’s dimension tables list dead volume alongside OD, ID, and wall thickness, because with a 10 microliter syringe, even a small amount of trapped fluid can throw off an entire dose. Thin-wall needles reduce that trapped volume at the same outer diameter, which is exactly why they show up so often in lab and microdosing work.
Before you draw up anything, check the lot number and expiration date, confirm the printed gauge and length match your order, and test the Luer fit if you’re pairing an unfamiliar needle with an unfamiliar syringe. Small-volume syringes often need a manual prime to clear air and displace dead volume before the first accurate dose. Every needle is single-use, and sharps go straight into an approved disposal container immediately after use, no exceptions.
Most needle gauge charts circulating online get copied from one source to another without anyone checking the original numbers, and small transcription errors creep in over the years. The version above draws directly from the Birmingham gauge standard and manufacturer-published dimension tables, not a secondhand summary.
Queens Surgical has spent years sourcing and cataloging clinical consumables for procurement teams who need spec accuracy, not marketing copy. Every needle and syringe listing on the Queenssurgical product pages carries the gauge, length, and packaging detail a buyer actually needs to verify before ordering. If you’re spec-checking a bulk order, that’s the level of detail to look for.
— QB
Once you know the gauge and length you need, the next step is sourcing it from a supplier who lists specs clearly instead of burying them in a PDF. Queenssurgical stocks the clinical consumables that pair with the selection process above, from standard hypodermic needles to the accessories that support safe handling, like the Halsey stainless steel needle holder for procedural work.

Before placing a bulk order, check each product page for gauge, length, and thin-wall (“s”) variant availability, since not every gauge ships in both wall thicknesses. Queens Surgical’s catalog spans consumables clinics restock constantly, including medical face masks and BP cuff barrier sleeves, alongside the needle and syringe lines your procedures depend on. For related injection route guidance, the complete guide to injection types is worth a read before you finalize an order. Browse the Queenssurgical catalog and check spec sheets on individual product pages before you check out.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.
Mayo and Metzenbaum scissors look alike but do different jobs. See how blades, shanks and tips differ, when to use each, and how to care for them.
Sterile water or saline? Learn the difference in tonicity, safe uses, wound irrigation evidence, and how to choose irrigation and dressing supplies.

