
Double Gloving Guidelines: What U.S. Teams Should Follow
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.
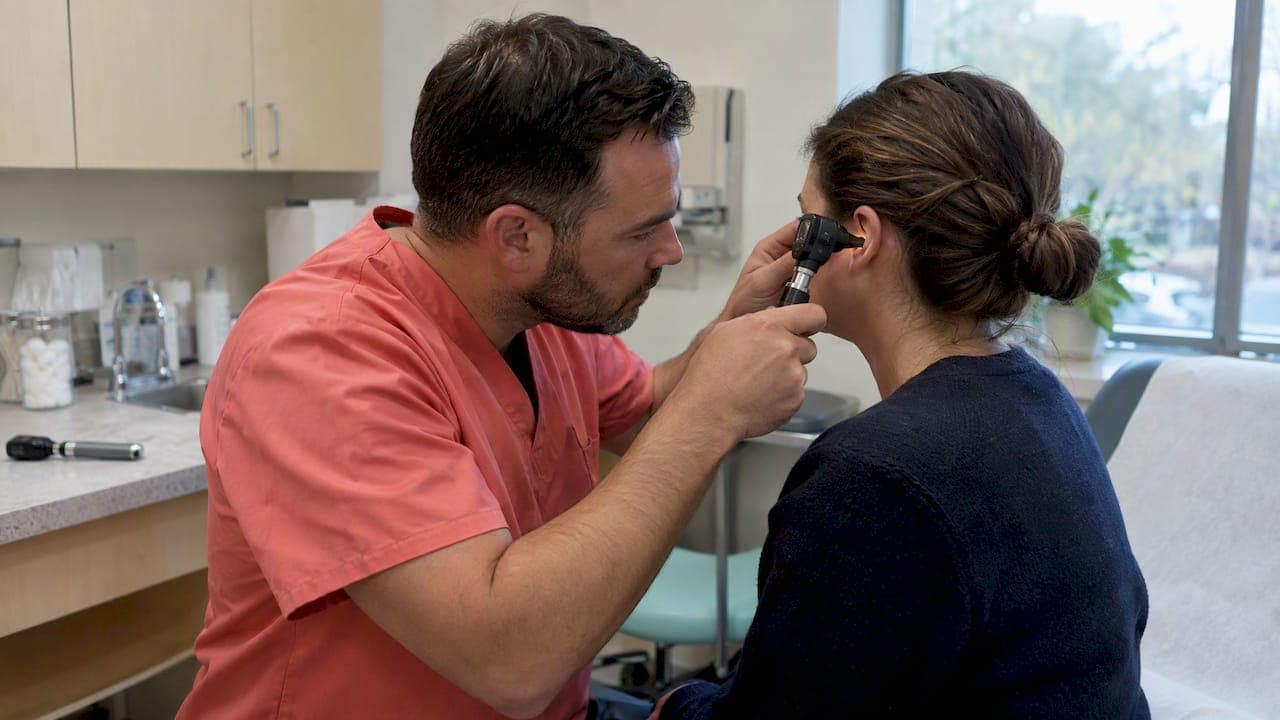
An otoscope looks at the ear canal and eardrum, while an ophthalmoscope looks at the retina and the rest of the fundus at the back of the eye. Ophthalmoscopy comes in direct and indirect forms, and otoscopy includes pneumatic testing. We draw on the American Academy of Ophthalmology, StatPearls, and our own work at Queens Surgical supplying clinic instruments.
TL;DR:
Source Instruments for Clinical Exams
Queens Surgical supplies medical instruments and equipment for healthcare professionals, clinics, hospitals, and other healthcare facilities.
An otoscope is a handheld instrument that combines a light source, a magnifying lens, and a cone-shaped speculum. The speculum slides gently into the outer ear so the examiner can see down the canal. According to StatPearls, otoscopy inspects the external auditory canal, the tympanic membrane (eardrum), and, through the membrane, parts of the middle ear.
Most handheld models accept disposable speculum tips, which keeps exams hygienic between patients. The main variants differ in what they add to that basic design:
Pneumatic testing assesses how the eardrum moves in response to air pressure, and digital health tools enhance such telemedicine-enabled ear exams for small businesses, as explained in Digital Health Tools Every SME Should Use. StatPearls also notes that digital and smartphone-enabled devices improve visualization and support telemedicine assessment. If remote exams are part of your workflow, our piece on how telehealth changes equipment requirements covers what to plan for.
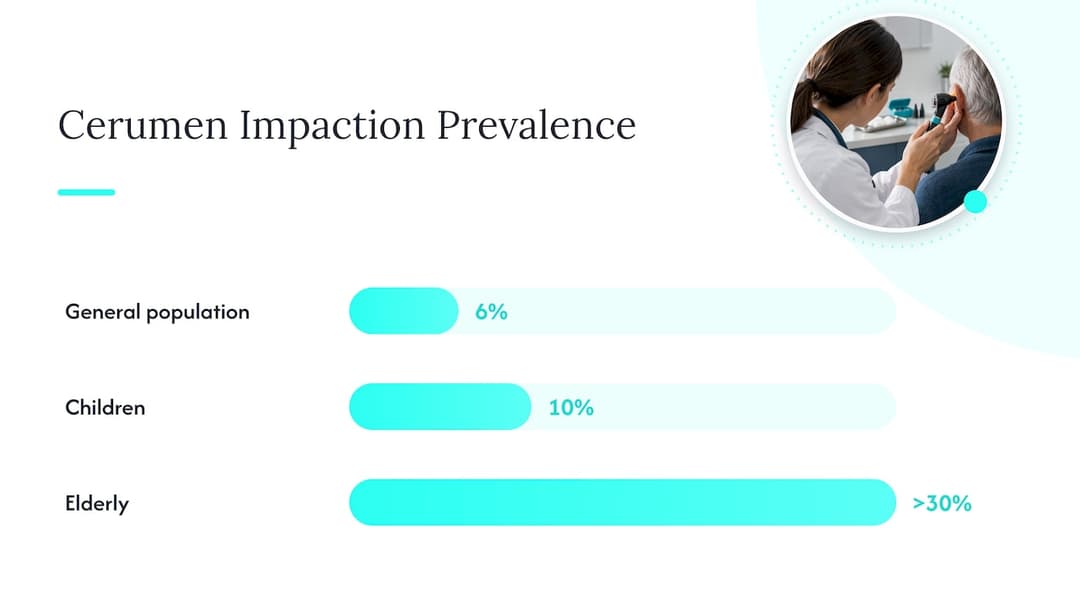
Common findings include cerumen impaction, otitis media, eardrum perforation, and retraction pockets. Earwax is the one that most often gets in the way. Cerumen impaction affects up to 6% of the general population, 10% of children, and more than 30% of the elderly, and in the United States it leads to 12 million patient visits and 8 million removal procedures a year. Impacted wax can hide the eardrum entirely, so the exam often has to pause until the canal is clear.
Pro Tip: Choose the largest speculum that fits the canal comfortably. A wider tip lets in more light and gives a cleaner view.
An ophthalmoscope lets an examiner look through the pupil at the fundus. The funduscopic examination inspects the retina, the retinal blood vessels, and the optic nerve head, and for many clinicians the handheld ophthalmoscope is the basic tool for that job. There are two main types.
A direct ophthalmoscope is the handheld version. It produces an upright image at roughly 15× magnification, per the American Academy of Ophthalmology. The catch is a narrow field, so the examiner sees only a small patch of retina at a time and must hold the device very close to the patient’s eye. Primary care clinicians commonly use it for initial screening rather than a full evaluation, as this University of Michigan teaching resource explains.
Indirect ophthalmoscopy uses a head-mounted light and a handheld condensing lens. MedlinePlus describes it as giving a wider, stereoscopic view of the peripheral retina, which is why specialists prefer it for diagnosing retinal tears and detachments. EyeWiki adds that binocular indirect ophthalmoscopy lets the examiner observe the retina dynamically and is standard for specialist exams.
The structures an examiner looks at include:
Dilating the pupil improves the view of all of these. Without dilation, a small pupil limits what a direct ophthalmoscope can show, which is one of its main practical limits.
The two tools share a handle-and-light design, but their optics point them at completely different anatomy. The practical differences come down to magnification, field of view, depth perception, and who uses them.
These design choices set the ceiling on what each tool can diagnose. A direct ophthalmoscope can screen the optic disc and central retina, but peripheral retinal pathology generally needs indirect ophthalmoscopy. An otoscope can confirm wax, infection signs, or a perforation, and pneumatic testing adds information about eardrum movement that a plain otoscope cannot give.
The overlap is smaller than people expect. No amount of adjusting turns an otoscope into an eye tool, because the anatomy, working distance, and optics are all different. Choosing between them is rarely about preference. It is about which body part needs a look.
Match the instrument to the symptom, then know when the view is not enough.
A useful rule for primary care clinicians: screen when you can, refer when the question is bigger than the tool. A direct ophthalmoscope answers “does the disc look normal?” It does not answer “is the peripheral retina intact?”
Otoscopy basics. Pick the largest speculum that fits comfortably, per practitioner advice in this PubMed-indexed review. Gently straighten the canal, advance the speculum under direct view, and identify the eardrum. Use the pneumatic bulb when indicated and watch the membrane move.
Direct ophthalmoscopy basics. Dim the room, ask the patient to fix their gaze on a distant target, and approach from a slight angle while adjusting the lens dial until the retina comes into focus. Dilation, where appropriate, widens the view.
Safety. Ear irrigation should follow an otoscopic exam that confirms an intact eardrum, and StatPearls recommends clinician-performed irrigation because of safety concerns. A PubMed review of do-it-yourself ear canal care notes that many over-the-counter ear-cleaning tools lack evidence of benefit and that self-irrigation can aggravate hidden problems such as a perforated eardrum.
Pro Tip: If you cannot see the eardrum, do not irrigate. Visualize first, then decide.
This guide draws on named clinical sources, each contributing a different piece. The American Academy of Ophthalmology supplied the direct versus indirect ophthalmoscopy comparison. StatPearls on the NCBI Bookshelf covered otoscopy, cerumen impaction, and ear irrigation safety. MedlinePlus gave the patient-facing explanation of indirect ophthalmoscopy, and PubMed literature supplied the cautions about do-it-yourself ear care. We also supply diagnostic instruments, disposables, and clinic consumables at Queens Surgical.
Good care keeps the optics clear and the light reliable. Most failures come from dirty lenses, tired batteries, and rough storage, not from the instruments themselves.
A short monthly check, covering light output, lens clarity, and speculum stock, catches most problems before they interrupt a clinic day.
Start with what you will actually do at the point of care. Features matter only if they serve that work.
For otoscopes, the main choices are:
For ophthalmoscopes, look at:
Useful accessories include hard cases, spare lamps, specula refills, and wall-mounted diagnostic sets that keep both instruments charged in one place. For cerumen work, instruments such as wide ear forceps round out an exam room alongside the otoscope.
Your setting decides which instrument earns its place first. Neither replaces the other, so the real question is which you need on day one and which you add later.
Primary care and family medicine: you will reach for the otoscope daily, and a pneumatic model pays for itself quickly in ear complaints. A direct ophthalmoscope is a sensible second purchase for screening the optic disc and central retina.
Pediatrics and urgent care: the otoscope is the workhorse here, because ear infections drive many visits. Pneumatic testing and a good range of small speculum sizes matter most.
School nursing and occupational health: a basic otoscope handles most needs, and the ophthalmoscope is optional unless your protocols include fundus screening.
ENT practices: a high-quality otoscope or video system is essential, and many such practices pair it with a microscope for cerumen removal and detailed work.
Ophthalmology and optometry: indirect ophthalmoscopy is the core tool for specialist retinal evaluation, and a direct ophthalmoscope often remains handy for quick checks.
For a wider view of how diagnostic tools fit together in a clinic, our clinical guide to diagnostic tools walks through the options.
Prices for both instruments vary widely by brand, build quality, and features, and we do not list a fixed figure here. Instead, think in tiers of what you get for the money.
Entry-level otoscopes cover the basics: a light, a lens, and a speculum set. Mid-range models usually add better LED illumination, sturdier construction, and often pneumatic capability. Video and smartphone-enabled units sit higher because they add a camera, display, or software.
Ophthalmoscopes follow a similar pattern. A basic direct model covers screening, while premium direct models offer more apertures, filters, and a wider lens range. Indirect ophthalmoscopes, with a headset and condensing lenses, are a separate, specialist-level investment.
Several budget habits help. Price the whole setup, including specula, cases, spare lamps, and charging stands, instead of only the handle. Consider how many exam rooms need their own set. Weigh durability, since a sturdier instrument that lasts through years of daily use often beats replacing a cheaper one. Current prices for specific instruments are available on our website.
The simple rule holds: otoscope for the ear, ophthalmoscope for the fundus. I would add one habit to it. Before anyone reaches into an ear with a swab, tool, or irrigator, someone should look first, and clinics do well to keep both instruments within arm’s reach and keep staff practiced with them. A tool nobody has trained on is just a heavy pen.
— QB

When you are ready to stock an exam room, we supply diagnostic instruments, disposables, and everyday clinic consumables, with both wholesale and retail purchasing, so one order can cover a whole setup. Browse what we carry:
Start at our medical equipment catalog and build your order today.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Yes. An otoscope lets the examiner see wax in the canal directly, and that is how impaction is most often diagnosed, per StatPearls. Heavy wax can also block the view of the eardrum.
You can look at your own outer canal with a video otoscope, but the view is hard to angle and interpret without training. Please don’t clean or irrigate based on what you think you see. A PubMed review on do-it-yourself ear care cautions that self-irrigation without professional visualization can aggravate hidden problems such as a perforated eardrum.
They are direct and indirect. Direct ophthalmoscopes are handheld and give an upright, magnified view of a small retinal area. Indirect ophthalmoscopes use a head-mounted light and a condensing lens to give a wider, stereoscopic view of the peripheral retina, as MedlinePlus explains.
There is no single best pair, because the right choice depends on your setting and use. Primary care clinics often favor a pneumatic otoscope and a direct ophthalmoscope, while ophthalmology practices rely on indirect ophthalmoscopy. Match features to the exams you perform most.
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.
Mayo and Metzenbaum scissors look alike but do different jobs. See how blades, shanks and tips differ, when to use each, and how to care for them.
Sterile water or saline? Learn the difference in tonicity, safe uses, wound irrigation evidence, and how to choose irrigation and dressing supplies.

