
Double Gloving Guidelines: What U.S. Teams Should Follow
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.


Retail medical markup standards are not a single universal percentage but a collection of variable pricing rules shaped by reimbursement formulas, negotiated contracts, and statutory programs. No single standard exists across hospitals, clinics, and retail suppliers. What you call “markup” in a procurement context depends entirely on whether you are dealing with Medicare Part B reimbursement, a 340B drug acquisition spread, or a hospital-insurer contract rate. Understanding which pricing model governs your transaction is the first step toward accurate cost evaluation and sustainable profitability.
Retail medical markup standards describe the pricing methodologies that determine how medical products and services are priced above their acquisition cost. The term sounds like it should refer to a fixed percentage, but the reality is far more fragmented. Hospitals apply cost-plus markup for some supply categories, while payers impose contractual reimbursement rates that override any markup calculation entirely.
Three major forces define markup practice in healthcare retail. CMS Medicare Part B sets statutory payment formulas for drugs. The 340B Drug Pricing Program creates acquisition-to-reimbursement spreads for covered entities. And hospital-insurer contracts establish negotiated rates that cap what providers can actually collect. Procurement teams that treat markup as a simple cost-plus calculation miss all three of these mechanisms.

The practical implication is direct: when a supplier quotes you a “standard markup,” ask which basis they are using. Cost-based markup, gross margin, and reimbursement spread are three different numbers for the same transaction. Confusing them is the most common pricing error in medical procurement.
Medicare Part B drug reimbursement follows a statutory formula: ASP plus 6%, reported and updated quarterly by CMS. This formula effectively replaces any conventional retail markup concept for covered drugs. The 6% add-on is not a negotiated margin. It is a fixed payment rate set by federal statute, and it applies regardless of what a supplier charges.
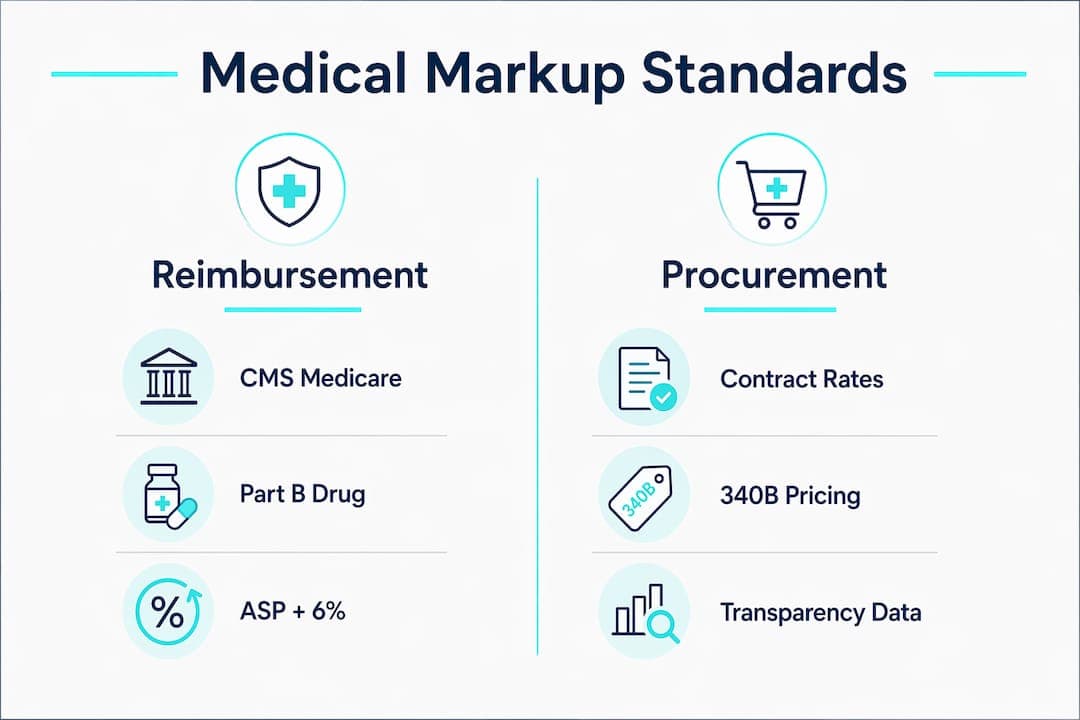
This matters for procurement because it means the reimbursement ceiling is known in advance. If a supplier prices a Part B drug above ASP, the provider absorbs the difference. The formula creates a hard ceiling on effective markup, which is why benchmarking supplier acquisition prices against ASP data is a non-negotiable step in any procurement evaluation.
Payers outside Medicare operate differently. Commercial insurers negotiate reimbursement rates directly with providers, and those rates are expressed as percentages of Medicare rates, billed charges, or negotiated fee schedules. None of these are “markup” in the retail sense. They are contractual payment floors and ceilings that determine what a provider collects after the fact.
Key reimbursement models that replace traditional markup in medical pricing:
Pro Tip: Before finalizing any supplier contract, pull the current ASP data from CMS for the relevant drug codes and compare it against the supplier’s quoted acquisition price. If acquisition cost exceeds ASP, your effective markup is negative before you start.
Markup and margin are not interchangeable, and confusing them produces systematic pricing errors. Markup is the profit expressed as a percentage of cost. Margin is the profit expressed as a percentage of selling price. For the same transaction, markup percentage is always higher than margin percentage.
The formulas are straightforward:
A concrete example clarifies the difference. If a medical glove box costs $8 and sells for $10, the markup is 25% and the margin is 20%. If a procurement manager reports a “25% margin” when they mean a 25% markup, the actual margin is only 20%. That 5-point gap compounds across a full supply catalog into a significant profitability miscalculation.
Mixing these concepts is a documented source of pricing strategy errors in retail healthcare. Markup is the right metric for setting prices. Margin is the right metric for evaluating profitability. Using markup to evaluate profitability overstates how much money you are actually keeping.
Pro Tip: Standardize your internal pricing language before any supplier negotiation. Decide whether your team reports in markup or margin, document it, and require suppliers to quote in the same format. Mismatched terminology in a contract is how a 30% markup becomes a 23% margin without anyone noticing.
CMS Hospital Price Transparency requirements, effective and enforced from 2021 with updated enforcement rules taking effect in 2026, require hospitals to post machine-readable files of standard charges and negotiated rates for all items and services. This disclosure fundamentally changes how markup can be applied in practice.
When negotiated rates are publicly posted, both payers and procurement teams can see the actual prices hospitals collect. This limits the ability to apply arbitrary markups above contract rates because the data is now visible to counterparties. For procurement professionals, transparency data is a direct benchmarking tool. You can compare a supplier’s quoted price against what hospitals in your region actually pay for the same item.
The table below contrasts the two dominant pricing models in retail medical supply:
| Pricing model | Basis | Markup visibility | Procurement implication |
|---|---|---|---|
| Cost-plus markup | Acquisition cost plus fixed percentage | High, set by supplier | Negotiable; benchmark against market rates |
| Contract-negotiated pricing | Payer or GPO contract rate | Low to moderate | Fixed by contract; limited negotiation room |
The shift toward transparency data as a pricing benchmark is accelerating. Procurement teams that use posted hospital rates as reference points gain negotiating leverage that was simply unavailable five years ago. The practical advice is to download CMS transparency files for hospitals in your procurement region and build a reference database of actual negotiated rates for your most frequently purchased supply categories.
The 340B Drug Pricing Program allows covered entities, including qualifying hospitals and federally qualified health centers, to purchase drugs at discounted ceiling prices and then bill payers at standard reimbursement rates. This creates a large acquisition-to-reimbursement spread that functions as an effective markup but operates entirely outside conventional retail markup standards.
Recent estimates place hospital profits from 340B markups at approximately $65 billion. That figure reflects the gap between what covered entities pay for drugs under 340B ceiling prices and what they collect from payers at standard reimbursement rates. No flat markup percentage governs this spread. It varies by drug, by payer, and by the size of the discount negotiated under 340B.
For procurement professionals evaluating prices from 340B-eligible suppliers, several factors require attention:
The core lesson for procurement is that 340B pricing is a reimbursement arbitrage mechanism, not a markup model. Evaluating it through a standard retail markup lens produces misleading conclusions about supplier profitability and price fairness.
Retail medical markup standards are defined by reimbursement formulas, contract rates, and statutory programs rather than any single universal percentage, making pricing literacy the most critical skill in medical procurement.
| Point | Details |
|---|---|
| No universal markup standard | Pricing rules vary by product, payer, and channel across Medicare, Medicaid, and commercial contracts. |
| ASP plus 6% governs Part B drugs | Medicare’s statutory formula sets a hard ceiling on effective markup for covered drug categories. |
| Markup and margin are not the same | A 25% markup on a product equals a 20% margin; confusing them overstates profitability. |
| Transparency data is a benchmark tool | CMS-posted hospital rates let procurement teams compare supplier quotes against real negotiated prices. |
| 340B spreads are not standard markup | Acquisition-to-reimbursement spreads in 340B operate outside conventional markup rules and carry reform risk. |
The most persistent mistake I see in medical procurement is treating markup as a fixed, knowable number. Procurement teams spend time negotiating a supplier’s markup percentage while the actual pricing outcome is determined by a reimbursement formula they never checked or a contract rate they did not know was publicly available.
The practical shift I recommend is moving from markup-centric thinking to reimbursement-aware pricing. Before any supplier negotiation, pull the relevant ASP data, check the CMS transparency files for your region, and clarify whether the supplier’s quote is cost-based markup, gross margin, or a reimbursement spread. Those three numbers look similar on paper and produce very different financial outcomes.
The 340B example is the clearest illustration of why flat markup thinking fails. A hospital buying a drug at a 340B ceiling price and billing Medicare at ASP plus 6% is not applying a markup in any retail sense. It is capturing a regulatory spread. Procurement teams that evaluate that transaction as a standard markup will consistently misread the supplier’s actual cost basis and negotiate from a false position.
The regulated medical device retail space adds another layer. Device pricing often involves bundled service components, warranty structures, and GPO contract tiers that make cost-plus markup calculations nearly impossible without detailed contract analysis. The answer is not a better markup formula. It is better pricing intelligence.
— QB

Queenssurgical supplies medical professionals, clinics, and healthcare facilities across the Americas with quality products at competitive, transparent prices. Whether you are sourcing protective equipment, instruments, or consumables, Queenssurgical’s catalog is built for procurement teams that need reliable pricing without the opacity that complicates markup evaluation. Browse frequently sourced items like the DynaShield Skin Protectant Cream or the CPE Thumb Loop Isolation Gown to compare acquisition costs directly against your current supplier quotes. Queenssurgical’s B2B and B2C capabilities mean you get wholesale pricing access without the contract complexity.
Retail medical markup standards are the pricing rules that determine how much above acquisition cost a medical product or service is priced. They vary by product type, payer, and regulatory program rather than following a single fixed percentage.
Medicare Part B pays for most covered drugs at ASP plus 6%, a statutory formula updated quarterly by CMS. This formula sets a hard ceiling on effective markup for Part B drugs regardless of what a supplier charges.
Markup is profit as a percentage of cost; margin is profit as a percentage of selling price. A 25% markup equals a 20% margin. Confusing the two leads to systematic errors in pricing strategy and profitability analysis.
The 340B program allows covered entities to buy drugs at discounted ceiling prices and bill payers at standard reimbursement rates. The resulting spread functions as an effective markup but has no statutory cap and operates outside conventional retail pricing rules.
CMS requires hospitals to post machine-readable files of standard charges and negotiated rates. Procurement teams can use this data to benchmark supplier quotes against actual market rates, improving negotiating leverage and pricing accuracy.
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.
Mayo and Metzenbaum scissors look alike but do different jobs. See how blades, shanks and tips differ, when to use each, and how to care for them.
Sterile water or saline? Learn the difference in tonicity, safe uses, wound irrigation evidence, and how to choose irrigation and dressing supplies.

