
Double Gloving Guidelines: What U.S. Teams Should Follow
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.


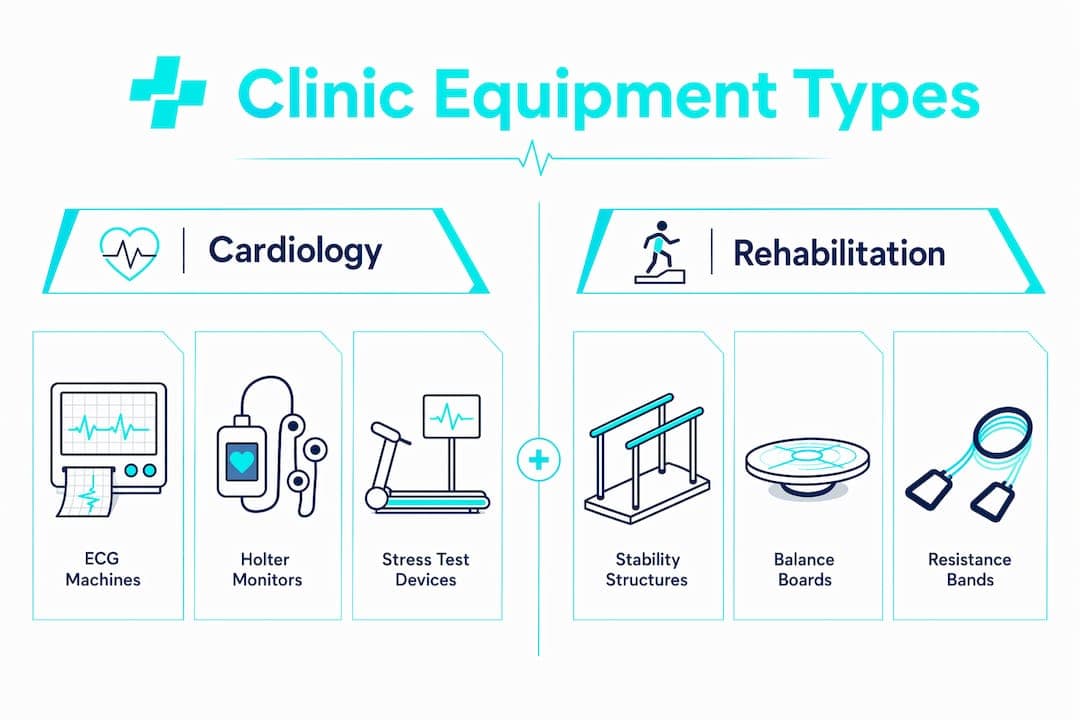
Specialty clinic equipment needs are defined as the targeted set of medical devices, diagnostic tools, and consumable supplies that each clinic must stock based on its specific medical focus. A cardiology clinic requires 12-channel ECG machines and Holter monitors. A rehabilitation clinic needs parallel bars and electrotherapy units. A surgical clinic demands endoscopes, autoclaves, and surgical lighting. What are specialty clinic equipment needs beyond this basic definition? They are the intersection of clinical function, patient volume, infrastructure capacity, and regulatory compliance. This guide covers every layer of that intersection, from baseline essentials to specialty-specific devices, spatial requirements, and long-term maintenance strategies aligned with 2026 standards.
Every specialty clinic, regardless of focus, shares a non-negotiable foundation of diagnostic and safety equipment. These are the tools that keep patients safe, support clinical decision-making, and satisfy regulatory requirements before any specialty-specific device enters the picture.
Diagnostic and examination tools form the first layer. Stethoscopes, otoscopes, glucometers, and pulse oximeters belong in every exam room. Digital blood pressure monitors are standard, and CDC 2026 guidelines specify that emergency preparedness also requires oxygen units, epinephrine at 1:1000 concentration, and first aid kits on site. This requirement applies to vaccine clinics and specialty practices alike, meaning no clinic can defer emergency readiness in favor of specialty equipment.
Infection control and PPE represent the second non-negotiable layer. Gloves, surgical masks, isolation gowns, and sterilization equipment protect both patients and staff. The sterilization choice matters significantly. UV sterilizers cover general disinfection, but any clinic performing invasive procedures requires a 12-liter steam autoclave, the recognized gold standard. Clinics that skip this distinction and rely on UV sterilizers for invasive work create measurable infection risk.
Pro Tip: Stock your wellness and immunization supplies before adding specialty devices. Regulators and accreditation bodies inspect baseline safety equipment first, and deficiencies here can delay your specialty clinic’s opening regardless of how advanced your specialty tools are.
Administrative infrastructure is often overlooked in equipment planning. EHR terminals, barcode scanners for medication tracking, and patient check-in kiosks directly affect throughput and billing accuracy. A clinic that invests in a Holter monitor but runs paper charts creates a bottleneck that undermines the clinical investment.
The specialty clinic equipment list diverges sharply once you move past the baseline. Three clinic types illustrate the range clearly: cardiology, physical therapy and rehabilitation, and surgical specialty clinics.
Cardiology clinics require diagnostic suites built around cardiac rhythm and function. 12-channel ECG machines, Holter monitoring systems with analysis software, and cardiac stress test systems using treadmills or ergometers are the core tools. These devices generate large volumes of data, which means the clinic also needs medical-grade monitors, data storage infrastructure, and software capable of producing physician-ready reports. A cardiology clinic without Holter analysis software is like a lab without a centrifuge. The hardware alone does not complete the diagnostic loop.
Rehabilitation clinics prioritize structural and mechanical tools before electronic ones. Basic rehab structures like parallel bars and therapy ladders must be secured before advanced electrotherapy devices are purchased. This sequencing matters because parallel bars support gait training for the broadest patient population, while devices like ultrasound therapy units or neuromuscular electrical stimulation systems serve narrower indications. Resistance bands, treatment tables, and balance boards round out the foundational layer. Advanced modalities like hydrotherapy tanks or robotic-assisted gait trainers belong in a second phase, once patient volume justifies the investment.

Surgical clinics carry the most complex equipment requirements. Endoscopy setups require primary visualization systems including endoscopes, camera heads, light sources, and insufflation units, plus medical-grade monitors and image capture systems. Surgical lighting, instrument trays, and sterilization rooms are non-negotiable. Explore the full scope of surgical suite essentials to understand how these components integrate into a functional operating environment.
| Clinic type | Core specialty devices | Secondary/advanced devices |
|---|---|---|
| Cardiology | 12-channel ECG, Holter monitor, stress test system | Echocardiography unit, ambulatory BP monitor |
| Physical therapy | Parallel bars, treatment tables, resistance bands | Electrotherapy units, ultrasound therapy, hydrotherapy |
| Surgical specialty | Endoscopes, surgical lighting, steam autoclave | Robotic assist systems, advanced imaging, laparoscopic towers |
Pro Tip: When evaluating equipment for specialized clinics, map each device to a specific patient diagnosis or procedure code. If a device does not correspond to at least 20% of your projected patient volume in year one, defer the purchase until demand is confirmed.
Physical space and building infrastructure determine which equipment a clinic can realistically operate, not just which equipment it can afford. This is one of the most underestimated dimensions of clinic setup equipment needs.
Specialty clinics require 1,200 to 2,000 square feet of functional floor space, compared to 600 to 800 square feet for a standard single-doctor practice. That difference is not aesthetic. It reflects the footprint of specialized equipment, the need for dedicated procedure rooms, and the patient flow patterns that prevent cross-contamination between exam and treatment areas. A cardiology clinic running stress tests needs a room large enough to accommodate a treadmill, monitoring cart, crash cart, and two clinical staff simultaneously.
Infrastructure requirements go deeper than square footage. Clinic layout must account for dedicated power circuits for high-draw equipment, medical gas lines for surgical and anesthesia use, and network infrastructure for connected monitoring systems. Surgical clinics specifically need insufflation gas supply lines, backup power for visualization systems, and sterilization rooms with proper ventilation. These elements are frequently under-planned, and the result is equipment downtime on day one of operations.
Storage and maintenance areas are equally critical. Equipment that lacks a designated storage space gets mishandled, which shortens its service life and creates compliance gaps. A sterilization room that doubles as a supply closet is a regulatory liability. Dedicated storage for clean and soiled instruments, with clear separation, is a 2026 Joint Commission requirement for accredited specialty clinics.
The practical implication: infrastructure planning must precede equipment procurement, not follow it. Ordering a laparoscopic tower before confirming that the procedure room has the correct power supply and gas connections is a common and costly sequencing error.
Equipment prioritization and lifecycle management are where most clinic managers either protect or erode their capital investment. The sequencing of purchases and the discipline of maintenance schedules determine whether a clinic’s equipment delivers its intended clinical and financial return.
Pro Tip: Build a simple equipment register in a spreadsheet or practice management system that tracks purchase date, warranty expiration, last service date, and next scheduled maintenance for every device. This single document prevents the most common maintenance failures and supports your accreditation audit.
Specialty clinic equipment needs are determined by clinical focus, patient volume, infrastructure capacity, and lifecycle management discipline, not by budget alone.
| Point | Details |
|---|---|
| Baseline equipment comes first | Diagnostic tools, PPE, sterilizers, and emergency supplies must be in place before specialty devices are ordered. |
| Specialty devices vary by clinic type | Cardiology, rehab, and surgical clinics each require distinct core devices that cannot be substituted across specialties. |
| Space and infrastructure drive procurement | Specialty clinics need 1,200 to 2,000 sq ft and dedicated power, gas, and storage infrastructure to operate specialty equipment safely. |
| Volume justifies advanced investment | Purchase high-end specialty machines only after patient demand confirms the ROI within a realistic depreciation window. |
| Lifecycle management protects the investment | Preventive maintenance schedules, service contracts, and staff training are required to sustain equipment performance and accreditation compliance. |
The most consistent mistake I see is clinics treating equipment procurement as a shopping exercise rather than a systems design problem. A manager orders a Holter monitor because a cardiologist requested it, without first confirming that the EHR can receive and store the output, that staff know how to apply the leads correctly, or that the room has the network connection the analysis software requires. The device arrives and sits in a box for six weeks.
The second pattern is infrastructure blindness. Surgical clinics are particularly vulnerable. Insufflation gas supply, backup power for visualization systems, and sterilization room ventilation are not glamorous line items, but they determine whether the operating room functions on day one. I have seen clinics spend heavily on endoscopy towers and then discover the procedure room lacks the correct gas connections. The delay costs more than the infrastructure upgrade would have.
The third issue is the false economy of deferring maintenance. A $300 annual service contract on a $15,000 ECG machine looks optional until the machine fails during a stress test. At that point, the repair cost, the lost revenue, and the patient safety exposure all exceed what years of service contracts would have cost. Maintenance is not overhead. It is risk management.
The clinics that get this right share one habit: they plan equipment needs backward from patient care workflows, not forward from a vendor catalog. Start with the clinical question you need to answer for your patient population, identify the device that answers it, confirm the infrastructure that supports it, and then purchase. That sequence, consistently applied, produces a clinic that works on day one and scales without crisis.
— QB

Queenssurgical supplies specialty clinics across the Americas with the PPE, diagnostic consumables, and infection control products that form the foundation of every clinic equipment list. From CPE thumb loop isolation gowns that meet fluid resistance standards for procedure rooms to BP cuff barrier sleeves that protect monitoring equipment between patients, Queenssurgical stocks the items clinic managers order repeatedly and need reliably. Wholesale pricing, a broad product catalog, and straightforward online ordering make Queenssurgical a practical procurement partner for both individual providers and larger purchasing organizations. Browse the full catalog at queenssurgical.net to source the supplies your specialty clinic depends on.
Specialty clinic equipment needs are the specific medical devices, diagnostic tools, and consumable supplies a clinic requires based on its clinical focus, such as ECG machines for cardiology or parallel bars for rehabilitation. They include both a universal baseline layer and a specialty-specific layer unique to each practice type.
Every specialty clinic requires diagnostic tools like stethoscopes and pulse oximeters, infection control supplies including gloves and isolation gowns, a sterilization system, sharps disposal, and emergency preparedness equipment including oxygen and epinephrine per CDC 2026 guidelines.
Specialty clinics require between 1,200 and 2,000 square feet of functional floor space, compared to 600 to 800 square feet for standard single-doctor practices, to accommodate specialized equipment, dedicated procedure rooms, and safe patient flow.
Advanced specialty devices should be purchased only after foundational diagnostic equipment is in place and patient volume confirms the return on investment within a realistic depreciation window. Purchasing high-end machines before demand is established is the leading cause of underutilized equipment in new specialty clinics.
General-purpose clinics can use UV sterilizers for surface disinfection, but clinics performing invasive procedures require 12-liter steam autoclaves, the gold standard for instrument sterilization. The choice depends directly on the invasiveness of the procedures performed.
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.
Mayo and Metzenbaum scissors look alike but do different jobs. See how blades, shanks and tips differ, when to use each, and how to care for them.
Sterile water or saline? Learn the difference in tonicity, safe uses, wound irrigation evidence, and how to choose irrigation and dressing supplies.

