
Double Gloving Guidelines: What U.S. Teams Should Follow
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.
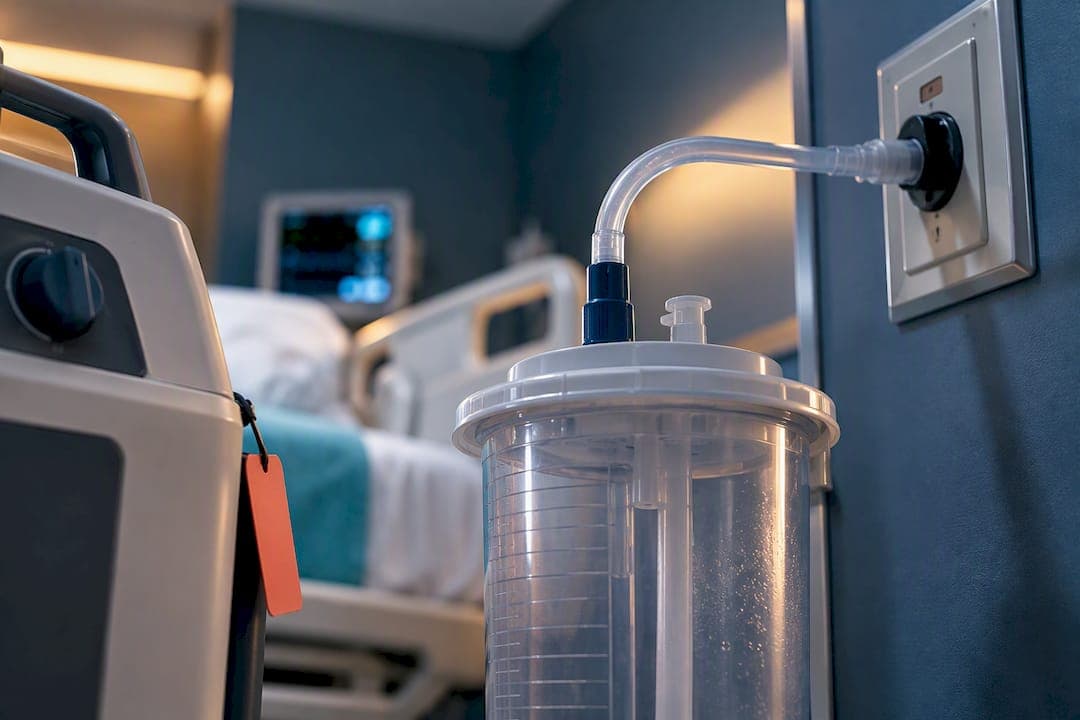
Five categories cover nearly every clinical suctioning need: manual, electrically powered (AC), battery-powered portable, wall-mounted/central vacuum, and gas-powered (venturi) systems. Wall or central vacuum is the right default for inpatient wards and operating rooms with high call volume. AC-powered portable units handle bedside and procedural suctioning. Battery-powered units belong in EMS and transport. Manual devices stay in the bag as backup. Every purchase decision should also account for FDA Class II classification, ISO 10079 performance standards, and AARC clinical guidance.
TL;DR:
Equip Your Clinical Procurement Team
Browse medical equipment, instruments, gloves, masks, and other supplies for clinics, hospitals, and healthcare facilities.
Each category trades off portability, power, and flow capacity differently, and picking the wrong one for the setting is one of the more common (and expensive) procurement mistakes.

Electrically powered (AC) units plug into standard wall outlets and generate vacuum through a motor-driven pump, typically producing flow rates and vacuum ranges suited to bedside procedures, outpatient clinics, and general ward use. They’re affordable, easy to service, and widely stocked, but they tether the patient (and the clinician) to a power outlet, which limits use during transport.
Wall-mounted or central vacuum systems draw from a facility-wide vacuum line rather than an individual pump. They deliver continuous, high-volume suction without per-unit maintenance and are the standard in ICUs and ORs where multiple patients need suction access around the clock. The tradeoff is fixed installation: they require plumbing and biomedical infrastructure, so they aren’t an option for a mobile clinic or a new build without capital investment.
Battery-powered portable units run on rechargeable batteries and are built for mobility, EMS response, ambulance transport, and disaster response. Runtime and ruggedness are the specs that matter most here. A literature review of portable suction devices found that many designs still fall short of real prehospital demands, particularly around tubing diameter and filter inclusion, so “portable” and “field-ready” aren’t automatically the same thing.
Manual suction devices (foot pumps or hand-operated syringes) require no power source at all. They’re slower and lower-flow than powered alternatives, but they’re the only option when electricity fails or when a facility needs a genuinely low-cost backup for every crash cart.
Gas-powered or venturi suction systems use pipeline medical gas, typically oxygen or compressed air, to create vacuum through the Venturi effect. They show up mostly in operating rooms and integrated pipeline systems where gas infrastructure already exists. ISO 10079-3 covers performance expectations for this category specifically, since it doesn’t rely on an electric motor the way AC or battery units do.
The pump gets the marketing attention, but clogging, weak flow, and inconsistent pressure usually trace back to the consumables around it, not the motor itself.
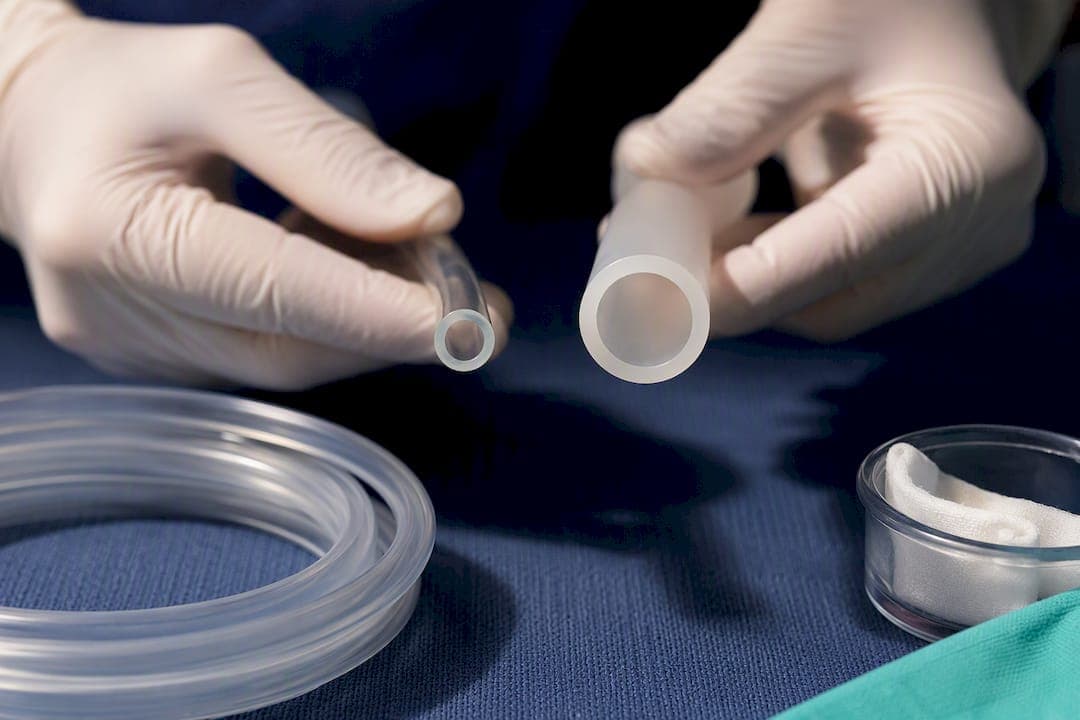
Catheter and tip selection follows its own rules. The Yankauer tip is the standard for oral suctioning of thick secretions. A wide-bore (“Wide Yank”) tip handles higher-volume or particulate matter. Flexible catheters are sized for nasopharyngeal or tracheal suctioning and must be matched to the artificial airway’s internal lumen, according to StatPearls’ guidance on airway suctioning, which also outlines the practical differences between open and closed suction technique.
Pro Tip: When secretions are thick or purulent, oversized tubing and a larger-bore catheter will save more clinical time than a stronger pump. Clogging is almost always a tubing problem, not a power problem.
Buying the wrong category for the setting is the single most avoidable procurement error in this space. A quick rundown:
A quote sheet with a price and a flow-rate number isn’t enough to make a sound purchasing decision. Ask for documentation that actually proves the device performs as advertised.
Consistent pressure regulation, not brand reputation, is the spec that predicts real-world performance. A device with a well-documented performance curve and stable pressure control at the low end of its range will outperform a higher-wattage unit with sloppy regulation, especially for pediatric and neonatal suctioning where pressure ceilings matter most.
Battery-powered units for EMS fleets carry their own failure mode: battery health. Ask vendors for maintenance intervals and real-world uptime data rather than relying on spec-sheet runtime alone, since portable device reviews flag battery degradation as one of the more common field failures.
Powered suction pumps fall under FDA Class II device regulation (21 CFR 878.4780), which sets expectations for device description, performance specs, and testing documentation vendors should be able to produce on request. The ISO 10079 series covers safety and performance requirements for both electrically powered and venturi-powered suction equipment, and procurement teams should ask vendors to reference the specific part that applies to the device in question.
On the clinical side, AARC guidelines recommend:
Pressure calibration, a documented maintenance schedule, and staff training on these limits do more for patient safety than any single hardware upgrade.
Beyond device selection, the consumables around a suction system determine whether it performs reliably day to day. Queenssurgical’s respiratory equipment guide covers system configurations in more depth, and the catalog includes disposable canisters with float-valve shutoff for teams standardizing consumables across departments.
Buyers spend most of their budget scrutiny on the pump and almost none on the maintenance plan. A wall vacuum system with no calibration schedule and untrained staff is more dangerous than a cheaper unit that’s properly maintained. Fix the maintenance and training gap before comparing another spec sheet.
— QB
One key advantage in medical supply is reliable access to disposable canisters, tubing, and filters without the long lead times that stall out smaller distributors, supported by extensive procurement experience across clinics, hospitals, and EMS buyers.

If your team is standardizing consumables for wall vacuum or portable suction systems, start with the disposable suction canister with float valve shutoff, a straightforward way to cut cross-contamination risk without adding a new SKU to track down every quarter. Queenssurgical also stocks the broader respiratory, wound care, and PPE categories your department likely orders alongside suction consumables, and wholesale buyers can request technical data sheets or a quote directly. Browse the full Queenssurgical catalog to check current stock and get a quote for your next order.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
The two most common types in clinical settings are electrically powered portable units and wall-mounted/central vacuum systems. Wards and ORs typically rely on central vacuum for continuous, high-volume access, while portable AC units cover bedside procedures and mobile clinical needs.
The two main techniques are open suctioning, where the ventilator circuit is disconnected to pass the catheter, and closed suctioning, which uses an inline catheter that stays connected to the circuit. StatPearls notes closed systems help maintain oxygenation and reduce exposure risk for ventilated patients.
There’s no single best option. The right suction machine depends on the setting: wall/central vacuum for high-volume inpatient use, AC-powered portables for bedside procedures, battery-powered units for EMS and transport, and manual devices as backup when power isn’t available.
For adult inpatients, wall-mounted or central vacuum systems generally offer the most reliable performance for routine and emergency suctioning. For adult transport or field use, a battery-powered portable with adequate runtime and a large-bore catheter option is the better fit. Pressure ceilings and maximum suction duration should follow AARC guidance regardless of which device type you choose.
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.
Mayo and Metzenbaum scissors look alike but do different jobs. See how blades, shanks and tips differ, when to use each, and how to care for them.
Sterile water or saline? Learn the difference in tonicity, safe uses, wound irrigation evidence, and how to choose irrigation and dressing supplies.

