
Double Gloving Guidelines: What U.S. Teams Should Follow
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.


Suture materials split along two axes: absorbable versus nonabsorbable, and monofilament versus multifilament. The clinical rule that matters most is the 60-day tensile-strength threshold, which separates materials that lose their holding power within two months from those that don’t. As a rough map, use synthetic absorbables like Vicryl or PDS for deep tissue, and monofilament nonabsorbables like Nylon or Prolene, or a rapidly absorbing option, for skin.
TL;DR:
Every suture material sits somewhere on three overlapping spectrums, and once you understand them, the entire catalog of options stops feeling arbitrary.
The first is absorbability. Absorbable sutures lose at least 50% of their tensile strength within 60 days, broken down by the body and eventually cleared. Nonabsorbable materials retain at least half their strength past that 60-day mark, sometimes indefinitely, and either stay in the tissue permanently or get physically removed.
The second axis is structure. Monofilament sutures are a single strand. Multifilament (braided) sutures twist several smaller strands together. This distinction drives real clinical consequences:
The third axis, synthetic versus natural, determines how the body actually gets rid of absorbable material. Synthetic polymers break down through hydrolysis, a chemical reaction with water that triggers a mild, predictable inflammatory response. Natural materials like gut break down through proteolysis, enzymatic digestion by the body’s own cells, which tends to provoke a stronger, less predictable tissue reaction.
Here’s where the taxonomy becomes practical. Below is a working reference for the materials you’ll actually pull off the shelf, organized by category.
Rapidly absorbable materials dissolve fast and lose strength early, which limits them mostly to tissue that heals quickly on its own.
Synthetic absorbable materials dominate modern practice because their degradation is predictable and their tissue reaction is mild.
Nonabsorbable materials stay put, either permanently or until you physically remove them.
Statistic Callout: A systematic review of nine randomized trials covering 804 participants found no statistically significant difference between absorbable and nonabsorbable sutures for facial skin closure across infection rates, scarring, or wound dehiscence. For many surface closures, the “gold standard” nonabsorbable option isn’t actually outperforming the absorbable alternative.
Selection gets simpler if you run it as a sequence rather than trying to memorize a master list.
Removal timing follows the tissue, not a fixed calendar: face sutures typically come out at 5 to 7 days, scalp and trunk at 7 to 10 days, and extremities or areas under tension at 10 to 14 days.
Pro Tip: Monofilament’s memory works against you at the knot. Add one or two extra throws beyond what you’d use for a braided suture, and square each throw down flat rather than cinching at an angle, or you’ll watch that “secure” knot slowly unwind over the next 48 hours.

The USP scale runs from large diameters (like 5 or 2) down through 0, then into increasingly fine sizes denoted by multiple zeros (4-0, 5-0, 6-0). More zeros means a thinner strand.
Needle curvature matters too. A 3/8 circle handles most skin and superficial work, while tighter curves suit confined spaces. Cutting-point needles pierce skin cleanly, while tapered points push tissue aside without cutting, the better choice for fascia, bowel, or vessel walls where a cutting edge risks tearing.
Diameter directly trades off against trauma: a thicker strand holds more tension but leaves a bigger track mark, which is why cosmetic zones always push toward the finest gauge the tissue can tolerate.
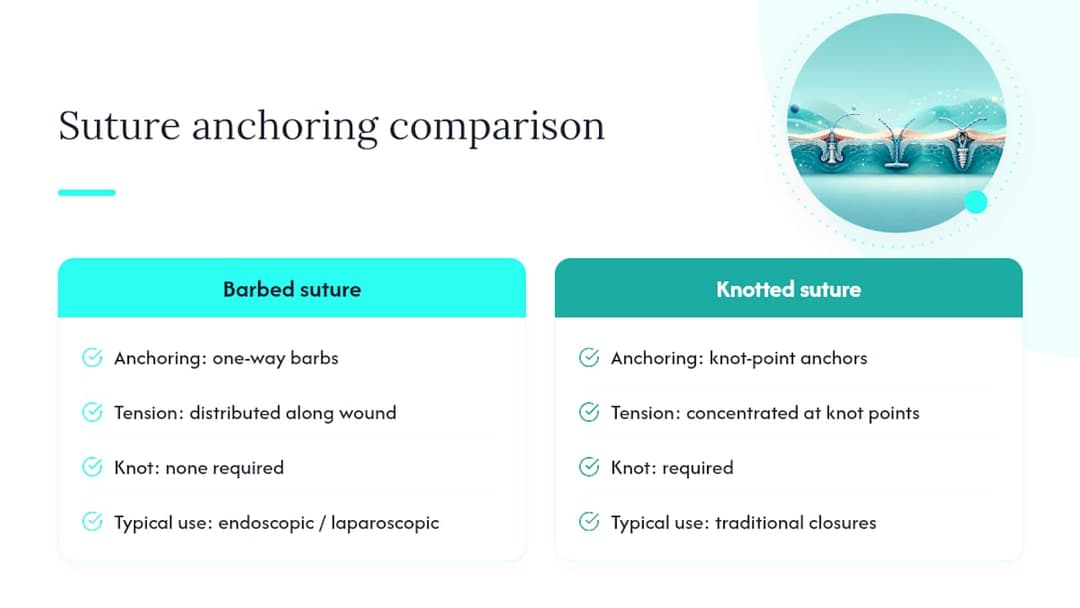
Barbed sutures are changing how some long incisions get closed. Tiny barbs cut into the strand act as one-way anchors that grip tissue without a knot, distributing tension evenly along the entire wound line instead of concentrating it at knot points. They show up most often in endoscopic and laparoscopic procedures where knot-tying in a confined space is genuinely difficult.
The other shift is in how confidently clinicians now reach for absorbables on visible skin. With randomized evidence showing comparable cosmetic and infection outcomes for facial closures, more practitioners are skipping the suture-removal visit entirely for appropriate wounds. Antibiotic-coated braided sutures, typically triclosan-coated Vicryl, are also seeing more consideration in cases where infection risk is a specific concern, though they remain a judgment call rather than a default.
A few habits separate a clean closure from a frustrating one.
Pro Tip: Before any procedure, confirm you have backup sizes on hand, not just your first-choice suture. Running out of 5-0 Monocryl mid-closure and improvising with 4-0 is how avoidable scars happen.
Every classification system in this guide, absorbable versus nonabsorbable, monofilament versus multifilament, synthetic versus natural, exists to make suture selection faster. But the data has a habit of quietly overturning assumptions clinicians have carried since training. The fact that Monocryl often beats Vicryl on cosmetic outcome for certain skin closures, and that absorbables can match nonabsorbables on facial wounds with statistical rigor behind that claim, should reshape how often braided nonabsorbable defaults still get reached for out of habit rather than evidence.
The bigger issue in most clinics isn’t ignorance of the taxonomy. It’s inventory. A resident who knows exactly why PDS belongs in a fascial closure still ends up using Vicryl because that’s what’s stocked in the tray. Suture selection is only as good as the supply chain behind it, and that’s a procurement problem as much as a clinical one. Facilities that treat their suture stock as an afterthought are quietly narrowing their own clinicians’ options every single day.
— QB
Clinicians shouldn’t have to compromise on suture selection due to what happens to be in stock., and. Browse our surgical supply catalog to see the range firsthand.
A supplier provides a full range of consumables clinics and hospitals need to keep procedures running, from wound dressings to procedural supplies, sourced for medical professionals and procurement teams across the Americas.

Unlike scrambling to source a specific suture family or gauge from multiple vendors, some platforms centralize ordering for clinics, individual practitioners, and larger purchasing organizations in one catalog. If your team is stocking for elective cases or restocking after a busy week, our surgical suite procurement guide walks through building a supply list that matches your case mix, and pairing suture stock with dressing supplies like our sterile adhesive bandages rounds out the closure workflow from first stitch to final dressing. Check current availability and place an order through our product catalog today.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Referenced throughout: suture classification and selection (PMC), facial closure meta-analysis (PMC), StatPearls suture chapter (NCBI), Merck Manual suture table.
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.
Mayo and Metzenbaum scissors look alike but do different jobs. See how blades, shanks and tips differ, when to use each, and how to care for them.
Sterile water or saline? Learn the difference in tonicity, safe uses, wound irrigation evidence, and how to choose irrigation and dressing supplies.

