
Double Gloving Guidelines: What U.S. Teams Should Follow
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.


Vetting new medical equipment suppliers is the process of systematically evaluating potential vendors against technical, regulatory, financial, and service criteria to confirm reliability, safety, and long-term value. For healthcare procurement professionals, a weak supplier relationship does not just create budget problems. It creates patient safety risks, regulatory exposure, and operational failures that are difficult to reverse. The most effective approach uses a structured, multi-criteria framework that covers ISO 13485 compliance, FDA registration status, total cost of ownership, logistics capacity, and post-sale support. Each of these dimensions carries distinct weight in the final decision, and skipping any one of them is where procurement teams consistently get burned.
Supplier evaluation in medical procurement follows five core dimensions: technical compliance, regulatory status, pricing, delivery capability, and after-sales support. Each dimension must carry a defined weight in your scoring model. Treating them as equally important is a mistake because they are not.
Technical compliance means the supplier’s products meet your facility’s clinical and operational specifications. This goes beyond reading a spec sheet. You need to confirm that the equipment performs as described under real-world conditions, that components are standardized, and that the supplier understands how the product integrates into your workflows. A supplier who can only recite specifications without explaining maintenance requirements or failure modes is a red flag.

Regulatory status covers certifications such as FDA 510(k) clearance, CE Mark, and ISO 13485 quality management system certification. These are not optional checkboxes. They are legal and operational requirements. Weighting price above 40% of your total evaluation score leads to supplier failure within the first year because vendors cut corners on quality and compliance to win on cost. That single finding should reset how your team builds its scoring model.
Unit price is the wrong metric. Total cost of ownership includes maintenance contracts, spare parts availability, technician call-out fees, and staff training costs. The cheapest initial bid frequently becomes the most expensive long-term choice. Build a cost model that projects expenses over a three-year horizon before comparing bids.
Delivery capability covers lead times, regional warehouse presence, order tracking, and responsiveness to urgent requests. A supplier with excellent products but unreliable logistics creates stockout risks that directly affect patient care. Ask for documented delivery performance data, not just verbal assurances.
After-sales support is often the dimension procurement teams underweight. It includes technician availability, training programs, documentation quality, and warranty terms. This dimension becomes the deciding factor when two suppliers score similarly on technical and regulatory criteria.
Pro Tip: Build your evaluation scorecard before you contact any supplier. Defining weights in advance prevents bias toward whichever vendor makes the strongest first impression.
Certification verification is the step most procurement teams rush, and it is where compliance failures originate. Suppliers routinely present certificates that are expired, out of scope, or issued to a parent company rather than the manufacturing facility you are actually sourcing from.
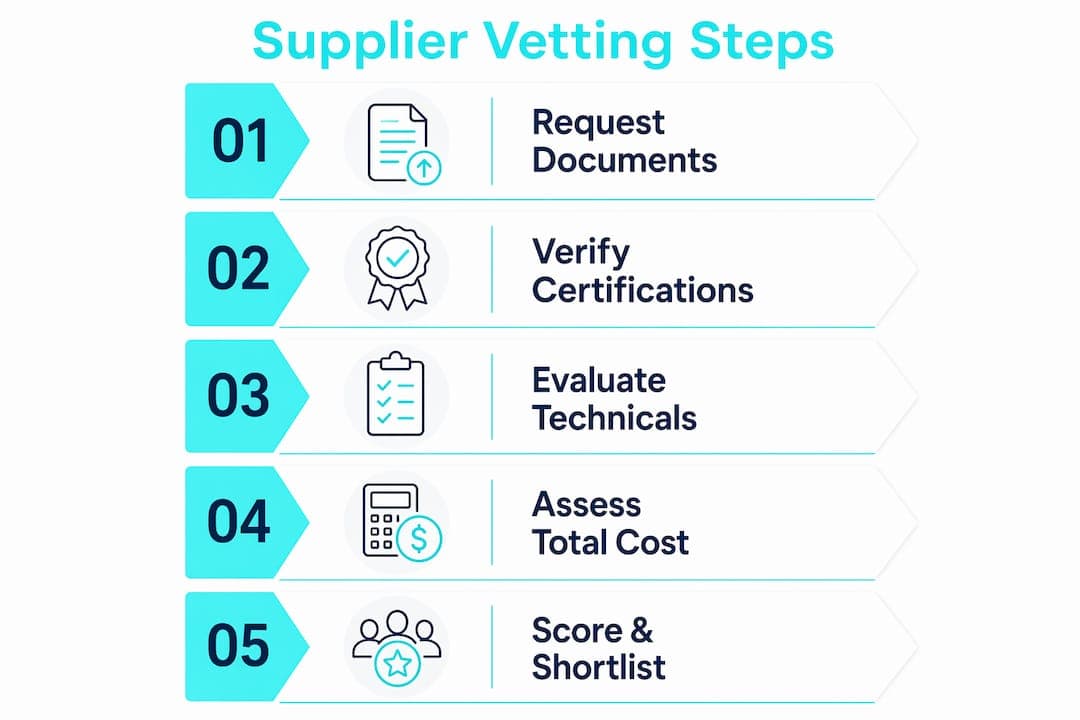
Follow these steps in order:
Pro Tip: Ask the supplier’s quality manager directly which notified body or registrar issued their ISO 13485 certificate. A confident, immediate answer signals genuine compliance. Hesitation or redirection to sales staff is a warning sign.
For a detailed breakdown of what to look for in regulatory documentation, the vendor comparison checklist from Queenssurgical covers the key verification steps for 2026 procurement standards.
Objective scoring requires a weighted model built before supplier contact begins. The model assigns percentage weights to each evaluation dimension, collects evidence-based scores for each supplier, and produces a ranked shortlist.
Shortlisting at least three suppliers is standard practice for major medical equipment procurement. Evaluating fewer than three creates false urgency and removes the competitive pressure that keeps pricing and service commitments honest.
Assign weights across your five core dimensions. A typical distribution for medical equipment procurement places technical compliance and regulatory status as the two highest-weighted categories, with pricing capped below 40% to avoid the quality-cutting dynamic described above. Delivery and after-sales support share the remaining weight based on your facility’s operational priorities.
Score each supplier on a 1–5 or 1–10 scale for each dimension. Multiply the score by the weight to produce a weighted score. Sum the weighted scores for a total. This produces a defensible, documented ranking.
ISO 13485 Clause 7.4 requires documented, risk-based supplier management, including quality agreements and periodic re-evaluation. Your scoring model is the foundation of that documentation. Failure to maintain evaluation records creates high audit risk during FDA inspections or notified body reviews.
Every supplier who clears your threshold score should be added to your Approved Supplier List (ASL). The ASL is a living document. It requires periodic re-evaluation, typically annually or after any significant supplier incident. Procurement teams that treat the ASL as a one-time exercise create compliance gaps that surface during audits.
Spreadsheet-based models work for smaller procurement teams. Larger organizations with multiple concurrent evaluations benefit from dedicated supplier management platforms that automate scoring, track certificate expiration dates, and flag re-evaluation deadlines.
After-sales support quality separates suppliers who perform well on paper from those who perform well in practice. The evaluation happens before you sign a contract, not after your first equipment failure.
Suppliers with in-house regional technicians deliver faster emergency response and less equipment downtime than those relying on third-party contractors. Ask every supplier candidate directly: are your service technicians employees or contractors? What is the average response time for emergency repairs in your region? Get those answers in writing.
Key areas to assess:
Technical depth in supplier discussions reveals real expertise. Ask maintenance and operational questions that go beyond the spec sheet. Suppliers who provide specific, actionable answers demonstrate genuine support capacity. Those who redirect every technical question to a product brochure do not.
Pro Tip: Request a sample service report from a recent customer repair. A well-documented service report shows the supplier’s technicians follow structured procedures. A vague or incomplete report predicts the quality of support you will actually receive.
For guidance on sourcing and qualifying suppliers from the ground up, the Queenssurgical resource on wholesale supplier qualification covers the full process in detail.
Effective supplier vetting requires a multi-criteria scoring framework that balances regulatory compliance, total cost of ownership, and service infrastructure before any purchasing decision is made.
| Point | Details |
|---|---|
| Cap price weighting below 40% | Overweighting price drives quality failures; balance cost against compliance and service scores. |
| Verify certifications in official databases | Cross-check ISO 13485, FDA registrations, and CE Marks in EUDAMED and FDA databases directly. |
| Score certificate duration, not just validity | A certificate expiring in three months carries more risk than one valid for four years. |
| Shortlist at least three suppliers | Evaluating three or more candidates maintains competitive pressure and reduces fraud risk. |
| Assess in-house technician networks | Suppliers with regional in-house technicians deliver faster response and lower downtime than those using contractors. |
The most expensive lesson in procurement is learning that a supplier’s sales team and their operations team are two entirely different organizations. I have sat through polished presentations from vendors who could not answer a single question about their ISO 13485 recertification timeline or explain which notified body audited their facility. Those are the suppliers who create problems six months after contract signature.
The instinct to verify documentation yourself, rather than accepting what a supplier submits, is the single habit that separates experienced procurement professionals from those who keep getting surprised. Checking an FDA establishment registration number takes four minutes. Discovering a non-compliant supplier after equipment is already deployed takes months to resolve and carries real regulatory exposure for your facility.
Price pressure is real, and I understand it. But the procurement teams I have seen struggle most are the ones who let a low bid override a weak compliance score. The math always catches up. Maintenance costs, emergency repair fees, and downtime losses erase the initial savings within the first year, which is exactly what the research on price weighting confirms.
The other mistake I see repeatedly is treating supplier approval as a finish line. Onboarding a supplier is the beginning of a managed relationship, not the end of an evaluation. Certificate expiration dates, technician network changes, and quality system lapses all require ongoing monitoring. Build re-evaluation triggers into your ASL from day one.
— QB
Healthcare procurement teams need suppliers who meet the same compliance standards they evaluate in others.

Queenssurgical carries a catalog of certified medical supplies built for clinical settings across the Americas, including CPE isolation gowns, BP cuff barrier sleeves, and non-rebreather elongated masks. Each product category is designed to meet the quality and safety standards that procurement professionals require. Whether your facility needs consumables for daily clinical use or protective equipment for infection control, Queenssurgical offers both wholesale and retail purchasing options with straightforward ordering. Browse the full catalog to find products that fit your facility’s compliance requirements and operational needs.
Request the supplier’s ISO 13485 certificate, FDA establishment registration number, and CE Mark documentation, then verify each against official databases before proceeding with any scoring or negotiation.
Shortlisting at least three suppliers is standard practice for major medical equipment procurement. Evaluating fewer removes competitive pressure and increases the risk of overpaying or accepting weaker compliance terms.
Unit price excludes maintenance, spare parts, training, and downtime costs. The cheapest initial bid frequently becomes the most expensive long-term choice once hidden costs are factored in over a multi-year horizon.
A supplier who cannot produce internal audit summaries or management review outputs within 48 hours carries significant compliance risk. ISO 13485 and FDA requirements mandate that these documents exist and be readily available at all times.
Annual re-evaluation is the standard minimum for suppliers on an Approved Supplier List. Re-evaluation should also be triggered by any significant supplier incident, certificate renewal, or change in the supplier’s ownership or manufacturing location.
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.
Mayo and Metzenbaum scissors look alike but do different jobs. See how blades, shanks and tips differ, when to use each, and how to care for them.
Sterile water or saline? Learn the difference in tonicity, safe uses, wound irrigation evidence, and how to choose irrigation and dressing supplies.

