
Double Gloving Guidelines: What U.S. Teams Should Follow
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.
Choosing right surgical gloves is defined as selecting sterile, properly fitted, procedure-matched gloves that meet FDA and ASTM standards to protect both the surgical team and the patient. Surgical gloves differ fundamentally from exam gloves in sterility, quality thresholds, and anatomical fit. The AQL standard for surgical gloves is 1.0 or lower, compared to 2.5 or lower for exam gloves. That tighter pinhole tolerance directly reflects the higher contamination risk in sterile invasive procedures. Getting this decision wrong is not a minor procurement error. It is a patient safety failure.
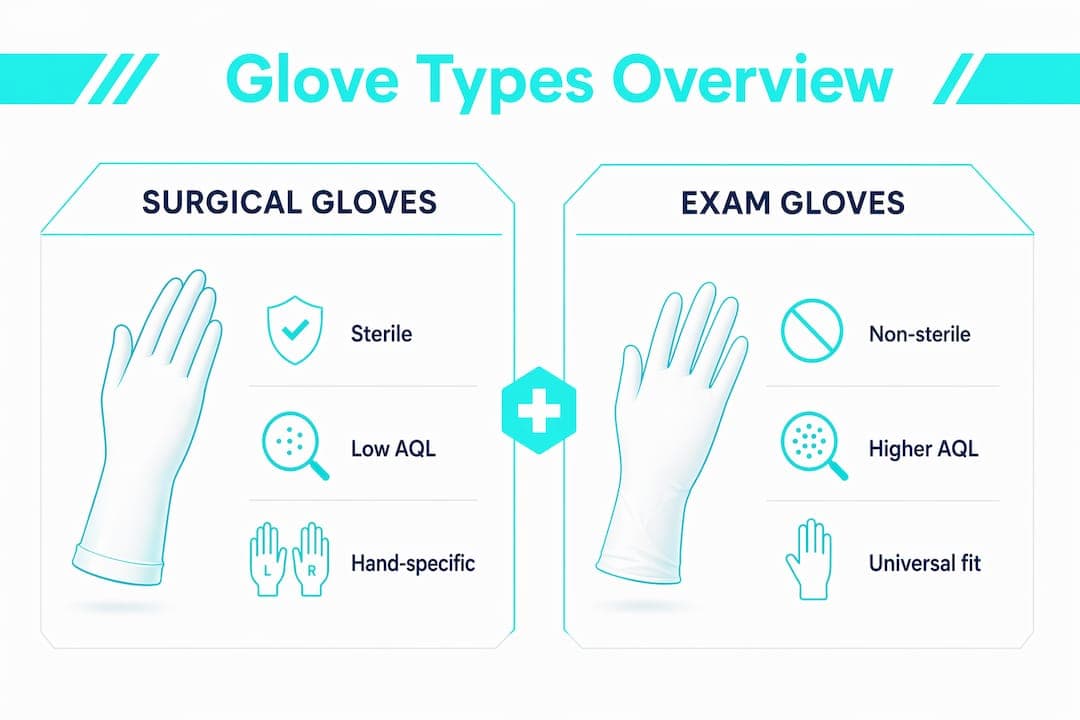
Surgical gloves are sterile, individually packaged, and manufactured to a stricter AQL of 1.0 or lower. Exam gloves carry an AQL of 2.5 or lower and are non-sterile by design. That gap matters because a higher AQL means more acceptable defects per batch, which is acceptable for a physical exam but not for open surgery.
The fit difference is equally significant. Surgical gloves come in hand-specific left and right configurations with numbered half sizes. Exam gloves are ambidextrous and sized in broad categories like small, medium, and large. The anatomical shaping of surgical gloves reduces material bunching, which directly supports tactile sensitivity during delicate procedures.
Packaging reflects the sterility requirement. Surgical gloves arrive in double-wrapped, individually sterile packs designed for aseptic donning. Exam gloves come in bulk dispensing boxes. Regulatory classification also differs: surgical gloves fall under FDA Class II medical devices, which requires 510(k) clearance.
Cost is the most common reason procurement managers blur the line between the two. Exam gloves cost roughly $0.04–$0.12 per glove, while surgical gloves run $0.75–$3.00 per pair. Using surgical gloves for non-sterile tasks wastes budget without improving safety. Using exam gloves for sterile procedures creates genuine clinical risk.
| Feature | Surgical gloves | Exam gloves |
|---|---|---|
| Sterility | Sterile, individually packaged | Non-sterile, bulk dispensed |
| AQL threshold | 1.0 or lower | 2.5 or lower |
| Sizing | Numbered half sizes, hand-specific | S/M/L, ambidextrous |
| FDA classification | Class II, 510(k) required | Class I |
| Cost per pair | $0.75–$3.00 | $0.04–$0.12 |
Pro Tip: Never substitute exam gloves for surgical procedures to cut costs. The AQL difference alone represents a measurable increase in contamination risk that no budget justification can offset.
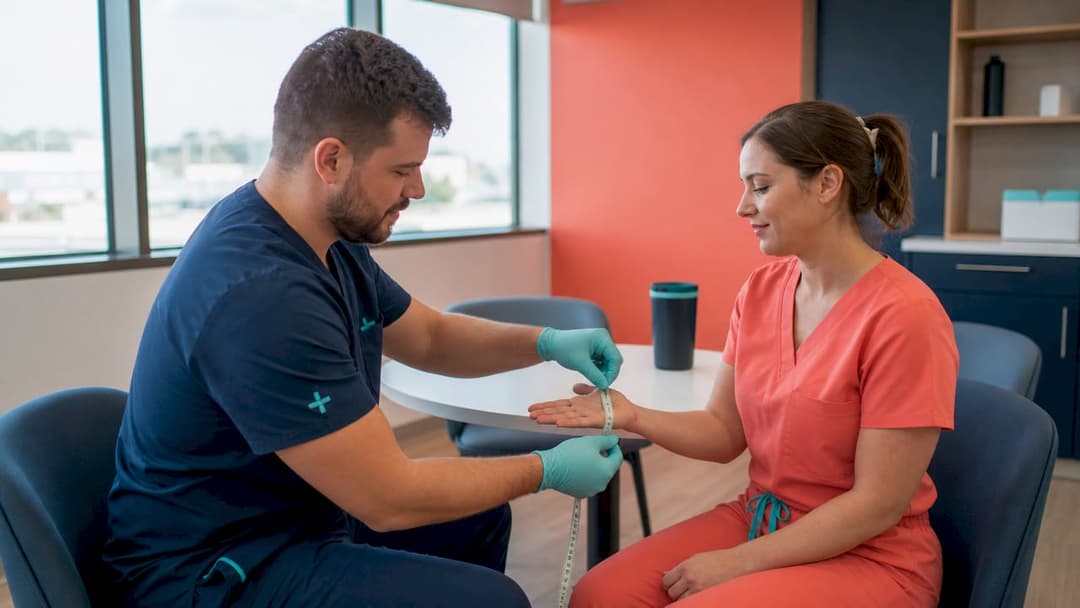
Proper sizing is the most overlooked factor in surgical glove selection. Surgical gloves come in numbered half sizes from 5.5 to 9.0, with a standard length of approximately 280 mm (about 12 inches). That precision exists because an ill-fitting glove reduces tactile sensitivity and increases hand fatigue during long procedures.
Measuring for the correct size requires two hand dimensions. Measure palm circumference at the widest point, just below the knuckles. Then measure the length of the middle finger from base to tip. When the two measurements suggest different sizes, go with the palm circumference as the primary guide.
Material elasticity changes the fitting equation. For latex gloves, a slightly tighter fit is preferred because latex stretches to conform and a loose fit causes slippage. Nitrile and synthetic-isoprene gloves have less natural stretch, so sizing up by half a size often produces a better working fit without restricting circulation.
Key sizing considerations for surgical teams:
Pro Tip: Have your surgical team measure both hands. Dominant and non-dominant hands often differ by half a size, and fitting to the larger hand prevents restriction on the dominant side.
Material choice is the single most consequential decision in a surgical gloves buying guide. Each material carries distinct trade-offs in elasticity, allergy risk, chemical resistance, and tactile feel. Matching material to procedure type and clinician profile is not optional. It is the foundation of safe glove selection.
Natural latex remains the benchmark for elasticity and tactile sensitivity. Latex conforms closely to hand anatomy and provides the most natural feel during fine motor tasks. The clinical concern is allergy risk. Protein content below 50 µg/dm² is the recommended threshold for reducing latex sensitization. Low-protein, powder-free latex gloves address most allergy concerns while preserving performance.
Synthetic isoprene is the preferred latex-free alternative for surgeons who need latex-level sensitivity without the allergy risk. Isoprene gloves closely replicate the stretch and feel of natural latex. They carry a higher per-unit cost than nitrile but are the right choice for high-precision procedures where tactile feedback is critical.
Nitrile leads in chemical resistance and puncture protection. Nitrile gloves are the standard in emergency rooms, dental settings, and any procedure involving chemical exposure. They are less elastic than latex or isoprene, which affects tactile sensitivity, but their durability makes them the right choice for high-risk or high-volume environments.
Powder-free finishes apply across all three materials. Powder-free gloves prevent residue and aerosol particles from entering the surgical field, reducing both irritation and contamination risk. Powdered surgical gloves are effectively obsolete in modern clinical practice.
| Material | Elasticity | Allergy risk | Chemical resistance | Best use case |
|---|---|---|---|---|
| Natural latex | Highest | Moderate to high | Low | Fine motor, open surgery |
| Synthetic isoprene | High | Very low | Low | Latex-free precision procedures |
| Nitrile | Moderate | Very low | High | Chemical exposure, high-risk procedures |
For a deeper look at glove material trade-offs, including allergy protocols and staff safety considerations, Queenssurgical’s procurement resource library covers each material category in clinical detail.
The concept of a single “best” surgical glove is misleading. Glove choice should be driven by clinical risk assessment that prioritizes procedure demands over trends or cost. A glove that performs well in laparoscopic surgery may be the wrong choice for a chemotherapy drug preparation environment.
Matching glove features to procedure type follows a clear logic:
For a procedure-based procurement framework, Queenssurgical’s surgical suite guide maps glove categories to clinical risk levels across common procedure types.
Procurement errors in surgical gloves fall into two categories: misuse and under-preparation. Both are preventable with a structured approach.
The most common misuse is deploying surgical gloves for non-sterile tasks. Using surgical gloves for routine exams or non-invasive procedures wastes significant budget with no clinical benefit. Conversely, using exam gloves for sterile procedures creates a documented safety gap. Clear usage protocols, posted at supply stations, eliminate most of this waste.
Latex allergy preparedness is the second most common gap. Proactive staff education on latex allergy protocols and the availability of latex-free alternatives at every station are critical for both safety and efficiency. Discovering a latex allergy mid-procedure is a preventable crisis.
“Gloves should be inspected periodically during surgery. Gloved hands must remain in front of and above waist level at all times to maintain the sterile field. Any breach requires immediate glove change.” — Clinical guidelines for sterile field maintenance
Additional best practices for procurement managers:
For guidance on safe procurement practices and compliance verification when ordering surgical supplies online, Queenssurgical’s buyer’s guide covers supplier vetting and certification checks in detail.
Choosing the right surgical gloves requires matching sterility standards, material properties, and glove size to the specific clinical procedure and the individual clinician’s hand profile.
| Point | Details |
|---|---|
| AQL standards define safety thresholds | Surgical gloves require AQL 1.0 or lower; exam gloves at AQL 2.5 are not sterile-field appropriate. |
| Material drives performance trade-offs | Latex offers the best feel; isoprene is the top latex-free option; nitrile leads in chemical resistance. |
| Sizing requires two measurements | Measure palm circumference and middle finger length; adjust for material elasticity. |
| Procedure type dictates glove choice | Chemotherapy handling requires ASTM D6978-tested gloves; open surgery favors latex or isoprene. |
| Double-gloving reduces perforation risk | Change the outer glove after 60–90 minutes in prolonged procedures to maintain sterile integrity. |
Most articles on surgical glove selection treat the topic as a product comparison exercise. After years of working with healthcare procurement teams across the Americas, I’ve found that the real problem is institutional habit. Facilities default to whatever glove they’ve always ordered, and nobody questions it until there’s an incident.
The shift I advocate for is treating gloves as procedure-specific clinical tools, not commodity consumables. That means your OR manager and your procurement manager need to be in the same conversation. A glove that costs $1.50 more per pair but reduces hand fatigue in a four-hour procedure is not an expense. It is an investment in surgical performance and staff retention.
Double-gloving is the clearest example of a practice that facilities resist for cost reasons and then adopt permanently after one close call. The data on perforation rates after 60–90 minutes is not ambiguous. The outer glove change protocol adds less than two minutes to a procedure and removes a documented contamination risk.
Sizing is the other underestimated variable. I’ve seen experienced surgeons working in gloves that are half a size too large because “that’s what we stock.” The loss of tactile sensitivity is real, and it accumulates over a career. Getting sizing right is one of the highest-return, lowest-cost improvements a facility can make.
— QB
Healthcare professionals and procurement managers who need verified, standards-compliant surgical gloves have a direct path through Queenssurgical. The platform stocks sterile surgical gloves across latex, synthetic isoprene, and nitrile categories, all with FDA and ASTM compliance documentation available on request.

Queenssurgical serves both individual clinicians and large healthcare facilities across the Americas, with bulk purchasing options that make procedure-specific stocking practical at scale. Whether you are building a procurement protocol for a single OR or standardizing glove selection across a hospital network, the full product catalog covers the clinical range you need. For facilities that require a tailored order, Queenssurgical’s team supports custom procurement requests directly through the platform.
Surgical gloves must meet an AQL of 1.0 or lower, which is a stricter pinhole defect threshold than the 2.5 AQL required for exam gloves. This tighter standard reflects the zero-tolerance requirement for contamination in sterile surgical fields.
Nitrile surgical gloves are appropriate for open surgery, particularly when latex allergy is a concern or chemical resistance is needed. They offer less tactile sensitivity than latex or synthetic isoprene, so procedure demands should guide the final choice.
Clinical guidance recommends changing the outer glove in a double-gloving setup after 60–90 minutes, as microscopic perforation risk increases significantly beyond that point. This practice maintains sterile field integrity without interrupting the procedure.
Gloves used during chemotherapy drug preparation or administration must be tested to ASTM D6978, the standard for chemotherapy resistance. Standard surgical gloves do not meet this requirement and should not be substituted.
Measure palm circumference at the widest point below the knuckles and middle finger length from base to tip. Use palm circumference as the primary guide, and adjust by half a size based on the elasticity of the glove material you are selecting.
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.
Mayo and Metzenbaum scissors look alike but do different jobs. See how blades, shanks and tips differ, when to use each, and how to care for them.
Sterile water or saline? Learn the difference in tonicity, safe uses, wound irrigation evidence, and how to choose irrigation and dressing supplies.

