
Double Gloving Guidelines: What U.S. Teams Should Follow
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.


Clinic supply inventory management is the process of systematically tracking, ordering, and controlling medical supplies and equipment in healthcare clinics to maintain availability, reduce loss, and control costs. Unlike retail stock control, medical inventory carries FDA traceability requirements, lot and serial number tracking for recalls, and strict expiration date oversight. Clinics that treat inventory as a core operational function, not a back-office task, protect both patient safety and financial health. This guide covers the tools, setup steps, troubleshooting strategies, and best practices clinic managers need to run a tight, compliant supply chain.
Effective clinic supply inventory management requires three things working together: accurate data capture at the point of receipt, real-time visibility across all storage locations, and defined rules for who can order and dispense stock. When any one of these breaks down, the entire system drifts. Inventory management is a strategic responsibility that directly affects patient safety and clinic financial health. That framing matters because it shifts the conversation from “who forgot to reorder gloves” to “what system failure allowed a stockout.”
Medical inventory differs fundamentally from retail stock. FDA traceability, lot and serial number tracing for recalls, and expiration date oversight are non-negotiable features, not optional add-ons. A clinic managing isolation gowns, face shields, and skin protectant creams must know exactly which lot number is on the shelf and when it expires. That level of detail is impossible with a spreadsheet.

The right technology stack for inventory control in clinics centers on barcode scanning, expiration tracking, automated reorder triggers, and integration with clinical record systems. Barcode-integrated inventory management systems reduce inventory shrink by up to 90% compared to manual methods. That reduction translates directly into lower waste costs and fewer emergency procurement orders.
When selecting a system, clinic managers should assess four feature categories:
Integration with your clinical record system is the feature most clinics undervalue. When a clinician documents a procedure, the system should auto-deduct the supplies used. Without that link, failure to integrate clinical records with stock usage causes inevitable human error and stock loss. Manual entry after the fact is the single largest source of data drift in clinic environments.
Pro Tip: Before committing to any inventory platform, run a vendor demo using your actual product catalog, including your fast-moving supply items. Generic demos hide configuration gaps that only appear with real SKUs.
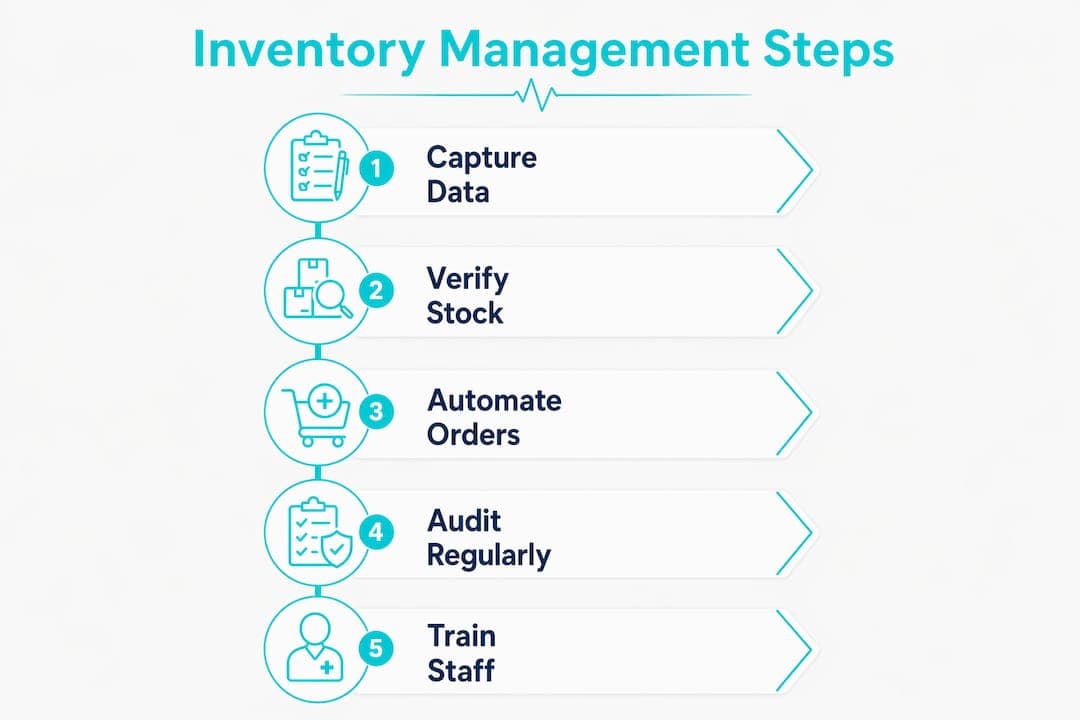
Initial setup for inventory management systems can take multiple weeks, including vendor demos, configuration, and ongoing adjustments. Build that timeline into your planning cycle. Rushing configuration is the most common reason clinics abandon systems within six months.
A structured setup process prevents the configuration errors that cause long-term data problems. Follow these steps in order.
Pro Tip: The most common setup error is entering pack size as the base unit. If your system shows “12 boxes” when you actually have 1,200 individual items, every reorder calculation will be wrong from day one. Fix this before you enter a single product.
For guidance on physical organization that complements your digital system, the medical supply room setup guide covers storage layout and labeling standards that reinforce accurate counting.
Most inventory accuracy problems in clinics trace back to three root causes: unlogged usage, wrong base units, and missing system integration. Each has a specific fix.
Data drift happens when stock leaves the shelf without a corresponding system entry. Clinical staff use supplies during a procedure and document the clinical outcome but not the supply consumption. Over days, the digital count diverges from the physical count. The fix is integration: when the clinical record closes, the system deducts the supplies automatically. No separate entry required.
When a physical count does not match the system, the instinct is to correct the number and move on. That approach hides the underlying cause. Instead, trace the discrepancy back to a specific transaction. Was a delivery received but not scanned? Was a return not logged? Each discrepancy is a data point about a process failure.
Troubleshooting checklist for common inventory problems:
Tiered audits increase data reliability by adapting audit frequency and depth to item importance. Auditing every item at the same frequency wastes time. Auditing critical items infrequently creates safety risk. Tier your audit schedule by item value and patient impact. Understanding inventory shrinkage in medical settings helps managers identify which categories carry the highest loss risk.
The clinics with the most accurate inventory share one characteristic: they treat stock control as a clinical leadership function, not an administrative one. The clinic director or medical director owns the process, not just the supply coordinator.
Data-driven demand forecasting separates reactive clinics from proactive ones. Pull usage reports monthly and look for trends. A clinic that sees a 20% increase in isolation gown usage over three months should adjust par levels before a stockout occurs, not after. Historical usage data is the most reliable input for procurement planning.
Centralized visibility across multiple locations is non-negotiable for multi-branch clinics. A manager who cannot see stock levels at a satellite location from the main dashboard will always be one phone call behind. Cloud-based systems with multi-location dashboards solve this without requiring on-site IT infrastructure.
Regulatory compliance and audit readiness require ongoing attention. FDA traceability and lot number tracing for recalls must be built into daily receiving processes, not reconstructed during an audit. Every item that enters the clinic should carry a digital record of its lot number, expiry date, and receiving date. For a detailed breakdown of compliance obligations, the retail medical compliance guide covers FDA traceability and recall management requirements.
Staff training and accountability close the gap between a well-configured system and accurate data. Train every staff member who touches inventory on the exact steps for receiving, dispensing, and returning stock. Assign a named individual as the inventory owner for each location. Accountability without a named owner defaults to no accountability.
Accurate clinic inventory management requires integrated systems, correct base units, and tiered audits to protect patient safety and reduce waste.
| Point | Details |
|---|---|
| Integration is non-negotiable | Linking clinical records to inventory prevents data drift and unlogged usage. |
| Base unit accuracy matters | Enter individual items, not packs or boxes, to keep counts and reorder alerts correct. |
| FEFO reduces expired stock | Making expiry date and lot number mandatory at receiving enforces First Expired, First Out logic. |
| Tiered audits save time | Audit high-value and patient-critical items weekly; lower-risk consumables monthly. |
| Leadership ownership drives results | Assigning a named inventory owner at each location creates accountability and consistent data. |
Clinic managers who treat inventory as a background function consistently underestimate its impact on clinical outcomes. I have seen well-run clinics with excellent clinical protocols run out of isolation gowns mid-shift because no one owned the reorder process. The clinical team was excellent. The inventory system was an afterthought.
The misconception that inventory control is purely administrative is the most expensive belief a clinic can hold. A stockout of a patient-critical consumable is a patient safety event. An expired lot of a skin protectant cream used in wound care is a liability. These are not supply chain abstractions. They are clinical risks with direct consequences.
Technology integration is where most clinics have the most room to improve. The tools exist. Barcode scanning, automated reorder triggers, and multi-location dashboards are not enterprise-only features. They are available to small and mid-size clinics at accessible price points. The barrier is not technology. It is the decision to treat inventory as a leadership priority.
My strongest recommendation: assign a named inventory owner at every location, run a tiered audit in the first week of every month, and review usage trends quarterly. Those three habits, consistently applied, will outperform any software implementation done without them.
— QB
Clinics that run tight inventory systems need suppliers who deliver consistent quality on the consumables that move fastest through their stock.

Queenssurgical carries the protective apparel and consumables that clinic managers track most closely, including disposable laboratory uniforms built from anti-fluid SMS material and CPE isolation gowns designed for infection control environments. Every product meets the quality standards that clinical procurement teams require. Queenssurgical serves clinics across the Americas as both a wholesale and retail supplier, with a catalog built around the consumables that appear most often on clinic reorder lists. Browse the full range at queenssurgical.net and source the supplies your inventory system is already tracking.
Clinic supply inventory management is the process of tracking, ordering, and controlling medical supplies in a healthcare clinic to maintain availability, reduce waste, and meet FDA traceability requirements.
FEFO (First Expired, First Out) prioritizes dispensing items closest to their expiration date, regardless of when they arrived. FIFO (First In, First Out) prioritizes items by arrival date, which can leave earlier-expiring stock unused.
Data drift occurs when clinical staff use supplies without logging the transaction. Integrating clinical record systems with inventory software auto-deducts used items and eliminates this gap.
Audit frequency should match item criticality and value. High-value or patient-critical items warrant weekly counts; lower-risk consumables can be reviewed monthly.
The most common error is entering pack or box quantities as the base unit instead of individual items. This causes every count, reorder alert, and usage report to reflect inaccurate numbers from the start.
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.
Mayo and Metzenbaum scissors look alike but do different jobs. See how blades, shanks and tips differ, when to use each, and how to care for them.
Sterile water or saline? Learn the difference in tonicity, safe uses, wound irrigation evidence, and how to choose irrigation and dressing supplies.

