
Double Gloving Guidelines: What U.S. Teams Should Follow
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.


Most healthcare administrators treat distributor agreements as a procurement formality. That assumption costs organizations real money and legal exposure. Understanding how distributor agreements for medical products work means recognizing that these contracts are not simple reseller arrangements. They are, as governance frameworks that align channel operations with competition law, data protection, and compliance obligations. This article walks you through every layer of these agreements, from core structure to negotiation tactics to regulatory accountability, so you can make smarter decisions at the procurement table.
| Point | Details |
|---|---|
| Agreements govern far more than pricing | Medical product distribution contracts define compliance roles, territorial rights, and performance obligations in detail. |
| Exclusivity is almost always conditional | Hybrid exclusivity with performance triggers protects your supply chain better than rigid exclusive arrangements. |
| Regulatory clauses prevent costly gaps | Contracts must explicitly assign vigilance, recall, and UDI responsibilities to avoid legal and patient safety failures. |
| Termination terms need careful attention | Standard notice periods run 90 to 180 days, and post-termination obligations like buybacks matter significantly. |
| Anti-kickback risks are real | Commission structures tied to physician referrals carry federal legal exposure that must be designed out of contracts. |
At their core, medical product distribution contracts establish the legal relationship between a manufacturer or supplier and the party selling products downstream. But the word “relationship” understates the complexity. These agreements define what the distributor can sell, where they can sell it, to whom, at what price ranges, and under what quality conditions. They also allocate legal risk between both parties for everything from product recalls to regulatory failures.
The distributor’s role and scope must be written with precision. A contract that calls someone a “distributor” without specifying whether they are an independent contractor, a limited agent, or an authorized reseller creates ambiguity that courts will eventually have to resolve, usually at significant expense to both parties.
Ambiguous territory definitions are the primary cause of disputes in distribution agreements. That means your contract must specify not just geographic boundaries but channel type and account category too. A distributor authorized to sell to hospital systems in the Southeast is not automatically authorized to sell to independent clinics in the same region unless the contract says so explicitly.
Product coverage should be listed by SKU or product family, with a clear process for adding new products. Without this, distributors sometimes represent competitor lines as “complementary” offerings, which erodes your market position quietly over time.
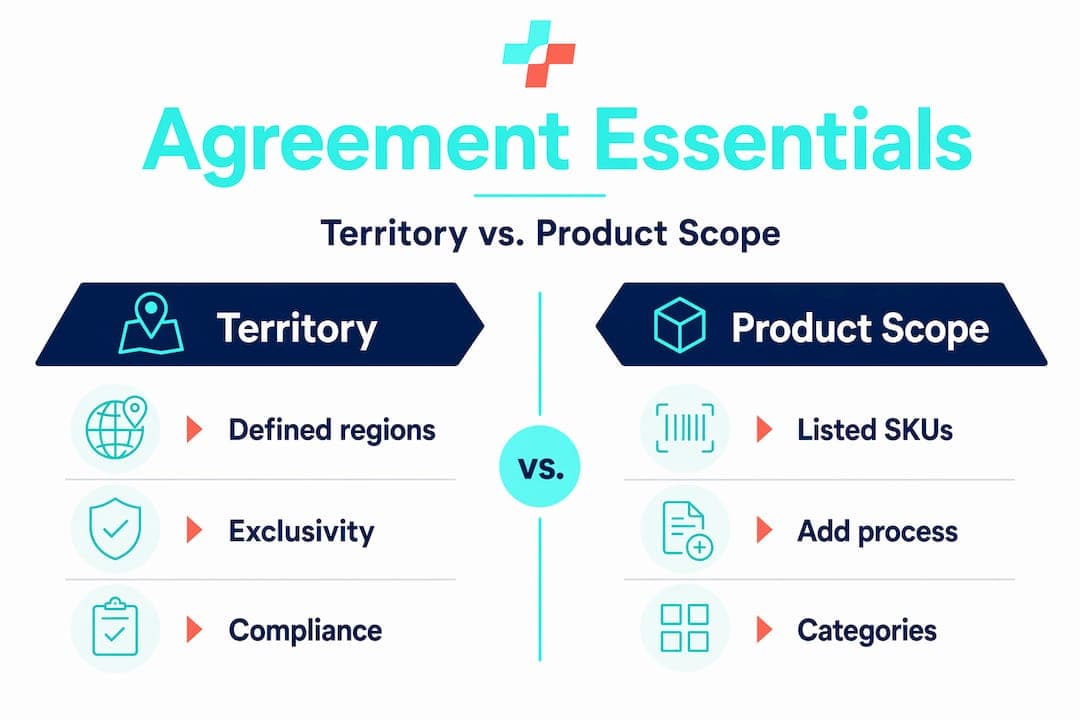
Performance minimums protect both parties. They give distributors a clear target and give manufacturers grounds to act when a territory is being underserved. Distributor marketing and training obligations, including minimum spend commitments and product training requirements, are the specific tools that enforce accountability. Vague language like “best efforts” is nearly unenforceable.
On pricing, the contract should include advance notice periods of 30 to 60 days for any price adjustments. This protects hospital procurement workflows and prevents distributors from being blindsided by changes that affect their margins and downstream customer commitments.
Pro Tip: Include a price protection clause covering orders already in the pipeline when a price increase is announced. Hospital procurement teams often work with 60 to 90-day purchasing cycles, and absorbing sudden cost increases mid-cycle damages trust fast.
Indemnification clauses define who pays when something goes wrong. Manufacturers typically indemnify against product defects. Distributors typically indemnify against misrepresentation, unauthorized modifications, or selling outside their authorized channel. The cleaner and more specific these provisions are, the less likely a product liability claim becomes a joint dispute between two parties pointing at each other.

Choosing the right structure for a medical distributor partnership is a strategic decision, not just a legal one. Here is how the main models compare and when each serves healthcare procurement best.
| Agreement type | How exclusivity works | Best fit | Key risk |
|---|---|---|---|
| Exclusive distribution | One distributor per defined territory | Specialized devices needing deep market investment | Underperformance with no fallback option |
| Non-exclusive distribution | Multiple distributors cover same territory | Commodity consumables with broad demand | Price undercutting and channel conflict |
| Hybrid exclusivity | Exclusive status contingent on performance targets | Mid-complexity devices in growing markets | Requires careful KPI design to be effective |
| Regional multi-distributor | Several non-exclusive local distributors | Fragmented geographic markets | Coordination complexity across distributors |
Multiple non-exclusive distributors in fragmented markets maintain coverage and serve as a risk mitigation strategy that purely exclusive arrangements cannot provide. If one distributor stumbles, supply continuity survives.
Pure exclusivity sounds appealing, but it creates leverage problems. Once a distributor holds exclusive rights to a territory, they have little financial pressure to exceed minimum performance. Modern exclusivity is often conditional, converting automatically to non-exclusive status if performance minimums go unmet for a defined period, typically after 18 to 24 months under review. This structure maintains the distributor’s motivation to grow the market while protecting your organization’s supply chain options.
For healthcare procurement professionals, this matters because the product complexity of your supply portfolio should drive your exclusivity choice. Complex capital equipment with high training requirements justifies exclusive arrangements. Surgical consumables and disposables are better served by flexible, multi-distributor models.
Understanding distributor agreements is one thing. Knowing what to push for at the negotiating table is where procurement professionals actually protect their organizations. Here are the terms that most often get under-negotiated.
Pro Tip: Always negotiate a right-to-audit clause into medical product distribution contracts. It lets your procurement team verify pricing compliance, rebate calculations, and sales volume claims independently, without waiting for disputes to surface.
This is where many organizations learn their most expensive lessons. When regulatory roles are shared between a manufacturer and a distributor, both parties often assume the other is handling critical obligations. That assumption creates gaps.
Contracts must explicitly assign vigilance reporting, complaint handling, recall logistics, and Unique Device Identification management to one named party per function. “Shared responsibility” language in a contract is functionally no responsibility at all when regulators come asking who owns an adverse event report.
Key compliance areas your contract should address explicitly include:
On commission structures, be careful. Royalty and commission arrangements tied to invoice prices can attract federal anti-kickback scrutiny when they function as incentives beyond the fair market value of actual distribution services. The Office of Inspector General has intensified review of payment structures that reward distributor loyalty in ways that look like referral payments.
Distribution agreements that fail to name specific owners for regulatory functions are not just incomplete contracts. They are compliance liabilities waiting to surface during an FDA inspection or a product recall event.
For procurement teams working across state lines or internationally, reviewing your retail medical compliance requirements before finalizing any agreement is a practical first step that prevents expensive contract revisions later.
I have reviewed enough of these agreements to know that the biggest mistakes rarely happen in the pricing sections. They happen in the territory definitions, the regulatory assignment clauses, and the exclusivity provisions.
In my experience, procurement professionals spend the most time negotiating unit price and payment terms, which makes sense on a budget level. But I have seen organizations locked into underperforming distribution partnerships for years because the exclusivity clause had no performance trigger and the termination notice period was too short to find a replacement distributor in a specialized product category.
What I have learned is that hybrid exclusivity consistently outperforms rigid exclusive arrangements over a three-to-five year horizon. Distributors with conditional exclusivity stay hungry. They invest in customer relationships, training, and sales infrastructure because they know the status can revert. Pure exclusivity removes that pressure.
The other thing most teams overlook is the post-termination section. I have watched procurement departments negotiate beautifully structured agreements on the front end, only to face a departing distributor who retained customer relationships, held product inventory with no buyback obligation, and had no non-compete restriction in adjacent territories. A thoughtfully structured exit is as important as the entry.
The clearest signal of a well-negotiated agreement is not the price per unit. It is the specificity of the regulatory roles section and the precision of the territory definition. Those two areas tell you whether the parties actually understood what they were agreeing to.
— QB

Whether you are evaluating medical distributor partnerships or sourcing directly for your facility, Queenssurgical provides healthcare professionals across the Americas with reliable, competitively priced medical supplies. The catalog covers surgical instruments, PPE, consumables, and wellness products built to meet industry safety standards. For procurement teams that need dependable supply continuity without the complexity of full distribution contracts, Queenssurgical’s platform makes procurement direct and efficient. Browse high-demand products like the surgical face mask with shield or the isolation mask with ear loop, and explore the full catalog at Queenssurgical to find what your facility needs today.
A medical product distributor agreement typically covers territory rights, product scope, exclusivity terms, performance minimums, pricing mechanisms, compliance responsibilities, and termination conditions. Each element should be written with specificity to prevent disputes.
Exclusivity in modern medical product distribution contracts is almost always conditional and performance-based. If a distributor fails to meet agreed volume targets, the agreement typically converts automatically to non-exclusive status after a defined review period.
Standard termination for convenience clauses in medical product distribution contracts require 90 to 180 days of advance notice, providing enough time for inventory transition and replacement sourcing without disrupting supply continuity.
The contract should name specific owners for adverse event reporting, recall coordination, UDI traceability, and import or export licensing. Leaving these as shared responsibilities creates regulatory gaps that regulators and auditors will flag.
Yes. Commission or royalty structures that tie payments to physician referrals or go beyond fair market value for actual distribution services can attract federal anti-kickback scrutiny. Contract terms should be structured to reflect legitimate service compensation only.
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.
Mayo and Metzenbaum scissors look alike but do different jobs. See how blades, shanks and tips differ, when to use each, and how to care for them.
Sterile water or saline? Learn the difference in tonicity, safe uses, wound irrigation evidence, and how to choose irrigation and dressing supplies.

