
Double Gloving Guidelines: What U.S. Teams Should Follow
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.


Consignment sounds simple on paper: the supplier drops off inventory, you use it, you pay for what you consume. No purchase order upfront, no capital tied up in idle stock. But understanding how consignment medical equipment retail works in practice means confronting a process far more demanding than that summary suggests. Hospitals accepting consigned surgical devices take on real operational obligations around billing reconciliation, regulatory traceability, and physical inventory control. This guide breaks down exactly how the model functions, where it breaks down, and what procurement teams need to manage it without costly mistakes.
| Point | Details |
|---|---|
| Consignment retention | Suppliers keep legal ownership of medical equipment until the device is used at the hospital. |
| Billing complexity | Invoices must be matched precisely with surgical records to ensure accurate payments. |
| Regulatory traceability | Consigned devices require unique device identifiers and lot capture for compliance, especially in the EU. |
| Inventory risks | Without visibility controls, consigned stock can be misplaced or misbilled across departments. |
| Technology benefits | Automation and RFID improve tracking, reduce errors, and streamline consignment management. |
At its core, consignment inventory places products at a hospital or clinic location while the supplier retains legal ownership until the device is actually consumed or used. The facility does not pay at delivery. Payment is triggered by use. That distinction matters enormously for accounting, liability, and cash flow.
Two roles govern every consignment relationship:
The contract between these parties defines the payment cycle, return rights, minimum stock levels, and audit frequency. Without a tight contract, the model falls apart quickly. Most consignment agreements in healthcare also specify device identifiers, lot numbers, and expiry date requirements, because the stakes of using the wrong device version can be clinical, not just financial.
Understanding the consignment benefits and challenges from both sides is critical before entering any agreement. The hospital gains access to a broader device portfolio without upfront capital expenditure, which is a genuine advantage in budget-constrained environments. The supplier gains placement inside the facility and pays for it in the form of inventory risk and delayed payment.
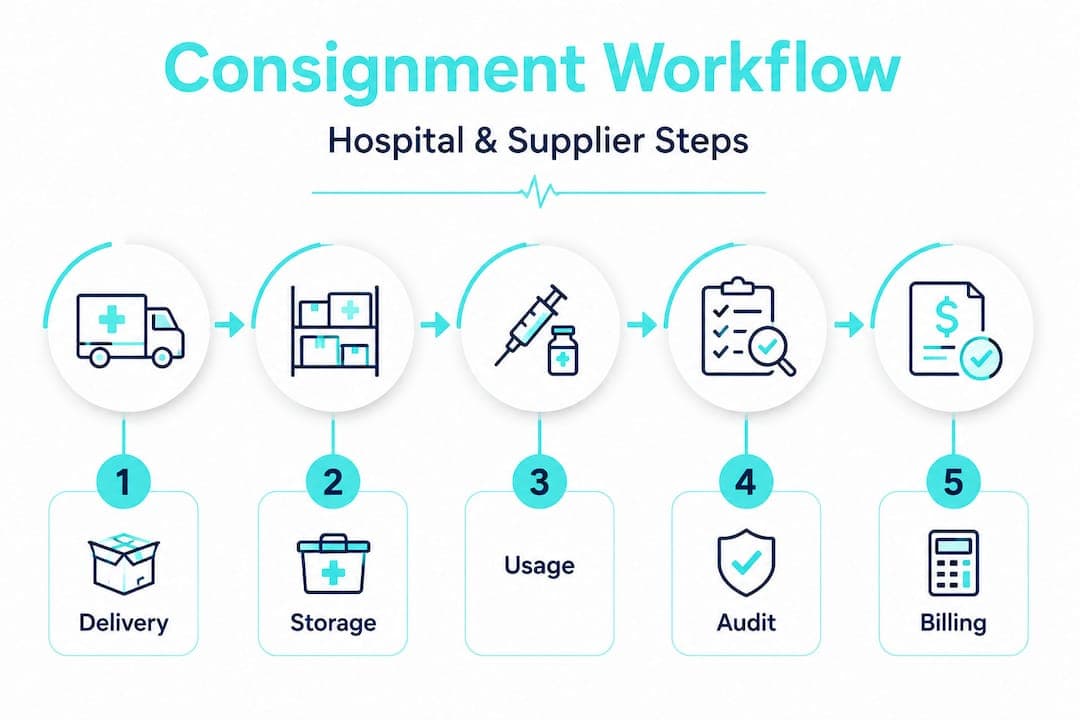
What often surprises procurement teams new to this model is that consignment stock still appears on the hospital’s physical inventory. It occupies storage space, requires handling, needs tracking, and must be accounted for in regulatory audits. “Free until used” does not mean “free to ignore.”
Consignment medical sales explained in theory look clean. In practice, the accounts payable side is where most hospitals struggle. Healthcare consignment billing is triggered by consumption, not delivery, which means every invoice from a supplier must be reconciled against actual procedure records before a single dollar is authorized.
Here is how the reconciliation process typically unfolds in a hospital:
The problem is that most hospitals receive invoices from dozens of suppliers using different formats, different device naming conventions, and different billing periods. Extracting and normalizing that data manually is time-consuming and error-prone.
Pro Tip: Require all consignment suppliers to submit invoices in a standardized format that maps directly to your procedure coding system. Even a simple template agreement up front eliminates hours of manual normalization per billing cycle.

AP teams handling surgical device consignment need more than spreadsheets. Automated reconciliation tools that pull OR procedure data and match it against supplier invoice data reduce error rates dramatically and flag discrepancies before they become disputed invoices.
If operational reconciliation is where hospitals feel the daily burden of consignment, regulatory traceability is where they face the largest risk exposure. Consigned devices in hospitals must now be traceable to their UDI with lot capture at point of use to comply with EUDAMED requirements effective 2026.
“Traceability under EUDAMED doesn’t stop at delivery. The link between the device’s Unique Device Identifier, its lot and expiry data, and the specific patient procedure must be captured and stored as an auditable record.”
What this means for procurement teams managing consignment stock:
Understanding surgical equipment regulatory traceability is not optional. Facilities that treat consignment as an informal arrangement, without proper documentation controls, expose themselves to regulatory findings that can freeze purchasing activity or trigger formal investigations. The 2026 EUDAMED mandate is not a distant deadline. It is active now.
Consigned inventory management frequently fails not because of bad intent, but because of structural weaknesses that build over time. The most common failure modes include:
Stat: Consignment inventory days on hand can exceed 130 days on average in healthcare facilities with poor visibility controls. That number represents supplier capital sitting idle and hospital storage space consumed without generating any operational value.
Pro Tip: Designate a single consignment inventory owner per department, ideally a charge nurse or materials coordinator with accountability for weekly stock audits. Distributed responsibility is no responsibility.
Procurement managers working on managing consignment inventory risks need to acknowledge that the financial exposure from poor consignment management is not theoretical. Overbilling goes unnoticed. Write-offs accumulate. And suppliers, seeing constant discrepancies, begin questioning whether the facility is a reliable consignment partner, which can affect their willingness to offer favorable terms.
Steps to start medical consignment business processes within a hospital require the same rigor you would apply to any capital program. Here is what works in practice:
Automation technologies like RFID and inventory management software enable real-time consumption tracking, reduce write-offs, and improve order-to-cash cycles. The efficiency gains are measurable, not hypothetical.
| Factor | Manual management | Automated management |
|---|---|---|
| Usage capture speed | Hours or days post-procedure | Real-time at point of care |
| Invoice matching accuracy | 70-80% without errors | 95%+ with exception flagging |
| Expiry detection | Periodic manual counts | Automated alerts before expiry |
| Audit preparation time | Days of manual consolidation | Same-day report generation |
| Cross-department tracking | Near impossible manually | Tracked by device identifier |
Consignment management best practices lean heavily on technology, but the foundation is process design. Tools do not fix broken workflows; they accelerate them, good or bad. Getting your inventory control and monitoring protocols right before implementing technology is what separates facilities that gain from consignment arrangements and those that are quietly buried by them.
Pro Tip: Before signing any consignment agreement, map the full data flow from device delivery through usage capture, invoice receipt, and payment. Every step without a clear owner or system touchpoint is a future problem.
Most articles on operating a medical consignment store focus on financial benefits. Lower upfront spend, wider device access, supplier-held risk. That framing is not wrong. But it sets up procurement teams to underestimate what they are actually agreeing to.
Here is the uncomfortable truth: when you accept consignment stock, you are not just accepting inventory. You are accepting operational responsibility for someone else’s assets. The supplier owns the product, but your team handles it, your systems must track it, and your facility is on the line if a compliance audit turns up gaps in device traceability.
The questions about consignment medical sales we hear most often are really questions about control. Who controls what gets used? Who controls what gets reported? Who controls the data that flows back to the supplier? In a poorly run consignment program, the answer to all three questions is “nobody, clearly.” And that gap costs hospitals money every quarter.
The smarter frame for procurement managers is this: consignment is not a purchasing model. It is a partnership model. It only works when both sides have clear obligations, matching data systems, and regular communication. Facilities that treat it as a passive arrangement, expecting suppliers to manage the complexity, consistently end up overpaying or underutilizing their consignment stock.
We have seen organizations run consignment programs effectively with nothing more than disciplined process and spreadsheet-level tooling, and others fail while using expensive inventory platforms. The variable is not technology. It is whether someone with authority owns the process from end to end.
Procurement decisions get easier when your supplier understands your operational environment. At Queens Surgical, we supply high-quality surgical instruments, medical equipment, and consumables to hospitals, clinics, and healthcare facilities across the Americas, and we understand that purchasing decisions involve more than just product specs.

Whether you are sourcing individual instruments or evaluating a broader supply relationship, our catalog is built for medical professionals who need reliable products at competitive prices. Browse our full range of surgical and medical supplies and take advantage of our weekly offers. Our team is ready to support your procurement process, from product selection through order fulfillment, so your facility always has what it needs when procedures are scheduled.
Unsold consigned goods typically remain the supplier’s property and can be returned without financial liability to the hospital, which is one of the primary advantages of the model for facilities managing tight budgets.
Hospitals match device serial numbers and usage data line by line against surgical procedure logs to confirm only actually consumed devices are billed, preventing both overpayment and underpayment disputes.
Yes. Consigned devices must comply with traceability rules requiring unique device identification and lot number capture at the point of use, particularly for facilities operating under EU MDR and EUDAMED mandates effective 2026.
The primary risks include weak visibility and inaccurate tracking, inventory misplacement, expiration of unused stock, cross-department transfers without billing updates, and invoice reconciliation errors that accumulate into significant financial losses over time.
Automation and RFID technologies capture real-time device consumption and location data, which improves billing accuracy, reduces product write-offs, and cuts the time AP teams spend on manual reconciliation work.
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.
Mayo and Metzenbaum scissors look alike but do different jobs. See how blades, shanks and tips differ, when to use each, and how to care for them.
Sterile water or saline? Learn the difference in tonicity, safe uses, wound irrigation evidence, and how to choose irrigation and dressing supplies.

