
Double Gloving Guidelines: What U.S. Teams Should Follow
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.
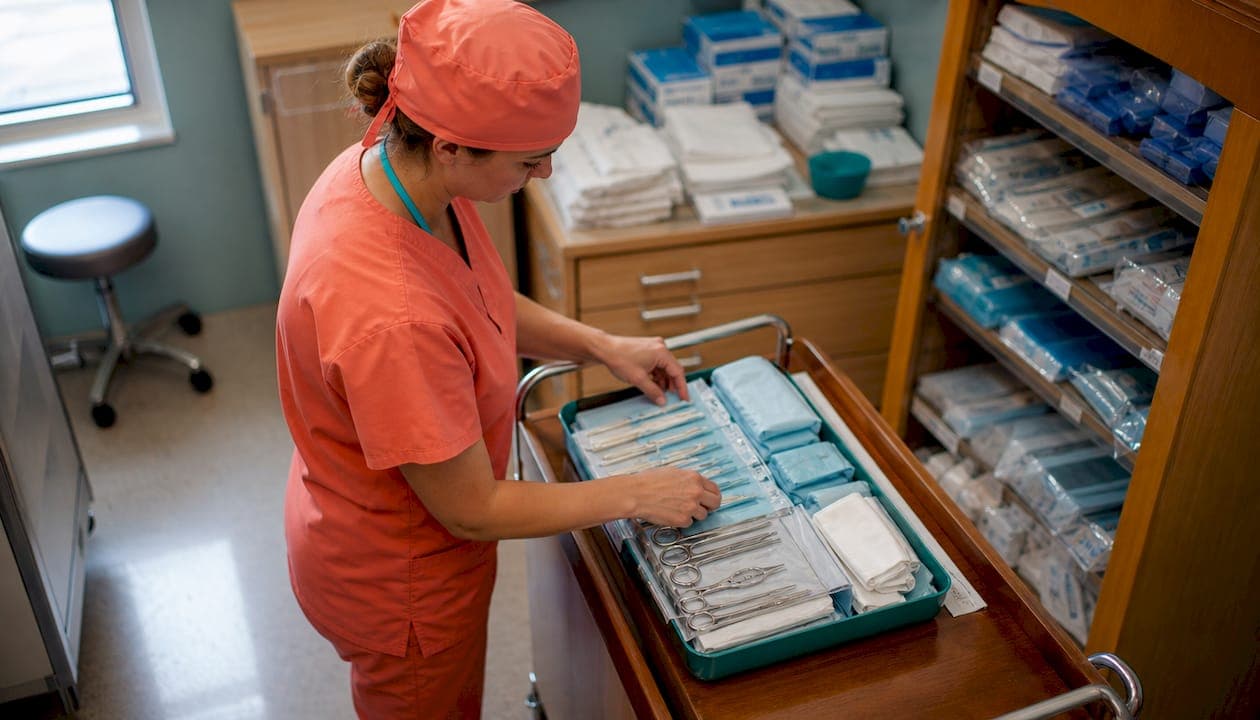
Operating room supply kits are pre-assembled packages containing all the surgical instruments and consumables required for a specific procedure, organized to reduce preparation time and eliminate intraoperative delays. Understanding how operating room supply kits work is the foundation of efficient surgical workflow management. Hospitals implementing procedure-specific custom trays can increase surgical procedure volume by up to 37%. That figure reflects not just convenience but a measurable operational advantage that affects patient throughput, staff performance, and resource use across every shift.
An operating room supply kit, also called a procedure pack or surgical tray, is a pre-configured collection of instruments and disposables assembled before a case begins. The goal is simple: every item the surgical team needs arrives in one container, verified and ready. This eliminates the time scrub technicians spend searching for individual components during setup and reduces the risk of missing items mid-procedure.
The kitting concept comes from manufacturing logistics. Kitting pre-groups all components required for a procedure into one container ahead of time, shifting material assembly away from the moment of need. In surgical practice, this means the OR team receives a complete, labeled package rather than pulling items from multiple storage locations. The result is faster room turnover and fewer opportunities for error.
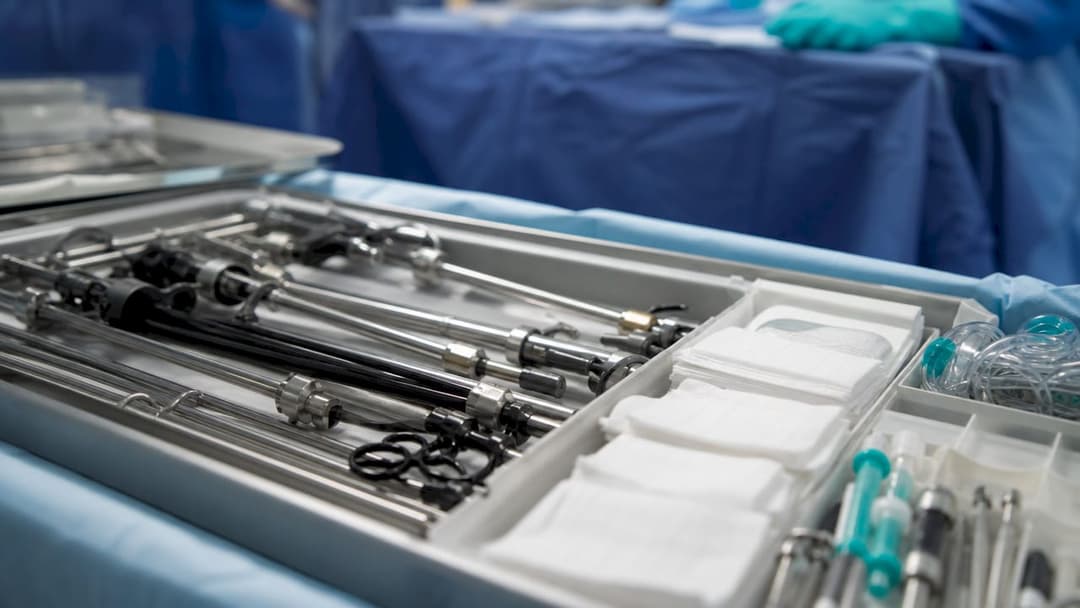
Procedure-specific kits are the standard in high-volume operating theaters. A laparoscopic cholecystectomy kit contains different instruments than an orthopedic arthroscopy kit. Matching kit contents to the procedure eliminates guesswork and keeps the sterile field organized from the first incision.
The components of surgical kits fall into two broad categories: reusable instruments and single-use consumables. Both categories require careful selection to avoid waste and support sterile technique.
Reusable instruments typically include:
Single-use consumables commonly included are surgical drapes, lap sponges, gauze, gloves, sutures, electrosurgical pencils, and irrigation supplies.
The clinical rationale for each item matters. Over-kitting with unnecessary items increases clinical waste, procurement costs, and complicates storage and stock rotation. A kit loaded with instruments that go unused in 90% of cases creates real financial and logistical drag. Procurement teams and clinical leads must review kit contents together, removing items that are rarely opened and adding surgeon-specific tools as separate supplementary stock.
Material quality directly affects sterilization reliability. Instruments made from surgical-grade stainless steel withstand repeated autoclave cycles without corrosion or deformation. Silicone mat holders in instrument trays significantly reduce verification time and setup variability, supporting rapid and reliable sterilization and setup processes. Silicone mats hold each instrument in a fixed position, so scrub technicians verify completeness at a glance rather than sorting through a loose pile.
Pro Tip: Review kit contents quarterly with both the lead surgeon and the supply chain coordinator. Clinical needs shift, and a kit built two years ago may carry instruments that are no longer used while missing newer tools that are.
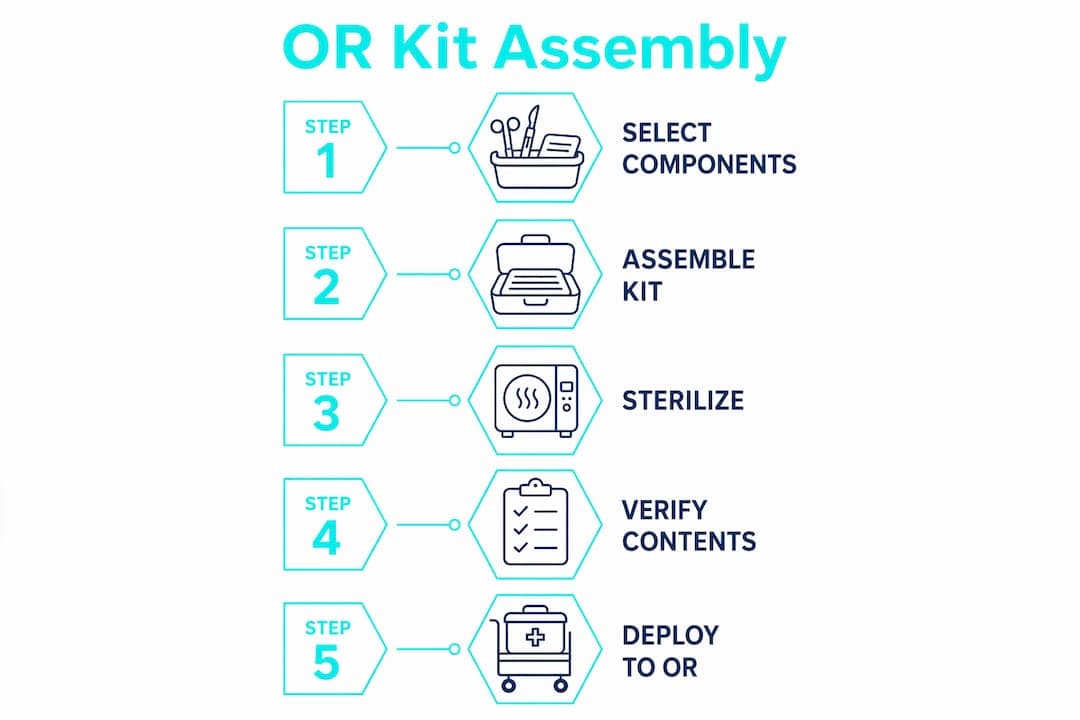
Accurate kit assembly follows a defined sequence. Skipping any step creates downstream errors that can delay or cancel a case.
Scheduling systems and materials requirements planning (MRP) tools drive kit preparation timing. A well-integrated MRP system triggers kit assembly 24–48 hours before the scheduled case, giving the sterile processing department enough lead time to complete sterilization cycles without rushing. Labeling also supports traceability. If a contamination event occurs, labeled kits allow the team to identify which cases used the affected batch and act quickly.
Managing partial kits during supply disruptions requires a documented exception protocol. The supply coordinator must flag the incomplete kit, notify the surgical team, and either source the missing item or adjust the case plan before the patient enters the room.
Standardization is an operational necessity, not just a convenience. Standard instrument sets reduce unpredictability and the costly OR turnover delays caused by variability in instrument sets. When every scrub technician works from the same tray layout for a given procedure, setup becomes predictable and fast regardless of who is on shift.
The most effective approach combines a standardized core kit with surgeon-specific add-ons stored separately. Hybrid kit models store core starter packs together with separately stocked surgeon-specific items, balancing clinical flexibility and inventory efficiency. This model prevents the two most common failure modes: over-kitting (too many items, most unused) and under-kitting (missing a critical instrument at the wrong moment).
The benefits of a well-standardized kit program include:
The risks of poor kit management are equally concrete. Variability in instrument sets forces scrub technicians to mentally recalibrate for each case, which increases the chance of errors under pressure. Missing components discovered after the sterile field is established can delay the procedure by 15–30 minutes while a replacement is sourced and re-sterilized.
Standardizing core surgical trays is an operational necessity, not just a convenience. It drastically reduces delays and cognitive load across surgical teams, and the data from high-volume theaters consistently shows that procedure-specific kits are the single most controllable variable in OR throughput.
Successful standardization projects require buy-in from surgeons, scrub technicians, sterile processing staff, and procurement. Clinical leads who resist standardization often do so because past kits were poorly designed. Involving them in the design process produces kits they trust and use consistently.
Well-managed supply kits produce measurable improvements across three areas: throughput, staff performance, and patient safety.
| Impact Area | Effect of Optimized Kits |
|---|---|
| Surgical throughput | Procedure-specific trays support up to 37% more cases per theater |
| OR turnover time | Standardized layouts reduce setup and breakdown time per case |
| Staff cognitive load | Fixed tray layouts reduce mental effort during high-pressure procedures |
| Instrument traceability | Labeled kits enable rapid response to contamination events |
| Infection risk | Verified sterile kits reduce bioburden exposure at the sterile field |
Standardized surgical instrument sets positively impact surgical precision, OR turnover time, and reduce physical and cognitive fatigue on surgical teams. Fatigue reduction matters because scrub technicians who spend less mental energy tracking instrument locations can focus on anticipating the surgeon’s next move, which directly supports procedural flow.
Instrument availability is a separate but related issue. Maintaining a minimum of 3 complete instrument sets per procedure type is required for continuous operation. High-volume theaters need 4–5 sets to prevent delays caused by sterilization cycling. A theater running on a single set faces an immediate shutdown if that set is contaminated or damaged.
Traceability built into the kit labeling system also supports infection control. When a sterilization failure is identified, labeled kits allow the sterile processing team to pull all affected trays before they reach the OR. This is a patient safety function, not just an administrative one.
Pro Tip: Integrate your kit labeling system with your electronic health record so that instrument set lot numbers are automatically linked to each surgical case. This makes post-incident tracing a minutes-long task instead of a multi-day manual audit.
Good supply chain management practices also support kit reliability. Procurement teams that track kit usage data can identify which components are consistently unused, adjust orders accordingly, and reduce the cost per kit over time.
Operating room supply kits are the single most controllable variable in surgical throughput, and their design, assembly, and standardization directly determine OR efficiency and patient safety.
| Point | Details |
|---|---|
| Kits drive throughput | Procedure-specific trays can increase surgical volume by up to 37% per theater. |
| Component selection is clinical | Over-kitting wastes resources; every item must have a documented clinical rationale. |
| Assembly requires a quality gate | Barcode or manual verification before sealing prevents intraoperative delays. |
| Hybrid models balance flexibility | Core starter packs plus surgeon-specific add-ons reduce waste without limiting clinical options. |
| Multiple sets prevent bottlenecks | High-volume theaters need 4–5 complete instrument sets per procedure type in circulation. |
The most common mistake I see is treating kit design as a one-time procurement decision. A kit built during a facility’s opening year reflects the surgical volume, case mix, and surgeon preferences of that moment. Three years later, the procedure mix has shifted, new surgeons have joined, and the kit is still carrying instruments from a technique nobody uses anymore.
The second mistake is designing kits without scrub technician input. Surgeons know what instruments they need. Scrub technicians know what is actually in the tray when the case starts. Those are not always the same list. Facilities that run quarterly kit reviews with both groups consistently report fewer missing-item incidents and faster setup times.
The technology piece is underused. Silicone mat trays and barcode verification are not expensive relative to the cost of a delayed surgical case. A single 30-minute delay in a busy OR costs more than a full set of silicone mats. The math is straightforward, but the adoption is slow because the upfront purchase requires a capital request while the delay costs are absorbed invisibly across the schedule.
My honest recommendation: treat your kit program as a living system. Review it with data, involve the people who actually use the trays, and invest in the verification tools that prevent errors before they reach the sterile field.
— QB
Queenssurgical stocks the consumables and protective apparel that belong in every well-built OR supply kit, from sterile drapes and isolation gowns to barrier sleeves and disposable lab uniforms.

The CPE thumb loop isolation gown and disposable laboratory uniforms are built from anti-fluid, latex-free SMS material that meets sterilization and infection control standards for OR environments. Queenssurgical serves hospitals, clinics, and surgical centers across the Americas with both wholesale and retail purchasing options, making it practical to source kit components in the quantities your facility actually needs. Browse the full surgical supplies catalog to find the consumables that fit your procedure-specific kit requirements.
An operating room supply kit is a pre-assembled package of surgical instruments and consumables organized for a specific procedure. It arrives at the OR ready for use, reducing setup time and the risk of missing items.
Components are selected based on the clinical requirements of each procedure, with input from surgeons and scrub technicians. Items with no documented clinical use are removed to prevent over-kitting and unnecessary waste.
High-volume theaters require 4–5 complete instrument sets per procedure type to maintain continuous operation through sterilization cycling. Running on fewer sets creates bottlenecks when a tray is contaminated or still in the autoclave.
A hybrid kit model combines a standardized core starter pack with separately stocked surgeon-specific add-ons. This approach reduces waste from unused items while preserving the clinical flexibility individual surgeons need.
Barcode scanning or manual counts confirm that every component is present before the kit is sealed and delivered. Catching a missing item before the case begins is far less disruptive than discovering it after the sterile field is established.
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.
Mayo and Metzenbaum scissors look alike but do different jobs. See how blades, shanks and tips differ, when to use each, and how to care for them.
Sterile water or saline? Learn the difference in tonicity, safe uses, wound irrigation evidence, and how to choose irrigation and dressing supplies.

