
Double Gloving Guidelines: What U.S. Teams Should Follow
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.


Pharmacy supply management is the coordinated process of forecasting, ordering, tracking, and controlling pharmaceuticals to guarantee medication availability, regulatory compliance, and cost control within healthcare settings. It is not simply a logistics function. It operates as an integrated ecosystem where procurement decisions, inventory discipline, and regulatory adherence all affect whether the right drug reaches the right patient at the right time.
The core objectives are straightforward: keep medications available, stay compliant with federal and state law, and control costs without sacrificing safety. Achieving all three simultaneously requires a structured approach built on several interdependent components.
Core components of pharmacy supply management:
Two federal agencies set the primary regulatory floor. The DEA governs controlled substances under the Controlled Substances Act (CSA), mandating strict recordkeeping, scheduling, and biennial inventory requirements. The FDA oversees drug safety, manufacturing standards, and, through the Drug Supply Chain Security Act (DSCSA), end-to-end track-and-trace requirements for all prescription drugs.
Key roles include the Pharmacy Supply Chain Manager, who oversees procurement strategy and financial oversight; pharmacists, who carry clinical and dispensing authority; and pharmacy technicians, who handle day-to-day ordering, receiving, and stock management. Data-driven decision-making and centralized purchasing tie these roles together, turning what could be fragmented activity into a system that scales. Centralized purchasing combined with automation and advanced analytics can lower inventory, waste, and stockouts, resulting in millions in savings; for example, MultiCare Health System saved $7.5 million and reduced inpatient pharmacy spend by 24%.
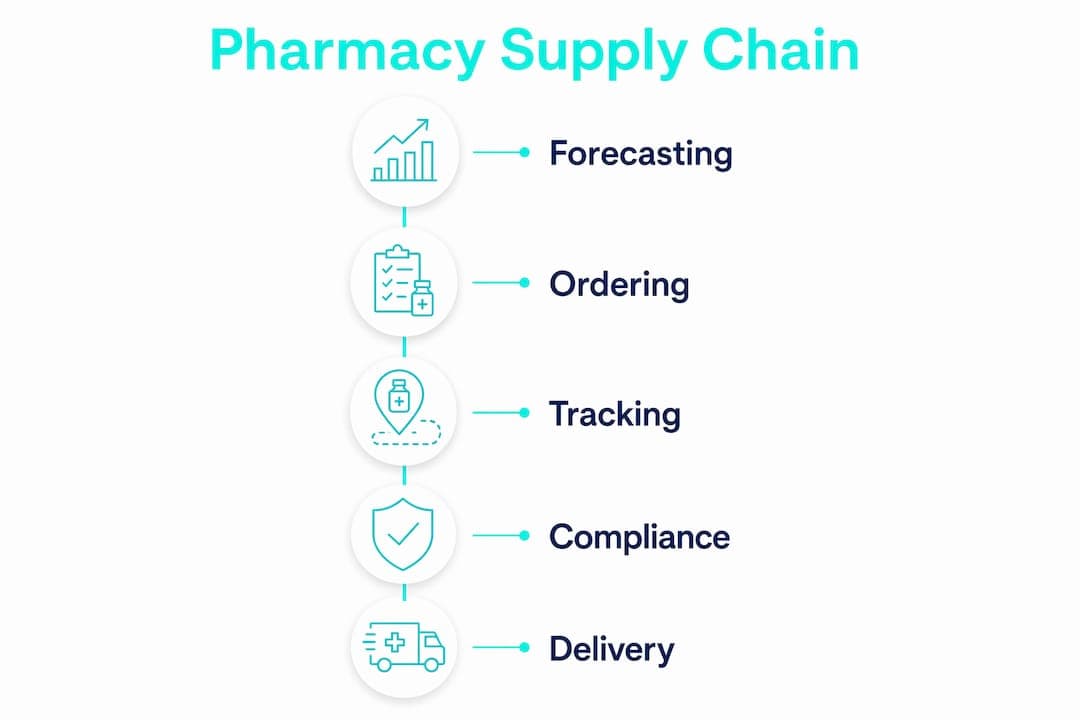
The pharmaceutical supply chain spans five major stages, each with distinct players and pressure points. Understanding who does what, and where things can break down, is foundational to managing the system well.
The five stages and their key participants:
Coordination among these players happens through electronic data interchange (EDI), shared formulary databases, and increasingly through integrated pharmacy management systems (PMS) that connect ordering, receiving, and dispensing in a single platform. When that coordination breaks down, the effects are immediate: delayed orders, substitution errors, or stockouts that force clinical teams to scramble for alternatives.
Lead times are one of the most persistent pressure points. A wholesaler’s standard delivery window might be 24–48 hours, but specialty drugs or controlled substances can take days longer, especially during shortage periods. Supply variability from manufacturers, driven by raw material constraints or production issues, compounds the problem. The FDA’s drug shortage database tracks active shortages in real time, and pharmacy procurement teams monitor it regularly to anticipate gaps before they hit clinical operations.
GPOs play a significant role in cost control by aggregating purchasing power across member institutions. But GPO contracts are not always the lowest-cost option for every drug category, which is why sophisticated pharmacy teams layer analytics on top of contract pricing to find gaps.

Pharmacy inventory management sits at the operational core of supply management. The goal is simple: know exactly what you have, where it is, and when it expires. The execution is considerably more complex.
Perpetual vs. periodic inventory: a direct comparison
| Feature | Perpetual inventory system | Periodic inventory system |
|---|---|---|
| Stock visibility | Real-time, updated per transaction | Snapshot at count intervals |
| Accuracy | High, when paired with physical audits | Moderate; gaps between counts create blind spots |
| Compliance fit | Strong for controlled substances | Limited; insufficient for DEA Schedule II requirements |
| Technology dependency | High; requires PIS or PMS integration | Low; can be manual |
| Operational burden | Ongoing data entry and reconciliation | Concentrated at count periods |
| Best use case | High-volume, regulated environments | Low-volume or supplementary tracking |
Perpetual inventory systems update a running stock balance automatically with every dispensing event, receiving transaction, and adjustment. Integrated with a pharmacy information system (PIS) or pharmacy management system (PMS), they give purchasing managers and pharmacists a live view of stock levels across every location. That visibility is what makes automated reorder alerts possible: when a drug drops below its par level, the system triggers a purchase order without requiring manual review.
Key features of a well-configured pharmacy inventory system:
Technology alone does not guarantee accuracy. Achieving true perpetual inventory demands disciplined daily or per-shift physical reconciliation, because software cannot prevent every discrepancy. A technician who pulls a medication without scanning it, or a receiving error that logs the wrong quantity, creates a gap between the system record and physical reality. Manual counts remain essential in high-volume pharmacies precisely because these gaps accumulate.
For controlled substances, the compliance bar is higher still. Schedule II substances require exact physical counts, tamper-evident storage, and perpetual inventory records that can withstand DEA audit. Cycle counts, where staff count a rotating subset of inventory daily rather than shutting down for a full physical count, help maintain accuracy without disrupting operations.

Pharmacy carousels, RFID systems, and point-of-use (POU) inventory platforms extend these capabilities into clinical units and operating rooms, where medication use happens far from the central pharmacy. One documented example found $14 million in annual savings by improving inventory accuracy and control through RFID and AI-supported POU systems.
Pro Tip: Set your automated reorder alerts at a level that accounts for your supplier’s lead time plus a safety buffer. A par level set at exactly one day’s supply with a 24-hour lead time leaves zero margin for delivery delays.
Compliance in pharmacy supply management is not a background concern. It is a daily operational requirement, and the consequences of getting it wrong range from financial penalties to criminal liability.
DEA and controlled substance requirements:
FDA and DSCSA track-and-trace requirements:
The Drug Supply Chain Security Act, fully enforced as of November 2023, requires every trading partner in the pharmaceutical supply chain to exchange transaction information, transaction history, and transaction statements (the “T3” documents) for each drug product. Track-and-trace capabilities covering lot numbers and expiration dates are now a baseline requirement, not an advanced feature. Integrated inventory software that captures this data at receiving and links it to dispensing records is the practical solution most health systems have adopted.
Ethical responsibilities and institutional standards:
Beyond federal law, pharmacy teams carry ethical obligations around medication security, patient privacy, and equitable access. The Joint Commission and state boards of pharmacy set additional standards for storage conditions, labeling, and staff competency. Facilities pursuing Joint Commission accreditation undergo unannounced surveys that include medication management reviews, making ongoing compliance training non-negotiable.
For a deeper look at how these frameworks apply in retail pharmacy settings, the retail medical compliance guide from Queenssurgical covers the regulatory landscape in practical terms.
Non-compliance carries real costs. DEA violations can result in registration revocation, fines, and criminal referral. DSCSA violations expose institutions to FDA enforcement action. Beyond legal exposure, a diversion incident or a medication error traced to poor inventory control can damage institutional reputation and, more critically, harm patients.
Pharmacy supply management faces a set of recurring problems that no single technology or policy fully eliminates. The teams that manage them best treat each challenge as a system design problem, not a one-time fix.
Drug shortages and supply disruptions:
Drug shortages are a structural feature of the U.S. pharmaceutical market, not an exception. Manufacturing consolidation, raw material constraints, and quality failures at production facilities all feed into a shortage pipeline that the FDA tracks continuously. Hurricane Helene’s impact on Baxter’s North Carolina manufacturing facility in 2024 illustrated how a single site disruption can ripple across the entire IV fluid supply. Pharmacy teams respond with therapeutic substitution protocols, allocation systems, and buffer stock strategies for high-risk drugs.
Cost containment under financial pressure:
Drug costs represent one of the largest and fastest-growing expense categories in health system budgets. GPO contracts provide a baseline, but they do not capture every savings opportunity. Wholesaler markups on oral generic solids, for example, can be significant, and pharmacy teams with spend analytics can identify where those markups are highest and route purchases accordingly.
Manual processes and multi-site coordination:
Manual inventory processes contribute to waste and inaccuracy at scale. Coordinating inventory across multiple pharmacy locations, each with its own ordering patterns and par levels, compounds the problem. Standardizing par levels, order schedules, and product selection across sites is a prerequisite for any meaningful automation investment.
Strategic solutions that work:
The medical supply chain management guide from Queenssurgical provides additional context on procurement strategies that apply across healthcare settings, including pharmacy-specific considerations.
Communication is the thread that holds these solutions together. When pharmacies, suppliers, and clinical teams share real-time data, shortages get flagged earlier, substitutions get coordinated faster, and waste gets caught before it compounds.
The strongest case for treating pharmacy supply management as a data-integrated ecosystem comes from health systems that have actually done it. The results are specific enough to be instructive.
Expert recommendations for system transformation:
compared to traditional wholesaler pricing
significant acute care pharmacy savings over multiple years, with a notable reduction in inpatient pharmacy spend. That is the documented result from MultiCare Health System after implementing centralized purchasing, perpetual inventory automation, and advanced spend analytics. The industry benchmark for comparable organizations during the same period was 7%.
The MultiCare case is worth unpacking because the sequence matters. Centralized purchasing came first, creating a coordinated structure that made analytics meaningful. Pharmacy carousels and ADCs came next, providing the real-time inventory data that analytics platforms need to surface opportunities. Spend analytics came last, identifying where GPO and wholesaler pricing was highest and routing purchases to better-priced alternatives. That order is not accidental. Analytics applied to fragmented, inaccurate inventory data produces noise, not insight.
Supply chains are structurally fragile due to upstream decisions in product development and manufacturing. Successful pharmacy supply management treats procurement as a data-integrated ecosystem, not a series of independent purchasing decisions. That framing changes what questions get asked, what data gets collected, and ultimately what savings get captured.
Procurement as a data-driven system requires transparency and standardization to reveal cost reduction opportunities and push waste below 1%. That threshold is achievable, but only when the data infrastructure supports it. Platforms using SQL Server Analysis Services and similar enterprise data tools create scalable data marts that let pharmacy leaders monitor KPIs across multiple sites and intervene before a back-order becomes a clinical problem.
The same analytical discipline that identifies savings opportunities also supports compliance. When every transaction is logged, every lot number is tracked, and every expiration date is flagged automatically, the audit trail that DEA and FDA require exists as a byproduct of normal operations rather than as a separate documentation burden.
Effective pharmacy supply management integrates centralized procurement, perpetual inventory discipline, regulatory compliance, and data analytics to reduce costs, prevent shortages, and protect patient safety.
| Point | Details |
|---|---|
| Perpetual inventory is the foundation | Real-time stock tracking, paired with daily physical reconciliation, prevents discrepancies that software alone cannot catch. |
| Centralize before you automate | Standardizing purchasing across all sites creates the data structure that analytics and automation require to deliver savings. |
| Regulatory compliance is operational | DEA Schedule II requirements, DSCSA track-and-trace, and Joint Commission standards shape daily inventory workflows, not just annual audits. |
| Data analytics multiplies savings | MultiCare’s centralized analytics approach yielded $7.5 million in savings and a 24% reduction in inpatient pharmacy spend over 2.5 years, against a 7% industry benchmark. |
| Direct sourcing changes the cost equation | Direct-to-manufacturer purchasing can yield greater savings compared to traditional wholesaler pricing when supported by spend analytics. |

Every pharmacy supply chain depends on reliable access to quality medical supplies, from the dispensing counter to the clinical unit. Queenssurgical supplies healthcare professionals, clinics, and health systems across the Americas with the medical products they need to keep operations running, including protective face masks, isolation gowns, instruments, and consumables that meet industry standards.
Whether you manage procurement for a single pharmacy or coordinate purchasing across a multi-site health system, Queenssurgical offers wholesale and retail options with competitive pricing and a catalog built for medical professionals. Browse the full product range and find what your facility needs today.
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.
Mayo and Metzenbaum scissors look alike but do different jobs. See how blades, shanks and tips differ, when to use each, and how to care for them.
Sterile water or saline? Learn the difference in tonicity, safe uses, wound irrigation evidence, and how to choose irrigation and dressing supplies.

