
Double Gloving Guidelines: What U.S. Teams Should Follow
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.


Healthcare organization budget planning for supplies is defined as the structured process of forecasting, allocating, and controlling spending on medical consumables, equipment, and services to maintain care quality without overspending. Medical supplies typically account for about 21.4% of total operational spend in a typical clinic, making this one of the largest controllable cost categories in any facility. With supply chain price increases projected at 2.78% overall for the period from july 2026 through june 2027, and IT costs rising as fast as 5.66%, administrators who rely on last year’s numbers will fall short. Effective budget planning in healthcare requires current market data, category-level analysis, and cross-functional coordination between finance, procurement, and clinical teams.
Sound healthcare organization budget planning for supplies starts with accurate baseline data. Before you build a single budget line, you need at least 12 months of historical spend data broken down by supply category: regular consumables such as gloves and masks, specialized clinical supplies, and capital equipment. Without that segmentation, your projections will be too broad to act on.
Supply categories behave very differently under inflation. Healthcare inflation is non-uniform: IT and facilities costs are accelerating faster than pharmacy spend, which means a single blended inflation rate will underestimate some categories and overestimate others. Indirect spend, for example, is projected to rise 3.85% while pharmacy inflation is slowing. Applying the right rate to the right category is the difference between a useful forecast and a misleading one.

The table below summarizes the core inputs and tools you need before building your supply budget.
| Input or tool | Purpose |
|---|---|
| 12-month historical spend by category | Establishes a reliable cost baseline |
| Vizient or GPO price forecasts | Provides inflation rates by supply segment |
| Inventory management system | Tracks real-time stock levels and usage rates |
| Demand forecasting software | Projects future consumption based on patient volume |
| Value analysis committee data | Identifies clinical variation and off-contract purchasing |
Pro Tip: Pull your spend data at the SKU level, not just the category level. Aggregated numbers hide the high-cost outliers that drive the most budget risk.
Once you have these inputs, classify your supplies using an ABC analysis: A items are high-cost, low-volume products that need the most scrutiny; C items are low-cost, high-volume consumables that need volume controls. This classification shapes every decision in the planning steps that follow.
A practical medical supply budget follows a defined sequence. Skipping steps, especially the clinical input phase, is the most common reason budgets fail within the first quarter.
The table below compares two common budgeting methods so you can choose the right fit for your organization.
| Method | Best for | Key limitation |
|---|---|---|
| Incremental budgeting | Stable organizations with predictable volume | Carries forward inefficiencies year over year |
| Zero-based budgeting | Organizations undergoing restructuring or cost reduction | Time-intensive; requires detailed justification for every line |
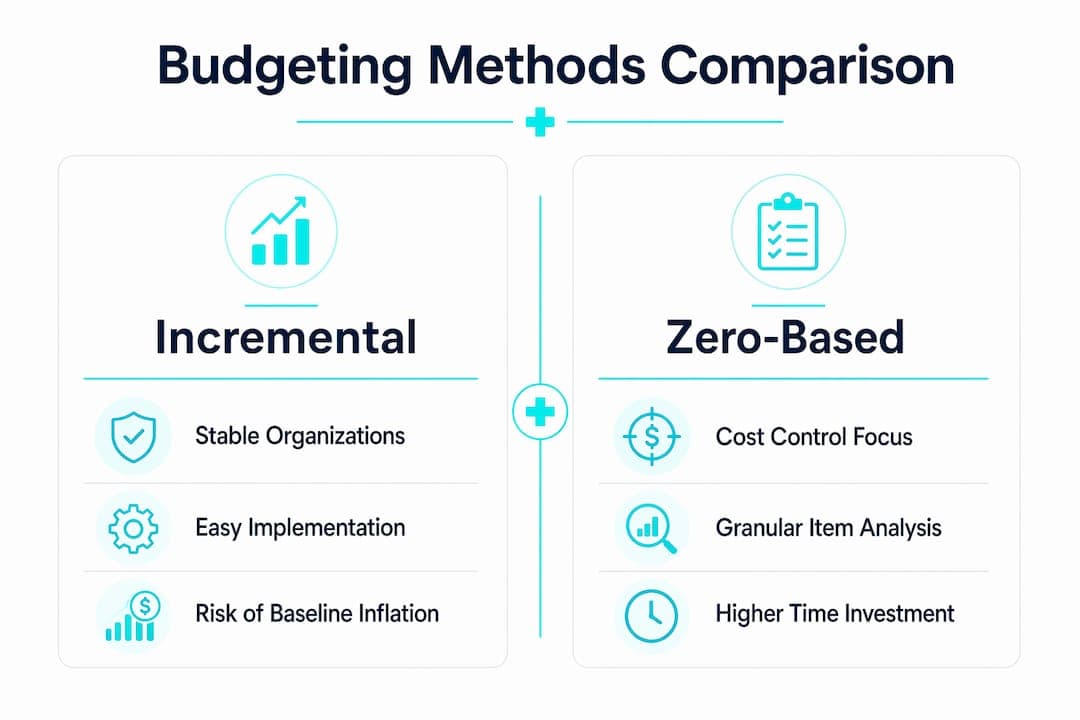
Pro Tip: Pair zero-based budgeting for your top 20% of supply spend with incremental budgeting for the rest. You get rigorous scrutiny where it matters most without drowning your team in paperwork.
For a deeper look at surgical supply sourcing techniques that complement this planning process, Queenssurgical has published practical guidance for hospital procurement teams.
A budget built in january is only as good as the monitoring process that follows it. Most budget overruns are not caused by bad forecasts. They are caused by late detection.
Real-time, automated receipt capture at the point of purchase enables earlier detection of budget overruns and improves monitoring effectiveness. When purchases are logged automatically rather than reconciled at month end, finance teams can act within days instead of weeks. That speed is the single biggest operational advantage in healthcare expense management.
Best practices for ongoing budget monitoring include:
Pro Tip: Assign a named budget owner to each major supply category, not just a department. Accountability by category produces faster responses to overruns than accountability by cost center alone.
Queenssurgical’s clinic inventory management guide covers practical monitoring frameworks that work for both small clinics and large health systems.
The biggest threat to any supply budget is external volatility. Shifting tariffs and trade policies add unpredictable cost pressure that historical spend data cannot capture. Planners who build budgets using only prior-year pricing are exposed to market shocks that can erase projected savings within a single quarter.
Specialized, high-cost supplies create a second layer of risk. High-tech implants and specialized medical supplies often surpass reimbursement caps, creating unpredictable financial exposure and patient co-pay variation. These items require granular, item-level analysis rather than category-level averages. A single product substitution in a high-volume surgical line can shift the budget by tens of thousands of dollars.
“Supply cost savings often come more from managing internal usage patterns and reducing clinical variation than from price negotiation alone. Organizations that focus exclusively on contract pricing miss the larger opportunity sitting inside their own walls.”
— Health Financial Management Association
Internal risks are just as serious as external ones. Off-contract purchasing, where clinicians or department managers buy outside approved vendor agreements, quietly inflates supply costs without triggering formal budget alerts. Supply management is evolving from pure procurement to a strategic value engine aligned with clinical and financial objectives. Organizations that treat it as a back-office function will consistently overspend. For guidance on managing supply chain transparency, Queenssurgical outlines how visibility into pricing and sourcing reduces these hidden risks.
Effective medical supply budgeting requires category-level data, inflation-adjusted forecasting, clinical collaboration, and real-time monitoring to control costs without compromising care.
| Point | Details |
|---|---|
| Supplies are a major cost driver | Medical supplies average 21.4% of operational spend, making them a top budget priority. |
| Inflation varies by category | Apply segment-specific rates: 2.78% overall, 3.85% for indirect spend, 5.66% for IT. |
| High-value items need focused analysis | Nearly 80% of supply expenditure comes from a small share of high-cost items. |
| Clinical collaboration cuts costs | Value analysis committees can generate millions in savings in the first year. |
| Real-time monitoring prevents overruns | Automated receipt capture and weekly reviews catch variances before they compound. |
Most finance officers I speak with treat supply budgeting as a back-office reconciliation task. They set a number in october, hand it to procurement, and revisit it when something goes wrong. That approach made sense when supply costs were stable and predictable. It does not work in 2026.
The organizations I have seen manage supply costs most effectively share one trait: they treat the supply budget as a living document, not an annual artifact. They meet monthly, not quarterly. They bring clinical leads into the room, not just finance and procurement. And they use data to challenge assumptions rather than confirm them.
The shift from reactive to proactive budgeting is not a technology problem. Most organizations already have the data they need. The gap is in how that data gets used. When a department head sees a weekly variance report with their name on it, behavior changes. When they see a quarterly summary buried in a finance deck, it does not.
One thing I would push every administrator to do right now: identify your top 10 supply items by total annual spend and build a dedicated monitoring protocol for each one. Those 10 items likely represent a disproportionate share of your total supply budget. Getting them right matters more than perfecting the rest of the catalog.
The future of cost control in healthcare organizations is not about squeezing vendors harder. It is about knowing your own usage patterns better than anyone else does.
— QB
Healthcare administrators need a supply partner that delivers consistent pricing, reliable availability, and a catalog broad enough to reduce the number of vendors you manage.

Queenssurgical serves clinics, hospitals, and healthcare facilities across the Americas with a full range of medical consumables, from isolation gowns and face shields to instruments and wellness products. Consistent pricing across orders supports the kind of budget accuracy that finance teams depend on when forecasting quarterly spend. Volume purchasing options help organizations reduce per-unit costs on high-frequency consumables. Visit Queenssurgical to browse the full product catalog and connect with the procurement team about volume pricing that fits your budget structure.
Medical supplies account for about 21.4% of total operational spend in a typical clinic, averaging roughly $13,500 per month for facilities with a $63,000 monthly budget.
Overall healthcare supply chain prices are projected to rise 2.78% between july 2026 and june 2027, with indirect spend up 3.85% and IT costs rising 5.66%, according to the Vizient Winter 2026 Spend Management Outlook.
Use zero-based budgeting for your highest-cost supply categories and apply granular, item-level analysis to specialized supplies, since nearly 80% of supply expenditure comes from a small share of high-value items.
Establishing cross-functional value analysis committees and reducing clinical variation in product selection are the most effective approaches, often generating millions in savings in the first year without compromising care standards.
External price volatility from tariffs and trade policy shifts is the leading risk, because it cannot be captured by historical spend data alone and requires current market intelligence to manage effectively.
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.
Mayo and Metzenbaum scissors look alike but do different jobs. See how blades, shanks and tips differ, when to use each, and how to care for them.
Sterile water or saline? Learn the difference in tonicity, safe uses, wound irrigation evidence, and how to choose irrigation and dressing supplies.

