
Double Gloving Guidelines: What U.S. Teams Should Follow
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.


A compliant medical-equipment return policy is a five-stage, audit-ready process that enforces eligibility, documents decontamination, and ties every inspection outcome to finance through an RMA lifecycle. Get any one of those stages wrong and you are looking at forfeited credits, contamination incidents, or a failed audit.
What your policy must deliver at minimum:
Start here: Add RMA preauthorization and Decontamination Certificate requirements to every vendor agreement before your next contract renewal.
The single most common source of return disputes is ambiguous eligibility language. Procurement managers need criteria specific enough to use at the receiving dock, not just in a policy binder.

Eligible vs. ineligible: a working reference
| Eligible (typical) | Ineligible or conditional (typical) |
|---|---|
| Unopened, sealed in original packaging with 12+ months to expiration | Opened or used items (unless recalled or decontaminated per manufacturer protocol) |
| Overstocked items purchased from the same vendor, currently in their catalog | Items that contacted the human body without documented decontamination |
| Recalled products returned by the deadline on the recall notice | Items expiring in less than 12 months |
| Items damaged in transit, reported promptly after receipt | Refrigerated, hazardous, or controlled substances |
| Loaner/demo equipment returned per the loaner agreement | Items below minimum value thresholds (e.g., under $50 per HHS PSC policy) |
| Unused but removed from original packaging, if vendor accepts with restocking fee | Explanted devices without a completed Decontamination Certificate |
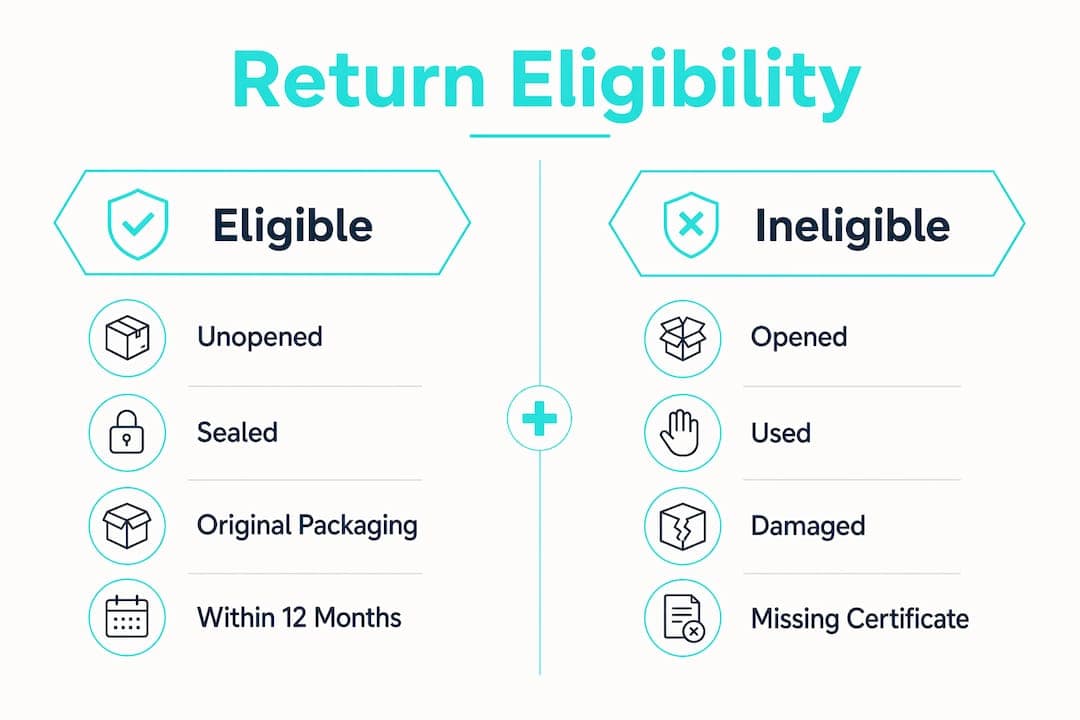
The HHS Program Support Center’s return goods policy is a useful benchmark: overstock items must be in original unopened packaging, currently stocked by PSC, and carry at least 12 months to expiration. That standard translates well to most vendor agreements.
Time windows matter. Standard return windows run within a timeframe commonly used for most consumables and capital equipment. Recalls are the primary exception: the deadline on the recall notice governs, and you should treat that date as a hard cutoff, not a suggestion. Vendor-specific programs for expired goods or loaner returns carry their own windows, which is why those terms belong in the vendor agreement, not just the internal policy.
Documentation required at initiation: purchase order number, RGA/RMA number, original invoice, and the device’s serial, model, and lot number. Missing any one of these at intake is grounds to reject the return request before it ever ships.
Treat every explanted or used device as biohazardous until a qualified person certifies otherwise. That is not overcaution; it is the baseline the Medtech Canada best-practice standard sets, and it maps directly to OSHA’s bloodborne pathogen rules for U.S. facilities.
Packaging requirements for contaminated or explanted devices:
If a shipment arrives without proper containment or labeling, the recipient may dispose of the device immediately without inspection, forfeiting any credit. That outcome is entirely preventable with a pre-shipment checklist.
What the Decontamination Certificate must include:
Contact the manufacturer first if there is any suspected infectious exposure or if the device-specific instructions prohibit standard cleaning methods. Improper decontamination (disassembly when not advised, immersion when contraindicated) can damage device integrity and void the inspection outcome entirely.
Pro Tip: Require photo evidence of the packaged device and completed certificate at initiation for all high-risk returns. It reduces rejected shipments and gives you a defensible record if a vendor disputes the condition on arrival.

Adopt a five-stage lifecycle and assign a named accountable role to each stage. Without that structure, returns pile up in a receiving area with no one responsible for moving them forward.
The five stages:
The flowchart for your SOP should follow this path: initiation → eligibility validation → RMA issuance → ship/receive → inspect → disposition → finance close. Every decision gate should have a named role and a documented outcome.
Pro Tip: Require photo evidence of suspected defects before issuing prepaid return labels. Apply tiered rules by item risk and value: high-value capital equipment gets a full inspection protocol; low-value consumables may go straight to disposition without a functional test.
Follow manufacturer shipping instructions first. When none exist, the default rule is double-impermeable containment in a rigid outer box with “Biohazard” labeling for any contaminated item. That is not optional; it is the condition under which a vendor will accept the shipment and process a credit.
Practical packaging checklist:
Carrier damage claims: Document the carrier scan events at receipt. Photograph the outer packaging before opening. File damage-in-transit claims within the carrier’s allowed window. HHS PSC policy, for example, requires reporting damaged items within five business days of receipt. Most commercial carriers have similar or shorter windows. Escalate to the vendor with the carrier claim reference number so they can coordinate on their end.
Typical timeline benchmarks to build into your SLA language:
Statistic callout: A structured returns management system linking the returns portal, receiving, grading, and accounting can speed available-to-sell timelines by up to 50% compared to manual processes, according to RMS implementation guidance.
Define the grading scale before the first return arrives. A four-tier system works for most healthcare supply chains and gives receiving staff a defensible, consistent framework.
Four-tier grading scale:
Inspection checklist for every return:
Disposition decision matrix:
| Condition grade | Disposition pathway | Accounting action |
|---|---|---|
| Grade A | Reinstate to active inventory | Reinstate at original landed cost |
| Grade B | Repackage and reinstate | Reinstate at landed cost minus repackaging labor |
| Grade C | Send to vendor for credit or route to repair | Hold in returns clearing account pending outcome |
| Grade D | Quarantine, arrange destruction, or donate with documentation | Write off or record donation at fair market value |
Photograph every disposition decision and store images with the RMA record. Those photos are your primary defense in a vendor credit dispute. For medical equipment storage during quarantine, follow your facility’s environmental and segregation requirements to prevent cross-contamination with active inventory.
Require a three-way match before any credit moves. That means the original purchase order, the RMA, and the inspection/grading report must all align before finance posts anything. A three-way match is the primary control against unauthorized credits and margin leakage in returns.
Finance steps in order:
KPIs every procurement and finance team should track:
Practical accounting controls: Hold credits until inspection is complete. Require supporting photos and inspection logs before approving vendor credits. Schedule a monthly returns reconciliation report that compares clearing account balances against open RMAs. Any RMA open longer than 45 days without a disposition decision should trigger an escalation.
Every vendor agreement and internal SOP should contain six core elements: RMA requirement, eligibility criteria, packaging and decontamination obligations, inspection grading definitions, disposition options, and finance/credit rules. AHRMM’s Policies and Procedures Manual for the Health Care Supply Chain identifies product returns, receiving documentation, and repair/replacement returns as discrete formal policies that must be maintained and audited.
Sample clause snippets:
Clauses to customize by facility size and vendor class:
| Vendor/item class | Key customizations |
|---|---|
| Capital equipment | Extended return window, functional test requirement, manufacturer sign-off |
| Consumables | Strict 30-day window, original packaging required, no partial case returns |
| Loaners/demos | Loaner agreement governs; return condition graded against loaner checklist at issue |
| Recalled items | Recall notice deadline governs; no minimum value threshold applies |
For RMA template fields, include: RMA number, issue date, expiration date, vendor name, facility name, item description, serial/lot number, return reason code, authorized signature, and disposition instructions. Integrate these fields into your procurement system or returns portal to eliminate manual data entry and reduce transcription errors. For context on how regulated medical device retail affects resale of returned items, review applicable FDA device class requirements before reinstating returned devices to active inventory.
Assign accountability by stage and document it. Without named roles, returns stall between departments and no one owns the outcome.
Role assignments by stage:
| Stage | Role | Key responsibility |
|---|---|---|
| Policy enforcement | Procurement policy owner | Maintains eligibility criteria and vendor terms |
| RMA initiation | RMA approver (procurement or supply chain lead) | Validates eligibility, issues RMA number |
| Shipping coordination | Shipping coordinator | Verifies packaging, labels, and documentation before dispatch |
| Receiving inspection | Receiving inspector | Grades item, photographs condition, records disposition |
| Finance reconciliation | AP/finance reconciler | Executes three-way match, posts credit or write-off |
| Decontamination certification | Authorized clinical or biomedical staff | Signs Decontamination Certificate |
| Disposal authorization | Risk/safety officer or department head | Authorizes destruction with documentation |
Staff training checklist:
Consistent staff training on handling protocols is one of the most direct ways to reduce contamination incidents and compliance gaps in any facility. Competency checks should happen at onboarding and annually thereafter. Training logs and SOP review records belong in the same audit binder as your RMA records. Review SOPs at least annually or whenever a regulatory update, vendor change, or incident triggers a gap.
Compliance with U.S. regulations is not a background condition; it is an active operational requirement at every stage of the return. Here is the practical breakdown:
HIPAA: Before returning any device that may store or transmit patient data (infusion pumps, imaging equipment, monitoring devices), verify that all patient-identifiable information has been removed or rendered inaccessible. Treat any device-linked protected health information (PHI) according to your facility’s privacy policies and HIPAA’s minimum necessary standard. This applies to both the physical device and any associated software or memory.
This article is general operational guidance, not legal or regulatory advice. Confirm current requirements with the relevant regulatory body or a qualified compliance professional for your specific situation.
Returns automation is not a luxury for large health systems. It is the mechanism that closes the loop between your returns portal, your warehouse management system, and your accounting platform. Without it, the five-stage lifecycle described above runs on spreadsheets and email, and days-to-available-to-sell stretches from days into weeks.
A purpose-built returns management system uses configurable rules engines to route disposition automatically, flag returns that require photo evidence or tiered approvals, and push grading outcomes directly to accounting. That integration is what makes the three-way match executable at scale rather than a manual reconciliation exercise. According to RMS implementation guidance, a structured system linking the returns portal, receiving, grading, and accounting can speed available-to-sell timelines by up to 50%.
Implementation tips for procurement teams:
Queenssurgical supports this workflow at the supply level. Standardized RMA fields, biohazard containment bags, and compliant packaging supplies are the physical inputs your RMS depends on. Getting those inputs right upstream means fewer rejected shipments and cleaner data flowing into your returns system.
A compliant medical-equipment return policy requires five accountable stages, a three-way match before any credit is issued, and mandatory decontamination documentation for all explanted or contaminated devices.
| Point | Details |
|---|---|
| Five-stage lifecycle | Assign named roles to policy enforcement, RMA initiation, logistics, inspection, and finance reconciliation. |
| Three-way match required | Match original PO, RMA, and inspection report before posting any credit or refund. |
| Decontamination Certificate | Required for all explanted or contaminated devices; must include device ID, cleaning method, date, and authorized signature. |
| RMS automation benefit | A structured returns management system can speed available-to-sell timelines by up to 50% versus manual processes. |
| Queenssurgical support | Queenssurgical supplies biohazard packaging, PPE, and standardized RMA-ready materials that feed directly into compliant return workflows. |
The biggest operational mistake is treating the returns lifecycle as a single event rather than five distinct processes. When policy enforcement, initiation, logistics, inspection, and reconciliation collapse into one informal workflow, you lose the audit trail, credits go unrecovered, and contaminated items end up in the wrong place.
Three patterns show up repeatedly in facilities that struggle with returns. First, RMA usage is inconsistent: some departments initiate returns without one, vendors receive unidentified packages, and credits never materialize. Second, Decontamination Certificates are treated as optional paperwork rather than a shipment prerequisite, which means vendors dispose of devices on arrival and the facility absorbs the loss. Third, finance reconciliation happens weeks after disposition, if at all, leaving the returns clearing account as a permanent holding area for unresolved credits.
The warning signs are measurable: long days-to-available-to-sell, a growing backlog of open RMAs past 45 days, and a pattern of vendor credit disputes. When those metrics trend in the wrong direction, the problem is almost always upstream in the policy or initiation stage, not in receiving.
One thing that gets underestimated is the vendor relationship dimension. Enforcement without communication creates friction. When you update your RMA requirements or add a Decontamination Certificate clause, brief your key vendors before the policy takes effect. Compliance improves faster when vendors understand the reason behind the requirement, not just the consequence of ignoring it.
Procurement managers who have built the policy framework still need the physical supplies to execute it safely. That is where Queenssurgical delivers direct, practical value.

Staff inspecting returned devices need proper PPE: full-length face shields for splash protection, isolation gowns for contamination control, and disposable laboratory uniforms for receiving and decontamination tasks. For packaging, Queenssurgical’s biohazard containment supplies meet the double-containment standard your policy requires. These are not generic supplies; they are the specific inputs your SOP depends on to function safely and compliantly.
Visit Queenssurgical’s shipping and returns page to review policy terms, explore product options for your returns workflow, or contact the team about bulk supply arrangements for your facility.
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.
Mayo and Metzenbaum scissors look alike but do different jobs. See how blades, shanks and tips differ, when to use each, and how to care for them.
Sterile water or saline? Learn the difference in tonicity, safe uses, wound irrigation evidence, and how to choose irrigation and dressing supplies.

