
Double Gloving Guidelines: What U.S. Teams Should Follow
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.

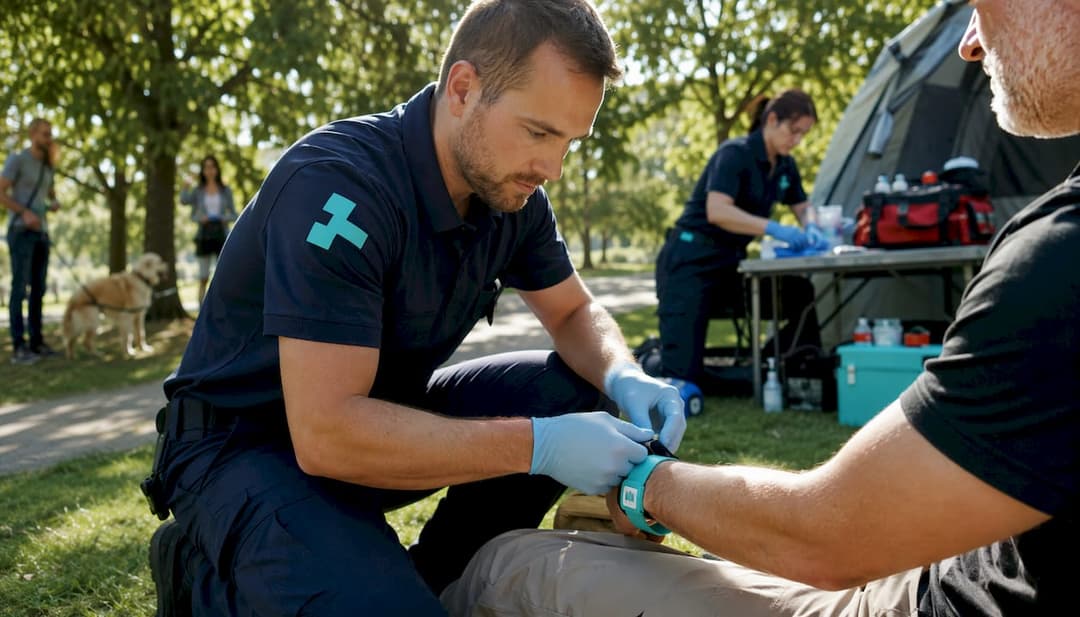
Commercial tourniquets are a first-line, life-saving intervention for severe external extremity hemorrhage. Apply one early. The American College of Surgeons Committee on Trauma and ILCOR/CoSTR both support their use when direct pressure fails or is not feasible, and a 2024 meta-analysis found prehospital tourniquet application was associated with significantly lower mortality (OR 0.48; 95% CI 0.27–0.86) in civilian extremity vascular trauma. The role of tourniquets in hemorrhage control is no longer debated at the guideline level. The question is whether your team applies them correctly and fast enough.
Three immediate actions define the standard of care:
The headline finding from a 2024 meta-analysis published in WJES is a significant mortality reduction in civilian patients with extremity vascular trauma who received prehospital tourniquet application.
ILCOR/CoSTR systematic review conclusion: Evidence from observational cohorts and military data consistently favors tourniquet use over direct pressure alone for severe extremity hemorrhage, with the survival benefit judged to outweigh risks even where certainty is rated low or very low due to study heterogeneity and bias.
The ILCOR/CoSTR review is candid about evidence quality. Most of the literature is observational; randomized controlled trials are absent for obvious ethical reasons. Military data from conflicts in Iraq and Afghanistan is the strongest available, and civilian data, while growing, is more heterogeneous. What matters clinically is the consistent direction of effect: across study designs and populations, early tourniquet application reduces bleeding-related mortality. The ACS Committee on Trauma guideline was built on exactly this evidence base, using GRADE methodology to translate low-certainty but directionally consistent data into actionable prehospital recommendations.
A separate systematic review in PMC found a trend toward reduced overall mortality with prehospital tourniquet use, though not statistically significant, and highlighted the need for higher-quality RCTs. The takeaway for practice: the evidence is not perfect, but the direction is clear and the alternative — uncontrolled hemorrhage — carries near-certain mortality.
Early application is now the standard, not a last resort. The joint U.S. prehospital position statement from ACEP, ACS COT, and NAEMSP explicitly supports this shift.
Apply a tourniquet when you encounter:
Prefer alternative methods when:
Two quick clinical scenarios: a construction worker with a partial degloving injury to the forearm and arterial spurting — tourniquet immediately, no debate. A pedestrian with a deep laceration to the thigh that stops bleeding with firm pressure in 30 seconds — maintain pressure, monitor, no tourniquet needed yet. The decision rule is simple: if you are not confident direct pressure will hold, apply the tourniquet now rather than after the patient deteriorates.

Placement is everything. The most common failures are not device failures — they are human factors: slack left in the band, placement over clothing, and misplacement over joints.
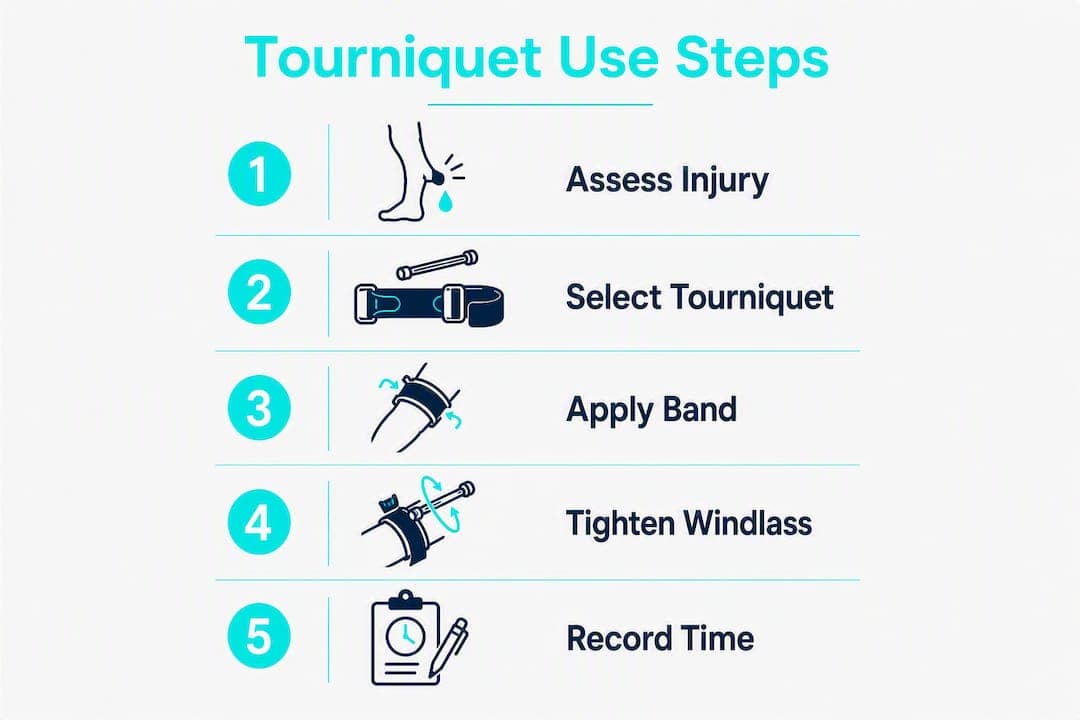
Step-by-step procedure:
For pediatric limbs: standard adult windlass tourniquets often do not fit limbs under 7.5 cm in circumference. Carry a pediatric-sized device or be prepared to use a blood pressure cuff as a temporary measure while arranging transfer.
For obese limbs or partial amputations: a single tourniquet may not generate sufficient occlusive pressure. Apply a second tourniquet immediately proximal to the first rather than loosening and repositioning.

Pro Tip: Before engaging the windlass, run your finger under the band to check for twisting or bunching. A twisted band concentrates pressure on a narrow strip of tissue, reduces occlusive effectiveness, and increases the risk of localized nerve injury. Flat band contact across the full circumference is what you want.
Manufactured tourniquets are preferred over improvised alternatives because they produce consistent, reliable arterial occlusion. A belt, a piece of webbing, or a rolled bandage may slow venous return without achieving arterial occlusion — which is worse than no tourniquet, because it increases blood loss while creating a false sense of control. Improvised devices are acceptable only when no manufactured option is available.
Procurement checklist for clinical managers:
For surgical supply sourcing at scale, aligning procurement cycles with training schedules prevents the common problem of purchasing devices your staff has never handled.
Pro Tip: Pair every procurement order with a mandatory hands-on skills station. A tourniquet sitting in a kit that no one has practiced with under stress is not a safety resource — it is a liability.
The key principle is this: do not remove a tourniquet in the field unless you are performing a planned conversion with wound packing and direct pressure ready. Removal belongs in the ED or OR, with surgical backup available.
ED and OR workflow:
Time thresholds matter. Mayo Clinic experts note that most patients transported within approximately two hours have low risk of permanent ischemic injury. Risk rises substantially when occlusion extends to 4–6 hours. That window is your operational target for hospital transfer.
Statistic callout: OR 0.48 (95% CI 0.27–0.86) for mortality with prehospital tourniquet use — but that benefit depends on timely transfer. Prolonged field time erodes the survival advantage.
Tourniquet conversion from device to hemostatic dressing or sustained pressure requires a planned sequence: pack the wound with a hemostatic dressing, apply sustained direct pressure, then loosen the tourniquet slowly while watching for rebleeding. If bleeding restarts, reapply immediately. This is not a field procedure unless you have no other option and the patient cannot be transported.
Complication monitoring list:
Limb ischemia and nerve or muscle injury from tourniquet use are time-dependent and pressure-dependent. When application is correct and hospital transfer is timely, major permanent harm is uncommon. The civilian prehospital review in PMC makes this point explicitly: fear of complications from appropriately used tourniquets is disproportionate to the actual risk.
| Category | Indication | Typical efficacy | Tolerated duration | Principal risks |
|---|---|---|---|---|
| Upper extremity | Arterial bleeding, forearm/arm | High with correct placement | Low risk with timely transport; higher risk with prolonged ischemia | Radial/ulnar nerve compression, skin injury |
| Lower extremity | Arterial bleeding, leg/thigh | High; may need two devices on thigh | Low risk with timely transport; higher risk with prolonged ischemia | Femoral nerve, compartment syndrome |
| Pediatric | Same indications; smaller limb circumference | Variable; device fit is critical | Similar considerations; less tolerance for error | Inadequate occlusion if device oversized |
Mitigation steps:
Escalate when you see: CK rising above 5,000 U/L, worsening motor or sensory deficit distal to the tourniquet, compartment pressures above 30 mmHg, or urine that is dark and not explained by dehydration alone.
Time applied is the single most critical data point. Without it, the receiving team cannot calculate ischemia duration, cannot time conversion safely, and cannot plan surgical intervention accurately.
Handover checklist (verbal and written/EMR):
One-line PCR documentation template:
“TQ applied [LEFT/RIGHT] [UPPER/LOWER] extremity at [TIME], [device type], [number applied], distal pulse [present/absent] at application, [no conversion attempted / conversion attempted with result].”
For structured medical handover practices that reduce communication errors at the point of transfer, the SOS-ID emergency communication guide offers a useful framework applicable to trauma handovers.
Reassess the tourniquet on every patient transfer: ground to stretcher, stretcher to ambulance, ambulance to ED gurney. Movement can shift device position and compromise occlusion without obvious external signs.
Didactic instruction alone does not produce reliable tourniquet application under stress. The narrative review on prehospital tourniquet techniques calls for improved simulation training alongside device availability, and that recommendation reflects what front-line educators already know: skill degrades fast without repetition.
Training program components:
Protocol elements for organizations:
For tactical responders and athletic trainers managing high-risk environments, injury prevention and emergency response training resources can complement institutional hemorrhage control programs.
Pro Tip: Run at least one unannounced drill per quarter where responders must locate, identify, and apply a tourniquet from a kit they did not pack themselves. Familiarity with your own kit is not the same as readiness.
Early tourniquet application with documented time and correct proximal placement is the most reliable intervention for reducing mortality from severe extremity hemorrhage in trauma.
| Point | Details |
|---|---|
| Apply early, not as a last resort | Guidelines from ACS COT, ACEP, and NAEMSP support early use when direct pressure fails or is not feasible. |
| Mortality benefit is substantial | A 2024 meta-analysis found OR 0.48 (95% CI 0.27–0.86) favoring prehospital tourniquet use in extremity vascular trauma. |
| Placement and documentation are critical | Place 2–3 inches proximal on bare skin, avoid joints, and record exact time of application immediately. |
| Transfer within ~2 hours limits harm | Most patients transported within approximately two hours have low risk of permanent ischemic injury; risk rises substantially at 4–6 hours. |
| Queenssurgical supports procurement | Queenssurgical stocks both single-use and reusable commercial tourniquets alongside trauma PPE for EMS and hospital purchasing. |
The evidence for tourniquet use in trauma is about as clear as observational data gets in emergency medicine. What is less discussed is why application failures still happen at a meaningful rate in both civilian EMS and hospital settings. The answer is almost never the device. It is the human factors: slack left in the band, placement over clothing because exposure took too long, time not written down because the provider assumed someone else would do it.
There is also a subtler institutional problem. Systems that purchase tourniquets without pairing them to mandatory skills stations are essentially buying false confidence. A device in a kit that no one has practiced with under stress is not a safety resource. Procurement and training have to be treated as a single workflow, not two separate budget line items.
The other thing worth saying plainly: the fear of causing limb loss from a tourniquet is still holding some providers back, and it should not be. The evidence is consistent that correctly applied tourniquets, with timely hospital transfer, carry a low risk of permanent harm. The risk of not applying one to a patient with arterial extremity hemorrhage is not low. That asymmetry should drive every protocol decision.
Stocking the right tourniquet before a mass-casualty event or a busy trauma shift is not a detail — it is the difference between a functional hemorrhage control kit and an empty one when it matters most. Queenssurgical supplies both single-use and reusable commercial tourniquets, trauma PPE, and consumables to EMS agencies, trauma bays, and hospital procurement teams across the Americas, with wholesale pricing and a catalog built for institutional buyers.

Whether you are building out a new ambulance stock list, refreshing your ED trauma bay, or sourcing disposable protective uniforms and isolation gowns for high-exposure bleeding events, Queenssurgical carries what your team needs. Browse the full trauma supply catalog at queenssurgical.net or contact the procurement team directly to discuss volume pricing and stocking schedules for your facility.
This article is general clinical information, not a substitute for professional medical judgment, institutional protocol, or current guideline review. Confirm current standards with your medical director and the primary sources listed above.
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.
Mayo and Metzenbaum scissors look alike but do different jobs. See how blades, shanks and tips differ, when to use each, and how to care for them.
Sterile water or saline? Learn the difference in tonicity, safe uses, wound irrigation evidence, and how to choose irrigation and dressing supplies.

