
Double Gloving Guidelines: What U.S. Teams Should Follow
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.
According to AHRQ, patient safety culture is the shared values, beliefs, norms, and behaviors that shape how an organization supports and promotes patient safety across every unit and organizational level. The shorthand version: it’s “the way things are done around here” when no one is watching. Measuring it starts with validated tools like the AHRQ Hospital Survey on Patient Safety Culture (HSOPS), and improving it requires more than a training day.
You can see safety culture operating in three places before lunch:
The stakes are not abstract. WHO data frames patient safety as the absence of preventable harm, and estimates that unsafe care is one of the leading causes of death and disability globally. In the U.S., the Institute of Medicine’s landmark 1999 report To Err Is Human put the problem on the national agenda by estimating that tens of thousands of Americans die annually from preventable medical errors. That report did not just document a problem; it reframed medical error as a systems failure, not a personal one, and that shift is the intellectual foundation of every safety culture effort since.
Patient safety culture is the shared values and behaviors that determine how an organization prevents harm, and improving it requires leadership commitment, validated measurement, and system-level interventions, not training alone.
| Point | Details |
|---|---|
| Core definition | Safety culture is shared values and behaviors shaping how staff prevent harm, measured with HSOPS or SAQ. |
| Evidence base | Leadership commitment and PPE access are among the strongest predictors of fewer adverse events and better compliance. |
| Measurement approach | Combine HSOPS or SAQ surveys with qualitative methods; survey scores alone do not capture actual behavior. |
| Just culture balance | Distinguish human error, at-risk behavior, and recklessness; respond differently to each to protect reporting culture. |
| 90-day starting point | Assess baseline, pick two priority domains, launch one quick win per phase, and track leading indicators weekly. |
Culture is not a policy document. It lives in the micro-decisions staff make under pressure, and those decisions are shaped by what the organization has historically rewarded, ignored, or punished.
A unit with a strong safety culture runs safety huddles at shift change, not because the Joint Commission requires them, but because the team has learned that five minutes of structured communication prevents hours of downstream problems. Incident reports get filed on near-misses, not just actual harm events, because staff trust that the response will be a system fix rather than a name on a report. When a surgeon skips a timeout, someone in the room says something.
Contrast that with a weak-culture unit: incident reports sit unfiled because the last person who submitted one got called into a meeting. Leadership walk rounds happen once a quarter, announced in advance, and feel performative. Staffing shortages get absorbed silently because raising them is seen as complaining.
Culture also operates at different levels simultaneously:
A hospital can have pockets of excellent safety culture in one ICU and a blame-heavy environment two floors down. That gap is itself a data point worth measuring.
AHRQ’s HSOPS organizes safety culture into measurable domains, and the Safety Attitudes Questionnaire (SAQ) covers overlapping ground from a slightly different angle. Both tools reflect a consensus on what dimensions matter most.
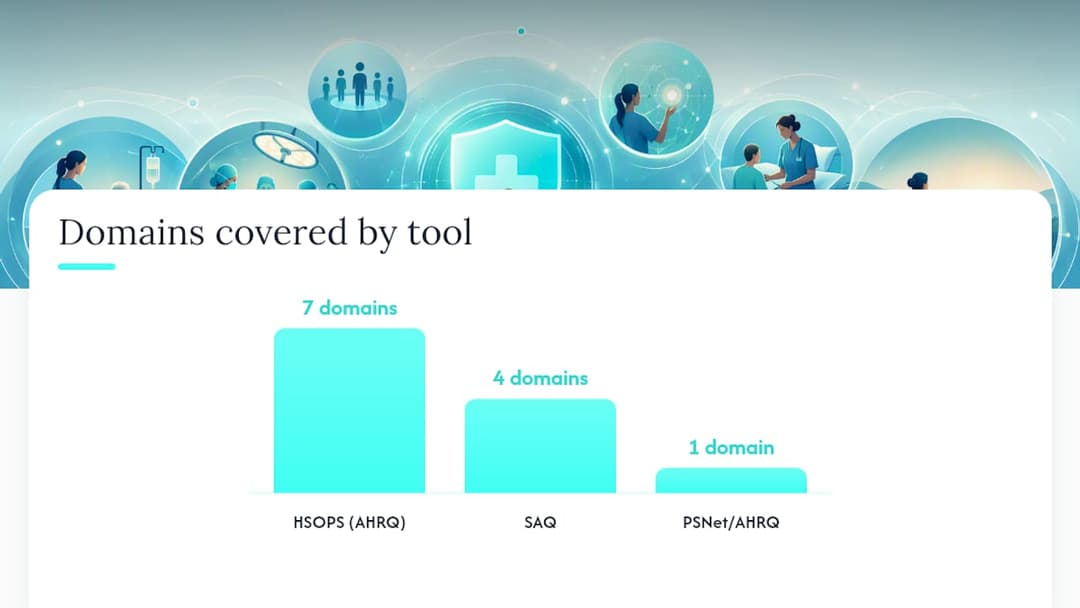
| Domain | What it measures | Covered by |
|---|---|---|
| Leadership commitment | Senior and unit-level leaders actively prioritize safety | HSOPS, SAQ |
| Teamwork climate | Staff feel supported and respected across roles | HSOPS, SAQ |
| Communication openness | Staff speak up freely about safety concerns | HSOPS, SAQ |
| Reporting culture | Near-misses and errors get reported without fear | HSOPS |
| Non-punitive response to error | Mistakes are treated as learning opportunities | HSOPS |
| Staffing and workload | Adequate staffing to work safely | HSOPS |
| Organizational learning | Feedback loops exist after incidents | HSOPS, SAQ |
| Just culture | Accountability is calibrated to behavior type | PSNet/AHRQ |
The just culture domain deserves a specific note. PSNet (AHRQ) draws a clear line between human error (a slip or lapse), at-risk behavior (a shortcut that seems reasonable in context), and reckless behavior (a conscious disregard for known risk). A just culture responds differently to each: support and system redesign for errors, coaching and removing incentives for at-risk behavior, and disciplinary action for recklessness. Collapsing all three into “blame the nurse” destroys reporting culture. Treating recklessness as a system problem destroys accountability. Getting that balance right is one of the hardest operational challenges in safety culture work.
The case for investing in safety culture is not theoretical. CDC/NIOSH guidance links visible management commitment and reliable PPE access directly to higher compliance with standard precautions and fewer adverse events. That connection between worker safety and patient safety is not incidental; organizations that protect their staff tend to protect their patients, and the reverse is also true.

A PMC review of hospital safety culture interventions found that leadership and organizational factors are among the strongest predictors of whether safety culture programs actually improve outcomes. Training alone rarely moves the needle, but what moves it is when senior leaders make safety a visible operational priority, allocate resources accordingly, and hold themselves accountable for lagging indicators.
The evidence base also covers staff outcomes:
On the cost side, adverse events are expensive. Hospital-acquired infections, surgical complications, and medication errors generate direct costs in extended stays, readmissions, and litigation. The Joint Commission and CMS both tie reimbursement and accreditation to safety performance metrics, which means safety culture is also a financial lever, not just a clinical one.
Pro Tip: When making the business case to a CFO, frame safety culture investment against the cost of a single preventable sentinel event, not against a training budget line. The math changes the conversation.
The two most widely used survey tools in U.S. healthcare are the AHRQ Hospital Survey on Patient Safety Culture (HSOPS) and the Safety Attitudes Questionnaire (SAQ). Both are validated, free or low-cost, and benchmarkable against national data. They are not interchangeable.
Surveys alone are not enough. A unit can score well on an HSOPS survey and still have observable behaviors that contradict those scores, because surveys capture attitudes and perceptions, not actions. Supplementing with qualitative methods (focus groups, structured interviews, leadership walk rounds with structured observation) gives you the “why” behind the numbers. Ethnographic observation, where a trained observer watches how a team actually handles a handoff or a near-miss, is resource-intensive but catches what surveys miss entirely.
A practical measurement strategy combines annual or biennial HSOPS administration with quarterly qualitative check-ins and ongoing behavioral indicators (incident report rates, near-miss ratios, time-to-close on safety reports). That combination links attitudes to outcomes rather than treating survey scores as the end goal.
The sequence matters. Organizations that skip baseline measurement and jump straight to interventions often invest in the wrong priorities. Here is a practical framework:
OSHA’s healthcare safety culture guidance reinforces that successful programs share a common architecture: leadership commitment, worker participation, hazard identification, prevention and control, training tied to system changes, and ongoing evaluation. The training piece is last for a reason. Training without system change teaches people skills they cannot use.
Pro Tip: Before adding a new training module, ask whether the barrier is knowledge or situation. If staff already know the right behavior but the workflow, equipment, or staffing makes it hard to execute, fix the situation first. Ensuring reliable access to PPE and supplies is a situational fix that training cannot substitute.
This timeline is designed for a department or service line, not a whole hospital at once. Pilot it at unit level, then scale.
Phase 1: Assess (Days 1–30)
Phase 2: Prioritize and plan (Days 31–45)
Phase 3: Pilot interventions (Days 46–75)
Phase 4: Measure and iterate (Days 76–90)
| Role | Responsibility during 90 days |
|---|---|
| CMO / CNO | Visible commitment, walk rounds, accountability for lagging indicators |
| Nurse manager | Daily huddle facilitation, frontline champion coordination |
| Quality lead | Survey administration, data analysis, feedback loop management |
| Frontline safety champion | Peer reporting encouragement, real-time barrier identification |
| HR / legal | Just-culture policy review and communication |
Quick wins that build momentum: leadership visibility on the floor at least twice per week, a single reporting-system friction point removed, one communication protocol (SBAR) adopted on one unit, and a posted “you said, we did” board showing staff what changed after a report. Building physician compliance culture alongside nursing engagement is worth the extra coordination effort; physician buy-in is often the rate-limiting step.
Most safety culture programs fail not because the interventions are wrong but because of predictable execution errors.
Pro Tip: Tie safety metrics to your existing operational cadence. If the department already reviews patient satisfaction scores monthly, add one safety leading indicator to that same meeting. Culture work that lives in a separate “safety committee” silo rarely reaches the people who make daily decisions.
Spotting these problems early means watching leading indicators, not waiting for an adverse event. A sudden drop in near-miss reporting rates is almost always a sign that something in the reporting environment has shifted, not that the unit has become safer.
Safety culture is not a soft initiative. The evidence connecting it to patient outcomes, staff retention, and organizational performance is substantial, and the cost of neglecting it shows up in adverse events, turnover, and accreditation risk. The IOM’s To Err Is Human reframed medical error as a systems problem more than two decades ago, and the U.S. healthcare system is still working through the implications.
What gets underestimated is the integration of worker safety and patient safety. Organizations that treat staff wellbeing as a separate HR concern and patient safety as a clinical quality concern miss the feedback loop between them. A burned-out nurse working a third consecutive short-staffed shift is a patient safety risk. Reliable access to properly stocked PPE and supplies is not just an infection control issue; it is a culture signal that tells staff whether leadership is serious about removing barriers to safe practice. That connection between supply chain reliability and frontline safety behavior is one of the most underappreciated levers in safety culture work.
The 90-day roadmap in this article is a starting point, not a destination. Safety culture improvement is iterative. The organizations that sustain it are the ones that embed it in operational decisions, not the ones that launch it as a project.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.
Mayo and Metzenbaum scissors look alike but do different jobs. See how blades, shanks and tips differ, when to use each, and how to care for them.
Sterile water or saline? Learn the difference in tonicity, safe uses, wound irrigation evidence, and how to choose irrigation and dressing supplies.

