
Double Gloving Guidelines: What U.S. Teams Should Follow
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.


Diagnostic tools are defined as any instrument, test, or procedure used to identify disease, evaluate patient condition, or guide treatment decisions. The role of diagnostic tools in patient assessment is foundational to modern medicine. Diagnostic tools influence approximately 70% of all clinical decisions, spanning everything from routine blood panels to advanced imaging. That single figure explains why clinicians who use these tools poorly produce worse outcomes, regardless of their therapeutic skill.
Diagnostic tools give clinicians objective data to confirm or rule out a clinical hypothesis. Without that data, treatment decisions rest on symptom patterns alone, which increases the risk of misdiagnosis. The WHO and CDC both recognize diagnostic accuracy as a core patient safety priority, and the CDC’s Diagnostic Excellence initiative specifically targets missed, delayed, and incorrect diagnoses as preventable harms.
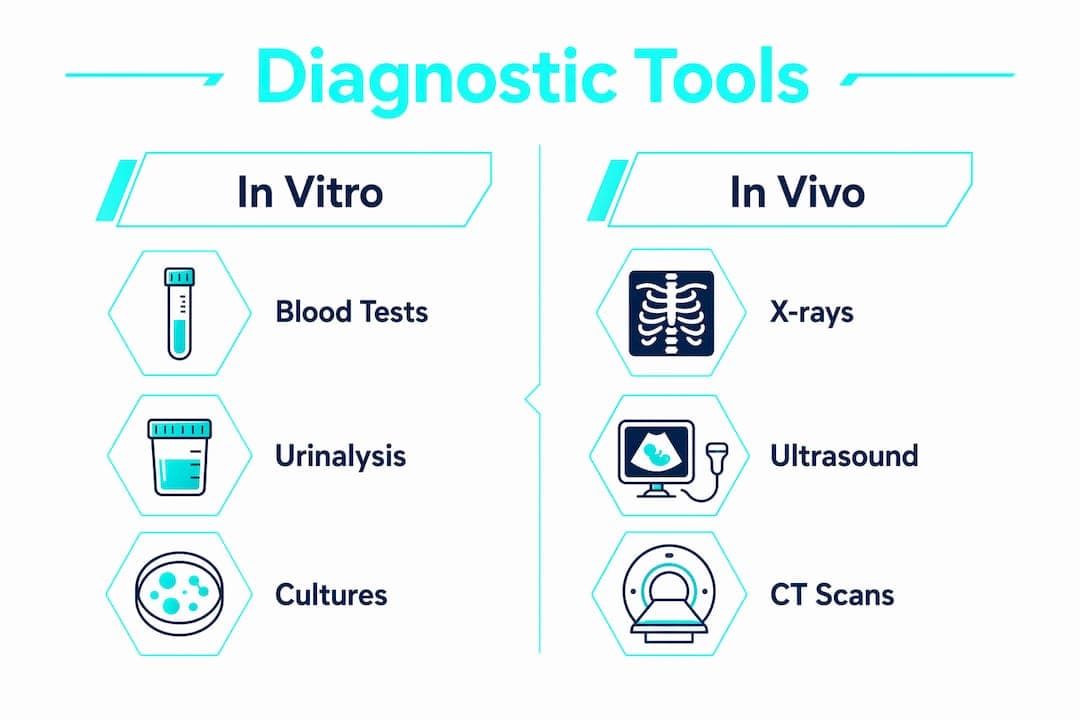
Clinical assessment methods fall into two broad categories. In vitro diagnostics include blood tests, urinalysis, and cultures performed on samples removed from the body. In vivo diagnostics include imaging studies such as X-ray, MRI, and ultrasound performed directly on the patient. Both categories serve distinct functions, and selecting the right type depends on the clinical question being asked.
The importance of diagnostic tools extends beyond individual patient encounters. Accurate, timely diagnosis reduces unnecessary procedures, shortens hospital stays, and lowers the cost of care. Clinicians who treat diagnostics as a core clinical skill, rather than a support service, consistently make faster and more defensible decisions.
Understanding the categories of diagnostic tools helps clinicians match the right test to the right clinical scenario. The three main categories are in vitro diagnostics, in vivo diagnostics, and point-of-care diagnostics.
In vitro diagnostics are the most commonly ordered tools in clinical practice. They include:
In vivo diagnostics provide structural and functional information that lab tests cannot. X-rays remain the first-line imaging tool for fractures and pulmonary pathology. MRI offers superior soft-tissue resolution for neurological and musculoskeletal conditions. Ultrasound provides real-time imaging without radiation, making it the preferred tool for abdominal and obstetric assessment.
Point-of-care diagnostics represent the fastest-growing segment of clinical assessment tools. Point-of-care tools like POCUS and high-sensitivity troponin deliver rapid, actionable results at the bedside. That speed directly reduces time-to-treatment in acute settings.

Pro Tip: Match test sensitivity to your clinical goal. High-sensitivity tests rule out disease by minimizing false negatives, while high-specificity tests confirm disease by minimizing false positives. Choosing the wrong type wastes time and can mislead management.
Diagnostic stewardship is the systematic practice of ordering, performing, and interpreting diagnostic tests appropriately to improve care quality and reduce harm. The term is borrowed from antimicrobial stewardship and applies the same logic: more testing is not better testing.
The scale of the problem is significant. Clinicians order 40%–60% of diagnostic tests unnecessarily, increasing the risk of overdiagnosis and overtreatment. Unnecessary tests generate abnormal results that require follow-up, expose patients to additional procedures, and increase costs without improving outcomes.
A structured stewardship approach addresses this through four steps:
The CDC’s Diagnostic Excellence programs formalize this approach at the hospital level. DxEx programs improve test ordering processes, interpretation workflows, and follow-up communication to prevent diagnostic errors before they reach the patient.
One concrete example: routine procalcitonin ordering without appropriate clinical context can prolong antibiotic treatment or cause misinterpretation. Stewardship protocols that require clinical justification before ordering procalcitonin reduce this risk significantly.
Pro Tip: Before ordering any test, ask one question: “Will this result change what I do next?” If the answer is no, the test is unlikely to benefit the patient.
Diagnostic tools are underused, misused, and underfunded relative to their clinical impact. Several systemic and practical barriers explain why.
Understanding reimbursement structures in medical retail helps procurement teams and practice managers align supply decisions with clinical priorities. The financial gap between diagnostic access and treatment access is a policy problem, but it has practical consequences at the clinic level every day.
Point-of-care diagnostics are reshaping how clinicians assess patients across every care setting. Bedside ultrasound (POCUS), high-sensitivity troponin assays, and rapid molecular testing have moved critical diagnostic capability out of the central lab and into the hands of the treating clinician. That shift reduces time-to-decision in emergency medicine, acute care, and pre-hospital settings.
Key developments driving this transformation include:
Point-of-care diagnostics improve patient flow and reduce hospital admissions by enabling faster, more accurate bedside assessments. That outcome matters most in high-volume emergency departments where bed capacity is the primary constraint.
Clinicians who stay current with surgical equipment and diagnostic technology options are better positioned to advocate for the tools their patients actually need.
Diagnostic tools drive approximately 70% of clinical decisions, making appropriate selection and interpretation the single most impactful skill in patient assessment.
| Point | Details |
|---|---|
| Diagnostics drive clinical decisions | Approximately 70% of medical decisions depend on diagnostic results, not symptoms alone. |
| Overtesting is a documented problem | Clinicians order 40%–60% of tests unnecessarily, increasing harm and cost without improving outcomes. |
| Stewardship improves care quality | Only order tests whose results will change patient management; DxEx programs formalize this standard. |
| Cost and policy gaps limit access | Diagnostic tests can cost $1,000 without insurance while matched treatments cost $30,000 annually. |
| Point-of-care tools are reshaping assessment | POCUS and high-sensitivity troponin deliver bedside results that reduce admissions and speed treatment. |
After years of working closely with healthcare procurement and clinical supply teams, the pattern I see most often is not underinvestment in diagnostic equipment. It is overconfidence in the act of ordering. Clinicians who order more tests believe they are being thorough. The data says otherwise.
The 40%–60% unnecessary testing rate is not a failure of equipment. It is a failure of clinical reasoning. The test is not the diagnosis. The test is a data point that either confirms or challenges a hypothesis the clinician should have formed before ordering. When that hypothesis is absent, the test becomes noise.
What actually works is simpler than most continuing education programs suggest. Ask the clinical question first. Then ask whether any available test can answer it with enough accuracy to change management. If yes, order the most specific test available. If no, document your reasoning and reassess. That process takes 30 seconds and eliminates the majority of low-value testing.
The second thing I would push harder on is communication. Diagnostic errors frequently trace back to results that were reported but never acted on. Building a closed-loop system where every abnormal result has an assigned owner is not a technology problem. It is a workflow problem that any practice can solve with existing tools.
The clinicians I respect most treat diagnostics as a discipline, not a service. They know their tests, they know their populations, and they know when not to order. That judgment is what separates good clinical assessment from expensive guesswork.
— QB
Safe patient assessment depends on more than the right test. It requires a clinical environment where practitioners are protected and equipped to work accurately.

Queenssurgical supplies the protective equipment that makes safe assessment possible. The CPE Thumb Loop Isolation Gown and fluid-resistant isolation gowns meet the protective standards required for direct patient contact in clinical and acute care settings. For skin integrity during extended assessment protocols, the DynaShield Skin Protectant Cream supports both patient and practitioner skin health. Queenssurgical serves clinics, hospitals, and healthcare facilities across the Americas with competitively priced, quality-verified medical supplies available through both wholesale and retail channels.
Diagnostic tools influence approximately 70% of all clinical medical decisions. That figure applies across primary care, emergency medicine, and specialist practice.
Diagnostic stewardship is the practice of ordering, performing, and interpreting tests appropriately to reduce unnecessary testing and improve patient outcomes. The CDC’s DxEx programs provide a structured framework for implementing stewardship at the hospital level.
Clinicians order 40%–60% of diagnostic tests unnecessarily, according to published clinical data. Unnecessary testing increases costs, generates incidental findings, and raises the risk of overtreatment.
Point-of-care diagnostics are tests performed at or near the patient, including POCUS and high-sensitivity troponin assays, that deliver immediate results without sending samples to a central lab. They are central to acute medicine and decentralized care delivery.
Diagnostic blood tests can cost around $1,000 without insurance, while the treatments they guide may cost $30,000 annually. Regulatory and reimbursement policies have not kept pace with diagnostic innovation, leaving many patients without access to the tests that would direct their care.
What CDC, OSHA, AORN and WHO say about double gloving, when to do it, how to don two pairs, and what procurement teams should stock for compliance.
Mayo and Metzenbaum scissors look alike but do different jobs. See how blades, shanks and tips differ, when to use each, and how to care for them.
Sterile water or saline? Learn the difference in tonicity, safe uses, wound irrigation evidence, and how to choose irrigation and dressing supplies.

